Demography
Estimating the population
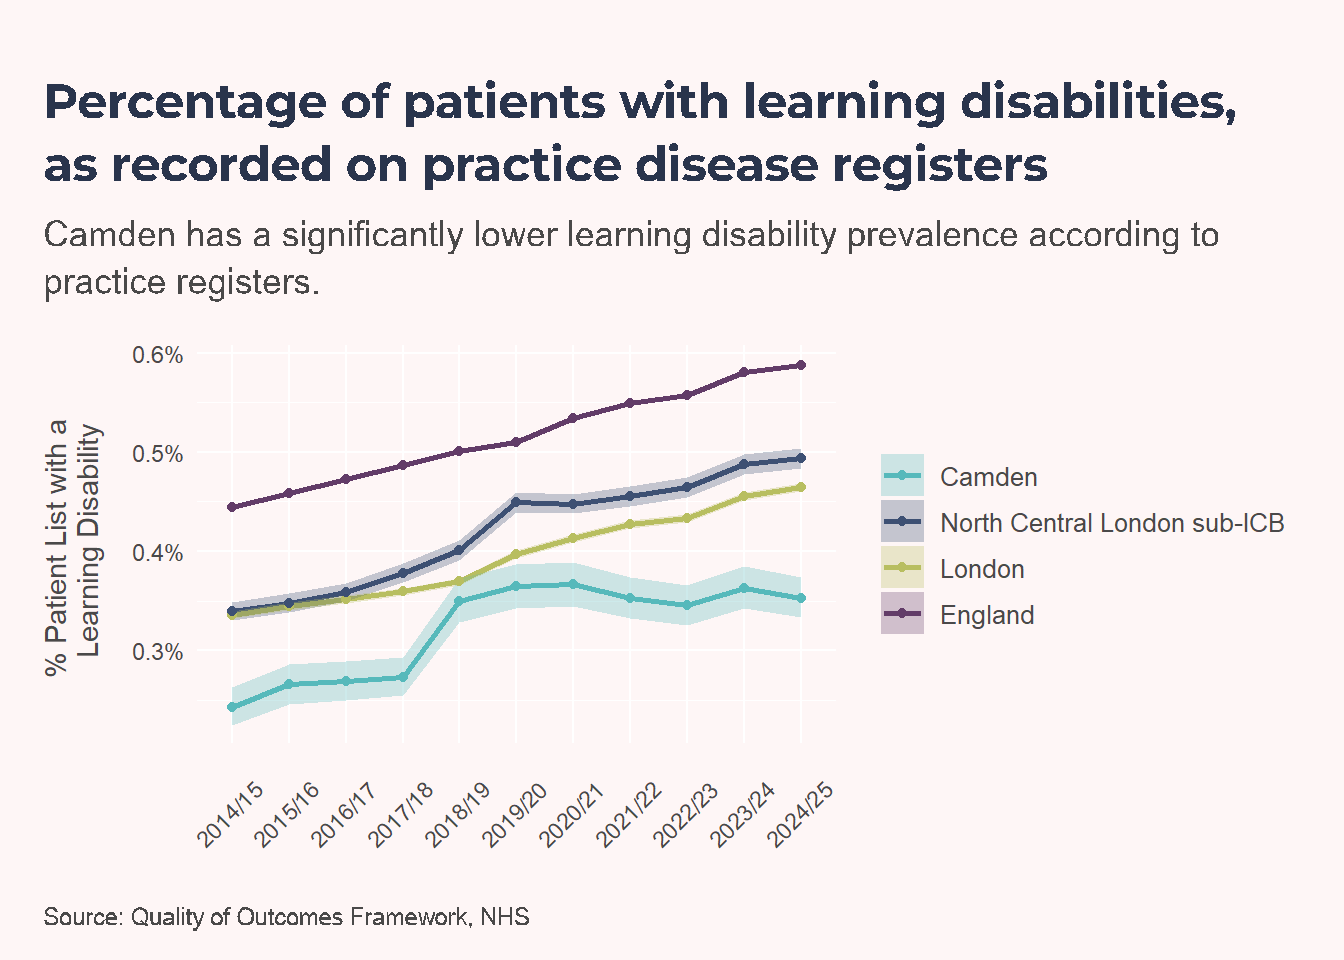
The most comprehensive identification data source of adults with a learning disability in England is the GP Learning Disability Register. The purpose of this register is to create a contact list to whom GPs can offer the free health checks to which they are entitled. According to this measure, 0.35% (n = 810) of people registered with a Camden GP had a learning disability. This is significantly lower than the values for NCL sub-ICB (0.49%), London (0.46%) and England (0.59%).
Using the Learning Disability Register as a proxy to estimate prevalence should be done cautiously. Camden could have a similar underlying prevalence to the other geographies, but a smaller proportion of its learning disability population may be known to a GP and therefore recorded on a practice register.
Between 2017/18 and 2018/19, there was a significant increase in the proportion of the patient list in Camden on the Learning Disability Register. However, since then the figure has plateaued while the proportion in all other geographies have continued to increase.
An alternative estimate for current prevalence uses ethnicity and mortality data to estimate need. PANSI applies the latest ONS sub-national population projections (2025) and a methodology developed by Emerson and Hatton (2004), with prevalence base rates adjusted for ethnicity and mortality.
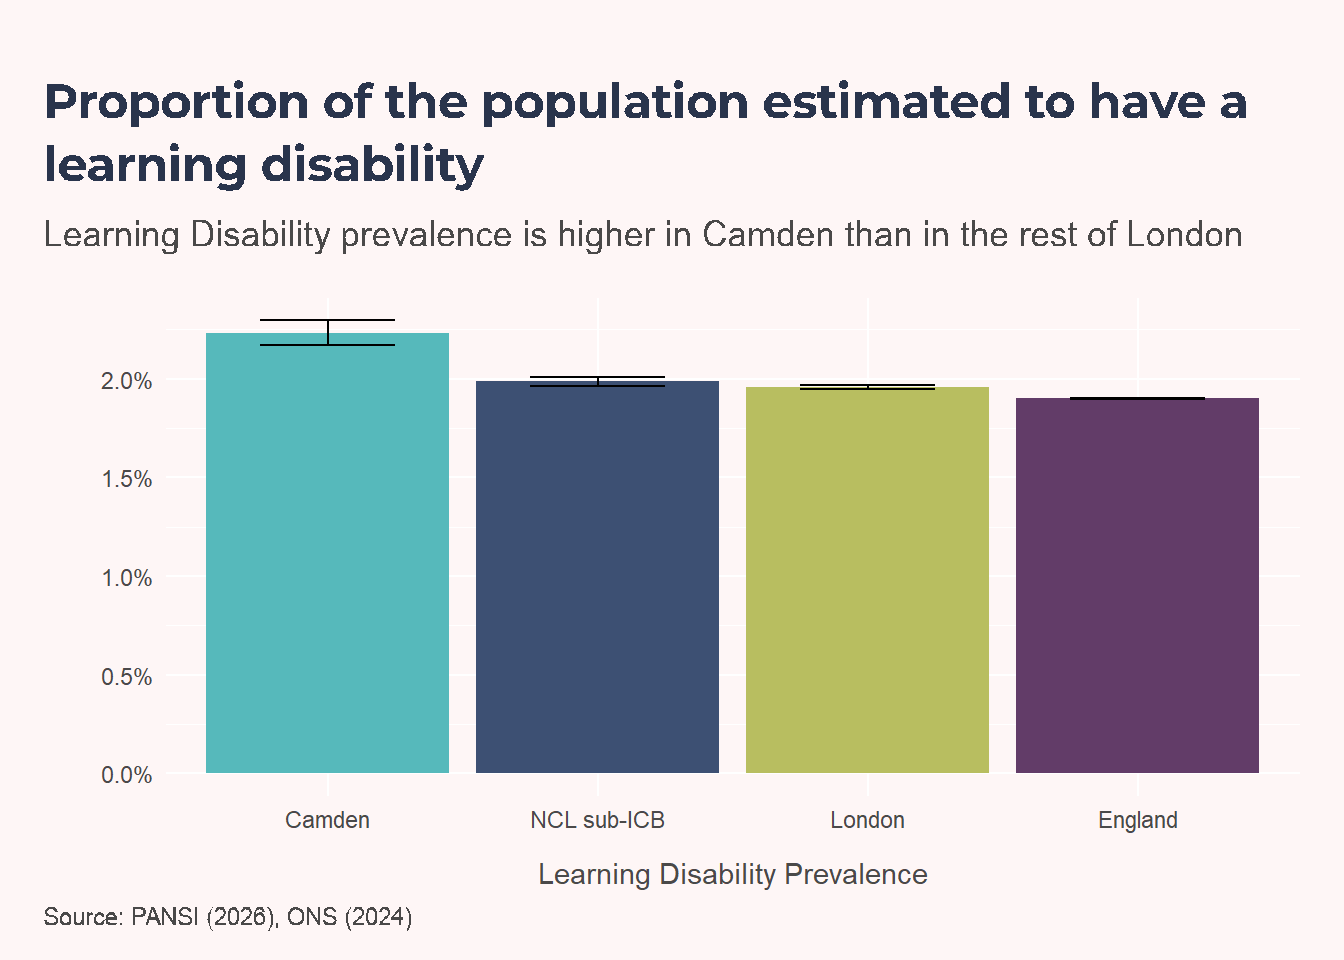
According to PANSI, there are 4,844 adults currently living in Camden who are estimated to have a learning disability. This is equivalent to 2.23% of the adult population, which is higher than the proportion estimated for North Central London (1.99%), London (1.96%) and England (1.90%).
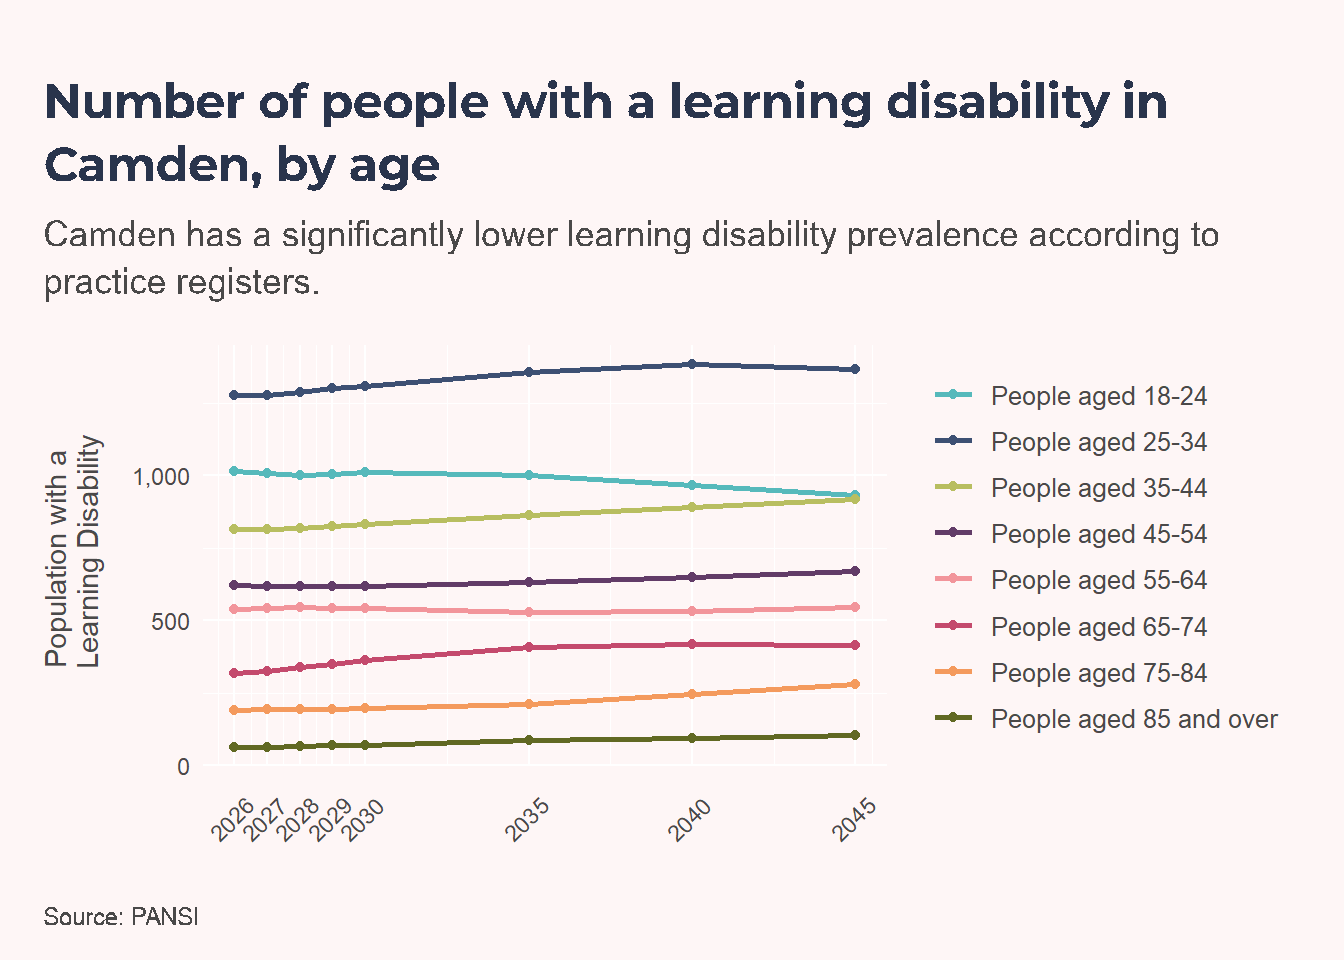
This difference is driven largely by Camden’s younger population profile, because PANSI assigns higher prevalence to younger adult age groups. However, PANSI does not adjust for an area’s local ethnic composition, so it may under-represent need in areas with higher-than-average South Asian populations and over-represent need in areas with lower-than-average South Asian populations (Emerson et al., 1997).
Projecting the population
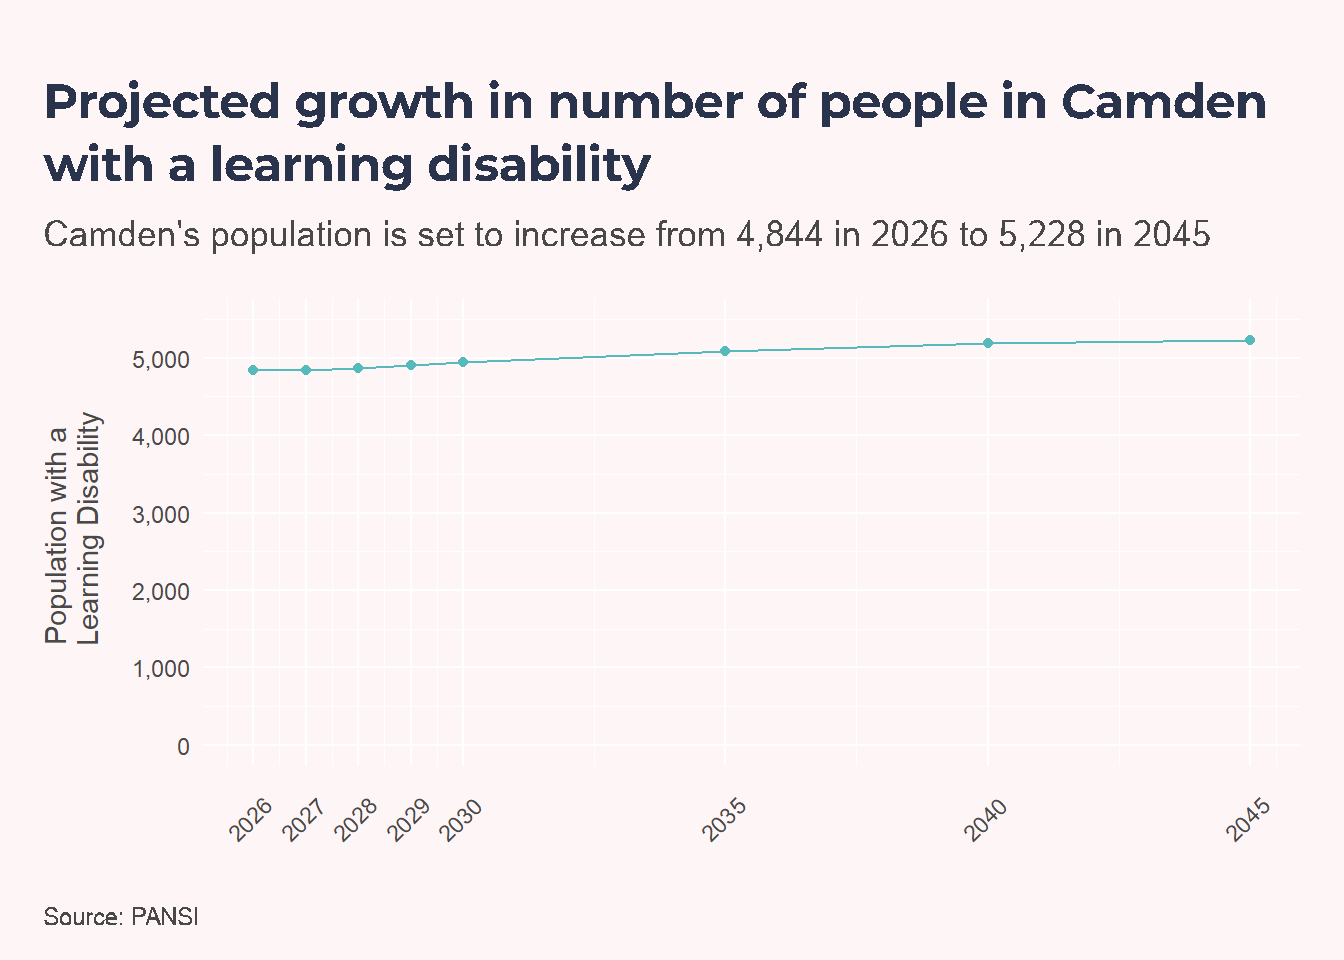
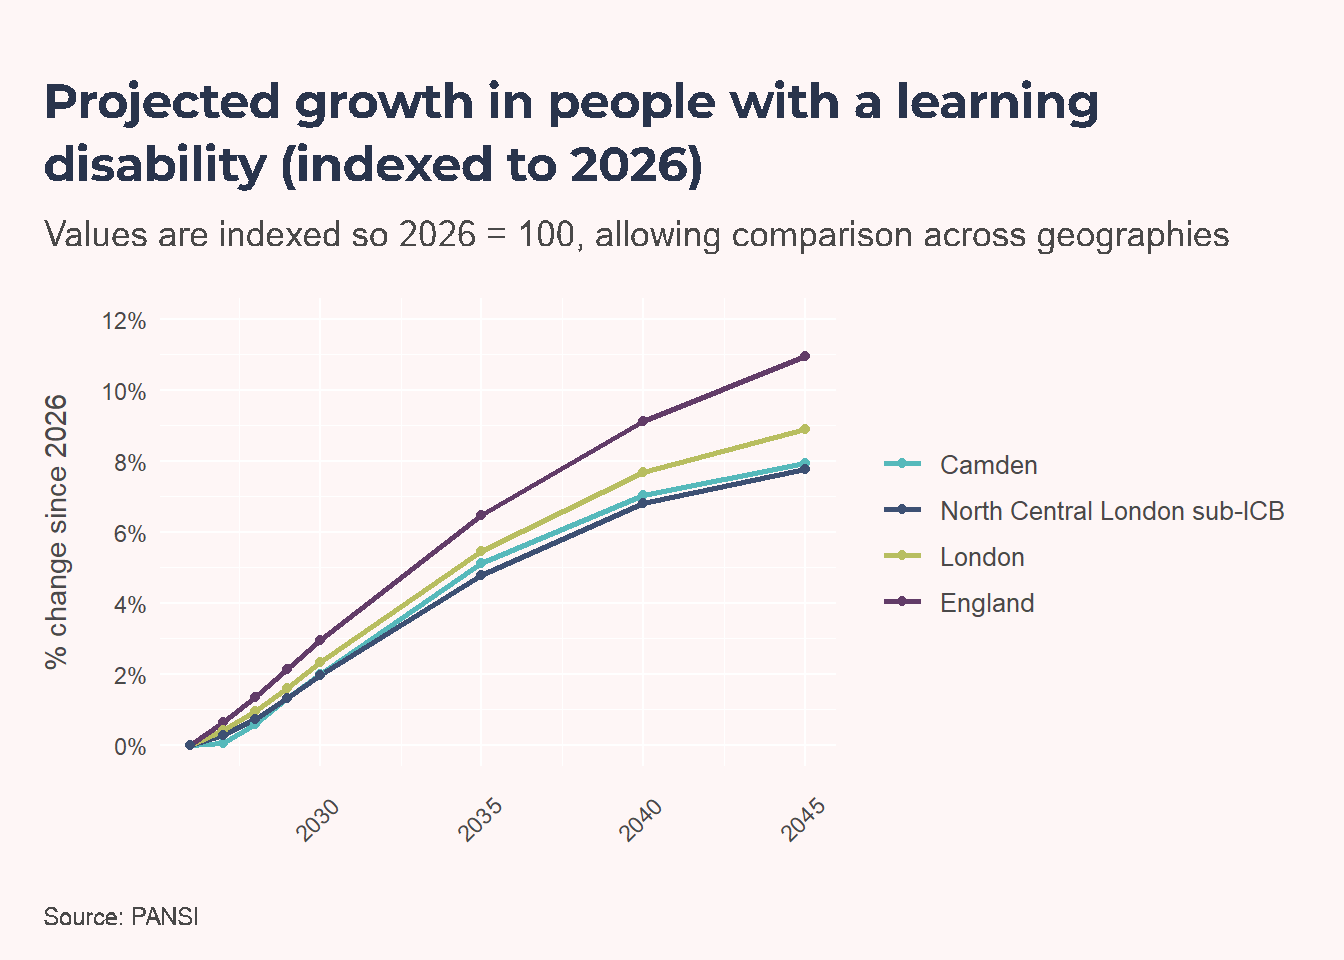
PANSI projections suggest growth in the number of adults with a learning disability in Camden from 4,844 in 2026 to 5,228 by 2045. In relative terms, Camden’s projected increase is 7.9%.
These projections are based on national modelling assumptions and are useful for planning. They are not derived from a Camden-specific measured prevalence estimate, so they should be interpreted as scenario estimates rather than a direct measure of local underlying prevalence.
Health
Prevention and annual health checks (AHCs)
Annual health checks (AHCs) for people with a learning disability (PWLD) are a free NHS review offered every year to everyone aged 14+ on their GP’s learning disability register, designed to identify health needs early and ensure appropriate treatment and support. They help address the poorer physical and mental health outcomes experienced by PWLD by detecting previously unrecognised conditions and developing personalised health action plans. AHCs are distinct from the general NHS Health Check programme for adults aged 40 to 74.
Camden’s annual health check coverage is higher than comparator areas
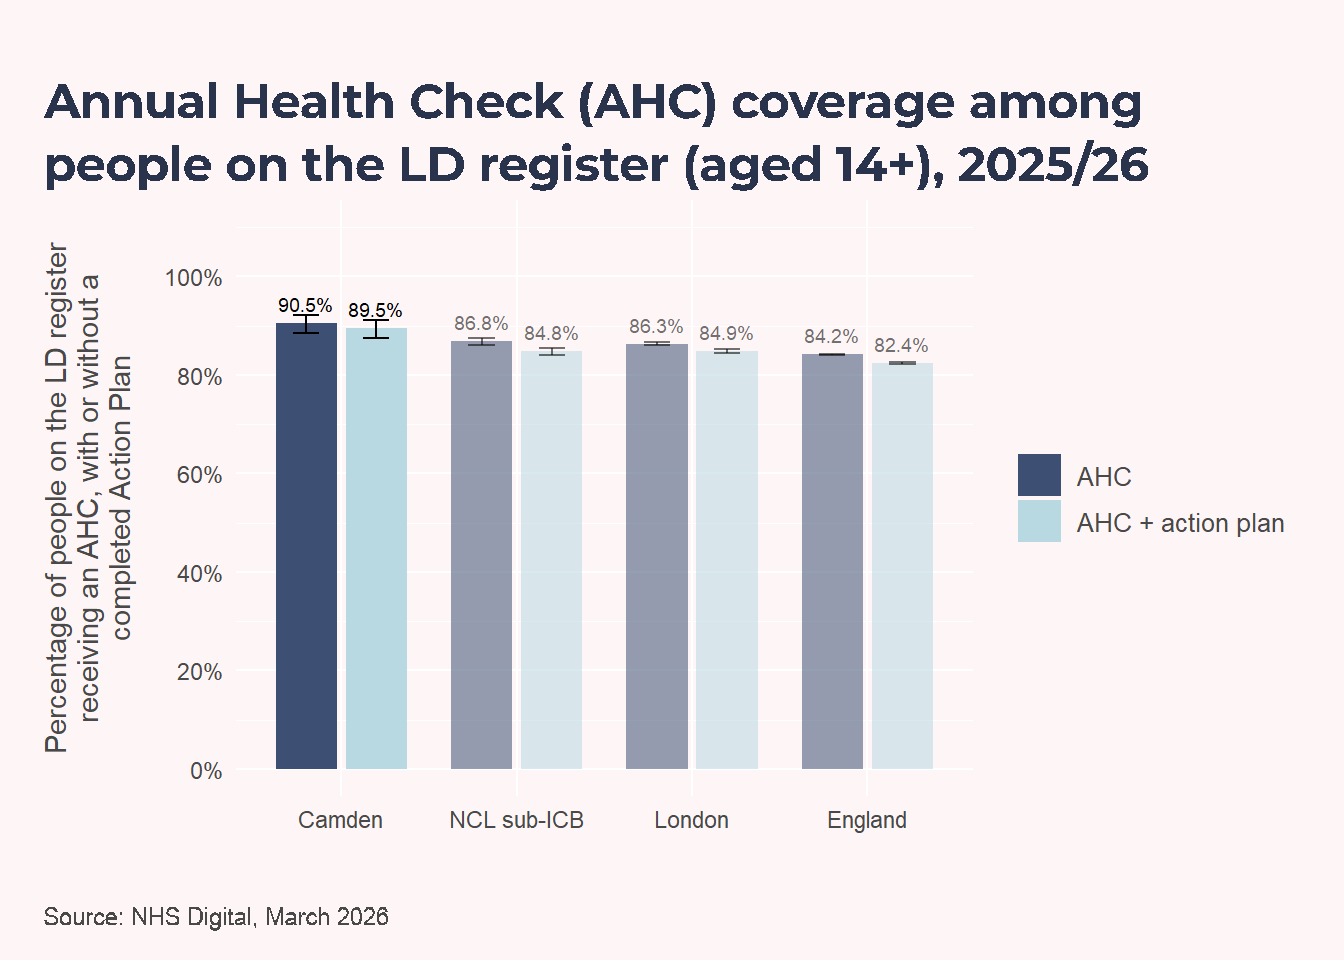
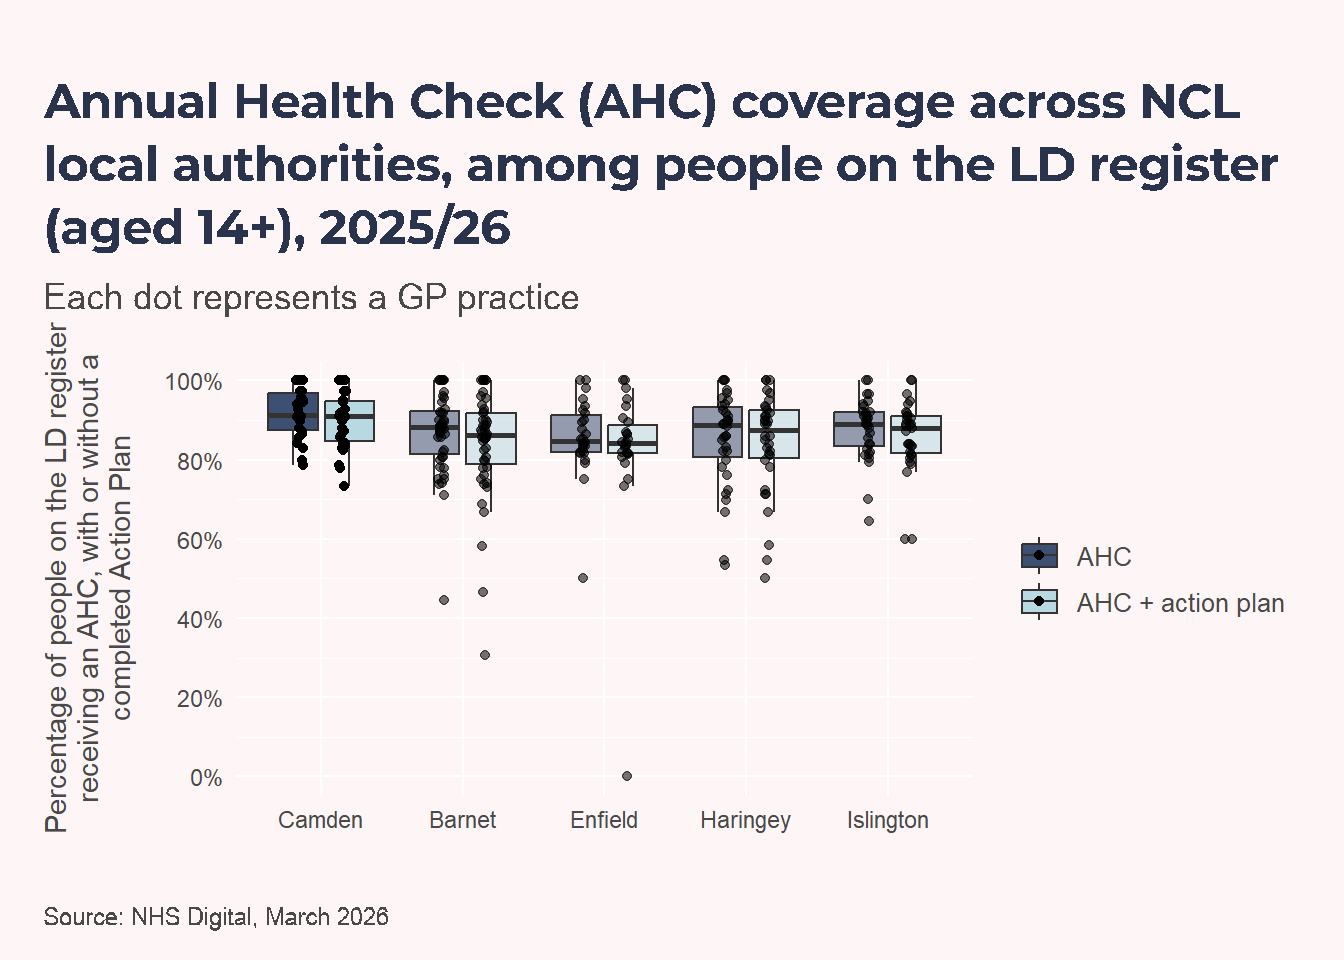
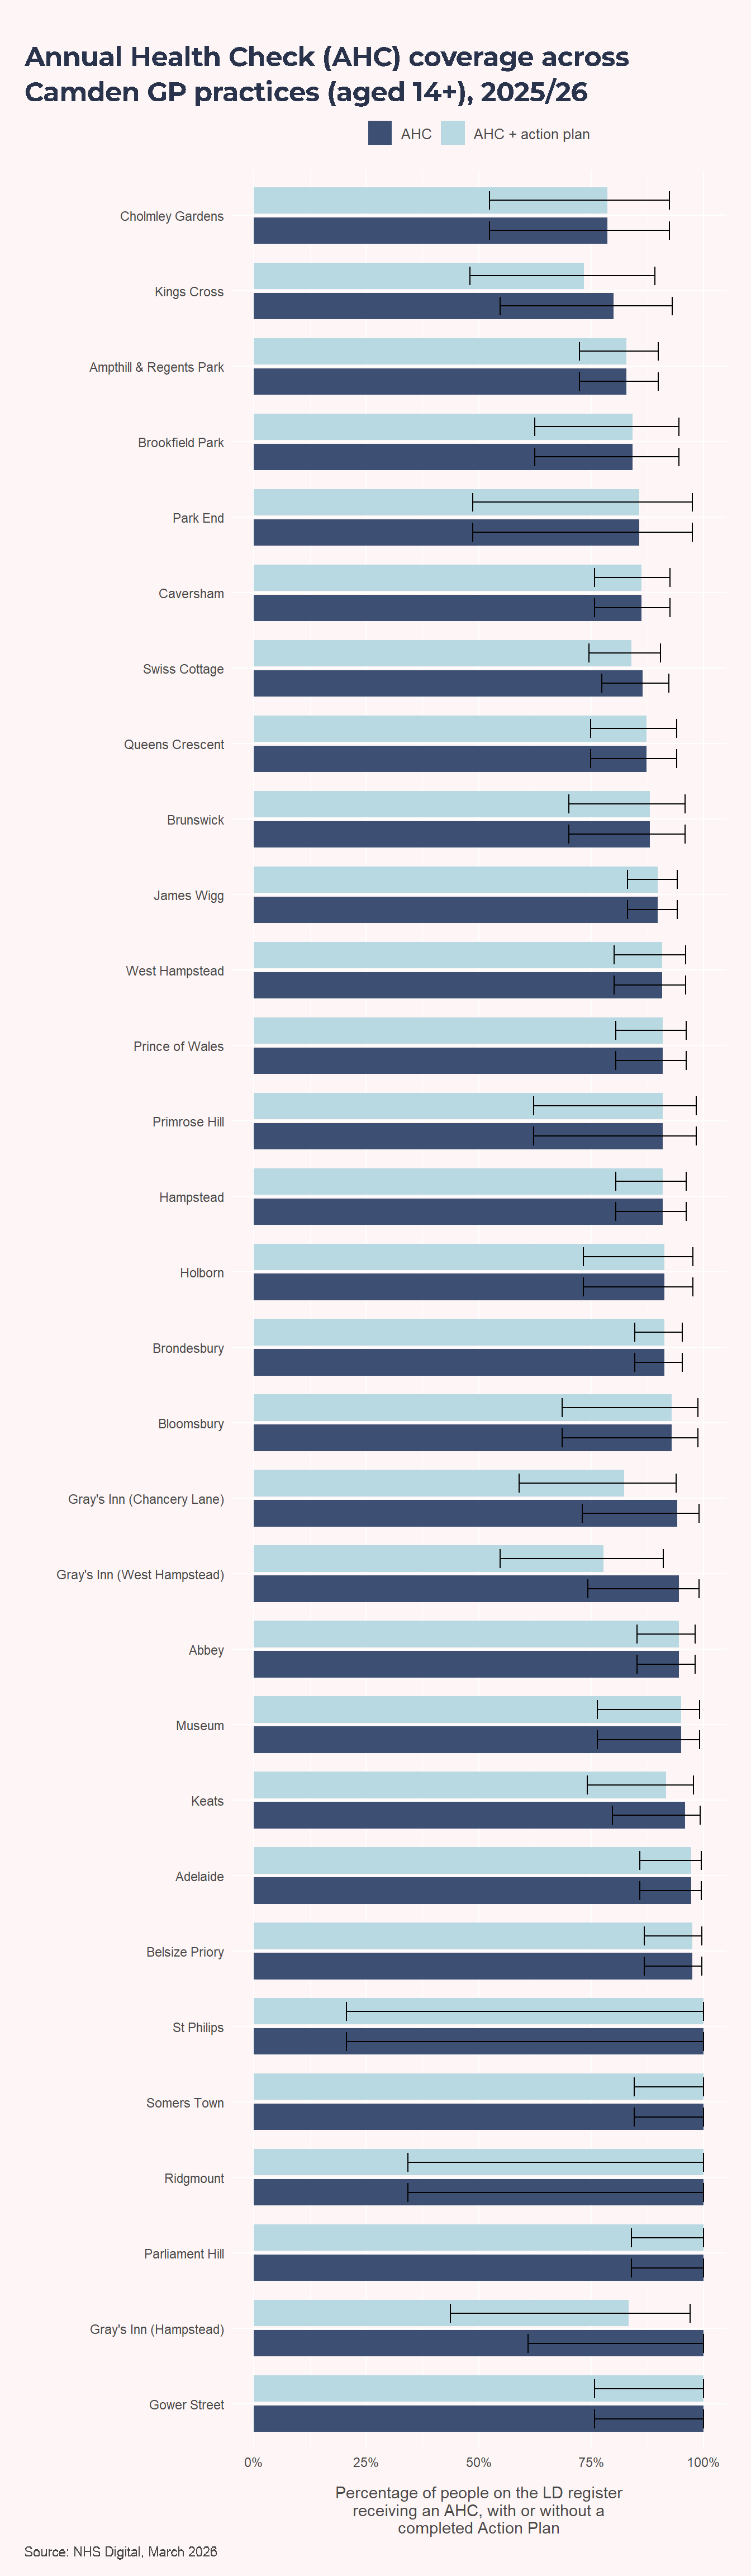
Across both the AHC-only and AHC plus action plan measures, Camden had significantly higher completion rates than England, London, and NCL sub-ICB. In 2025/26, 90.5% (958 of 1,059) of people on Camden’s learning disability register received an annual health check. 89.5% (948 of 1,059) had a completed health action plan alongside their annual health check.
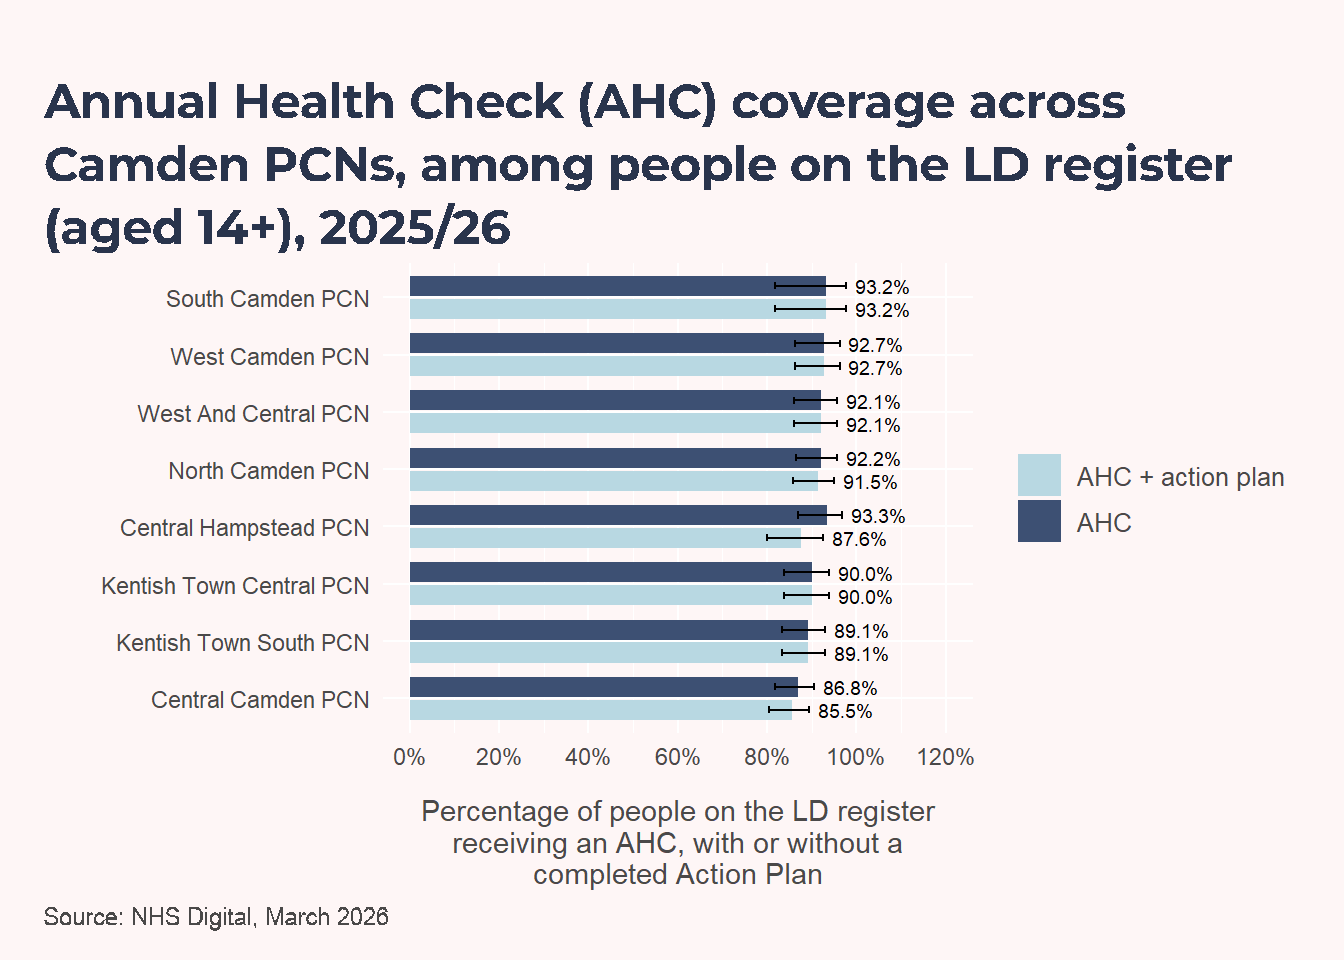
At PCN level, completion ranged from 86.8% in Central Camden PCN to 93.3% in Central Hampstead PCN for annual health checks, and from 85.5% in Central Camden PCN to 93.2% in South Camden PCN for completed health action plans.
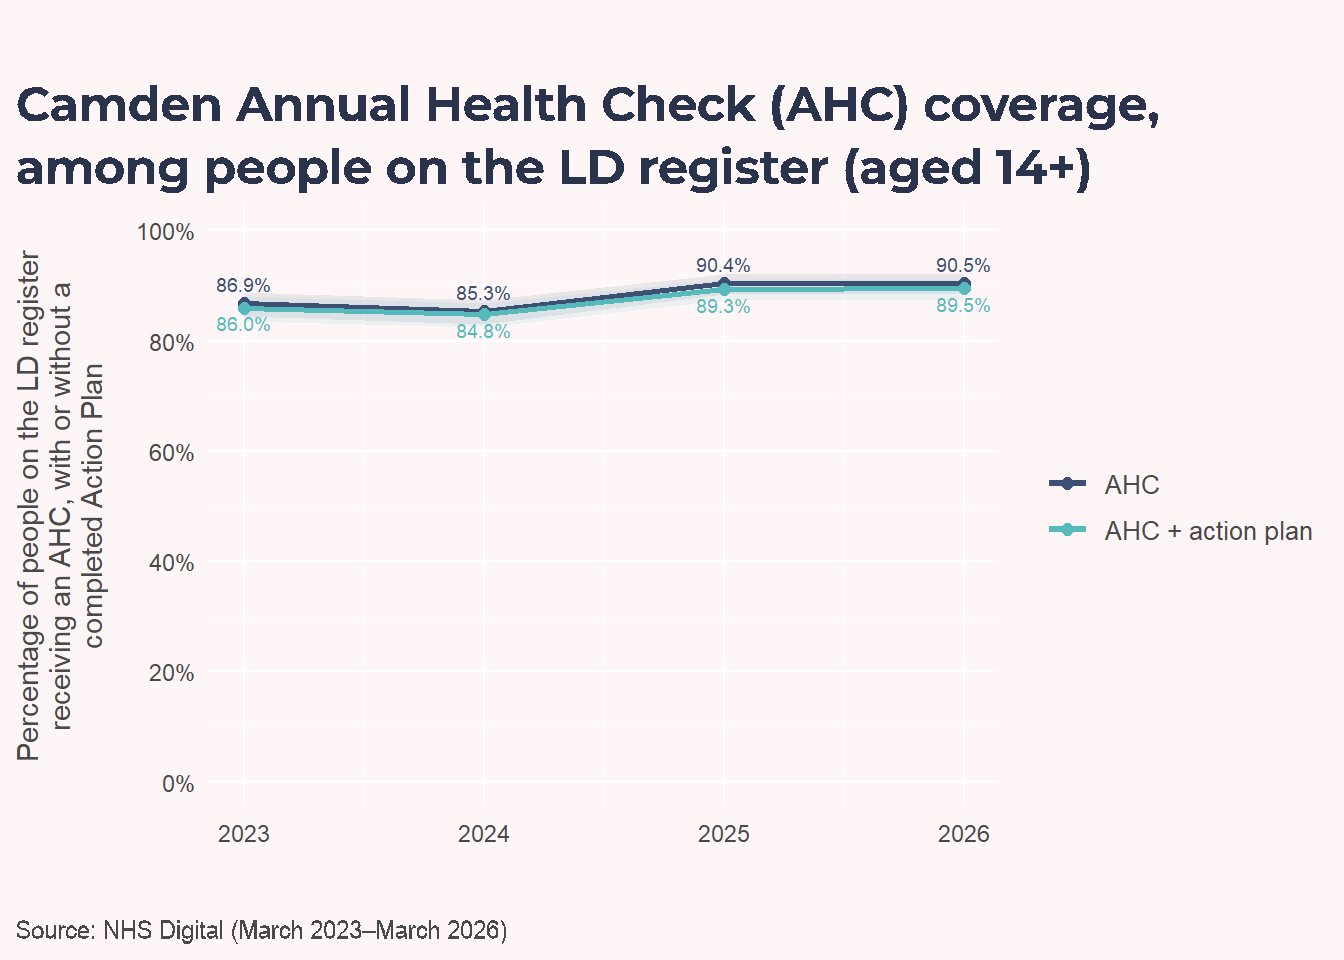
Camden’s AHC completion rate has increased since 2023
NoteTechnical Note
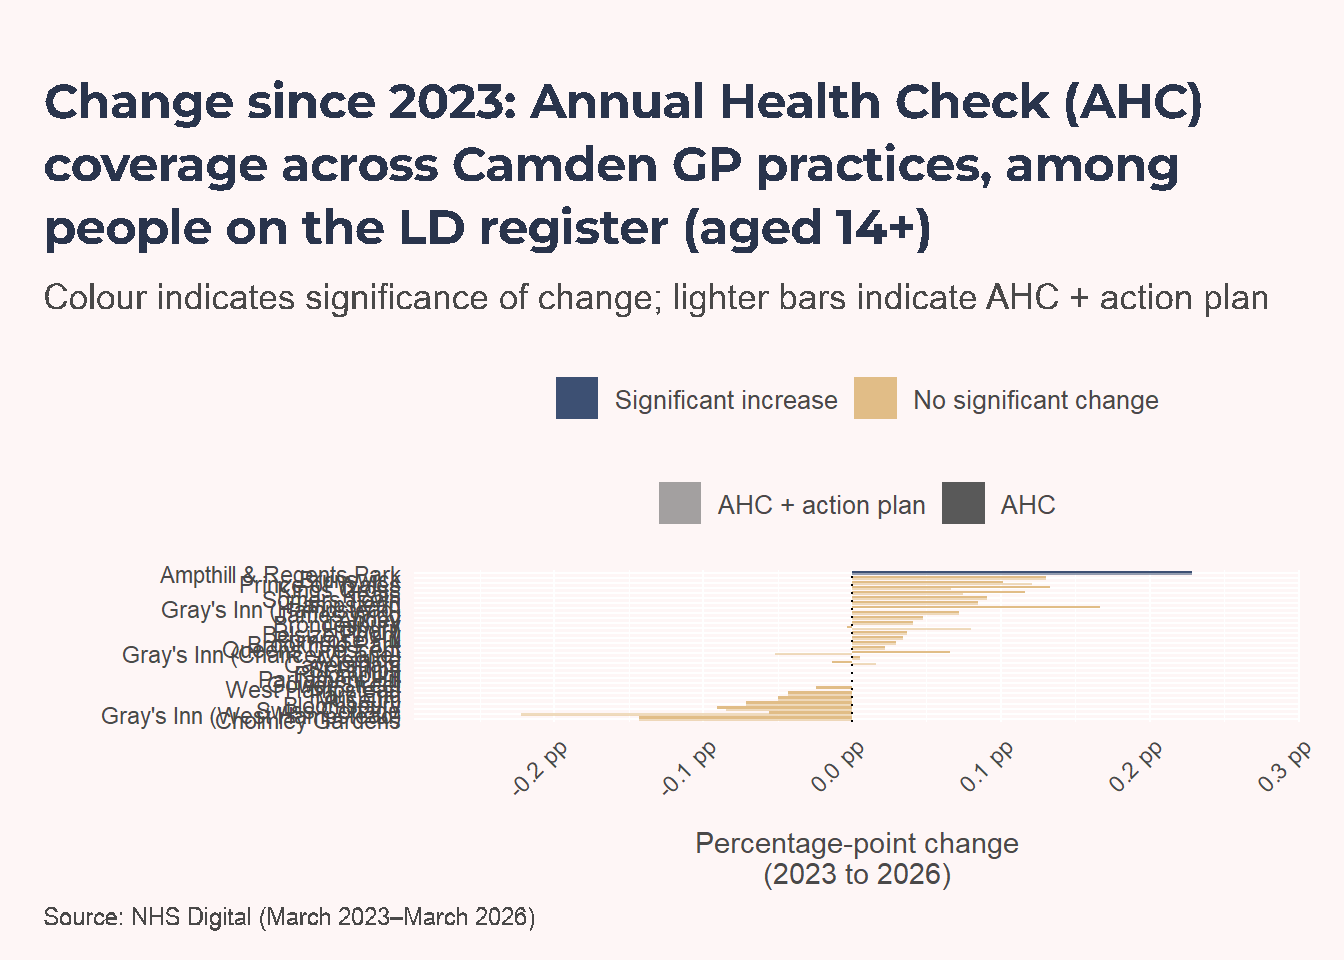
From March 2023 onwards, NHS Digital changed the LD AHC data structure to indicator-based records with explicit numerator and denominator fields. March 2022 uses legacy coding with a different structure, so it is less directly comparable with later files. To keep methods consistent across years, these change plots use a 2023 baseline.
These change charts take 2023 as their baseline, as this is the earliest year which can be reasonably compared with 2026, due to coding changes. Across both measures (with and without a completed health action plan), 29 practices show no significant change, 0 show a significant decrease, and 1 practice shows a significant increase in coverage: Ampthill & Regents Park, by 22.9 percentage points.
In the last 3 years, the Annual health checks completion rate has increased significantly (86.9% in 2023 to 90.5% in 2026; 3.6 percentage points). In the last 3 years, the annual health checks with completed health action plan completion rate has also increased significantly (86.0% in 2023 to 89.5% in 2026; 3.6 percentage points).
Co-occurring conditions and prescribing (NCL, 2024/25)
NoteData Availability
At the time of writing, Camden-level primary care data were not available to Camden Public Health Intelligence due to ongoing migration of data to the Snowflake platform. Once these data become available, this section will be updated with a Camden-specific analysis including, where possible within statistical disclosure limitations, additional demographic breakdowns such as ethnicity and deprivation.
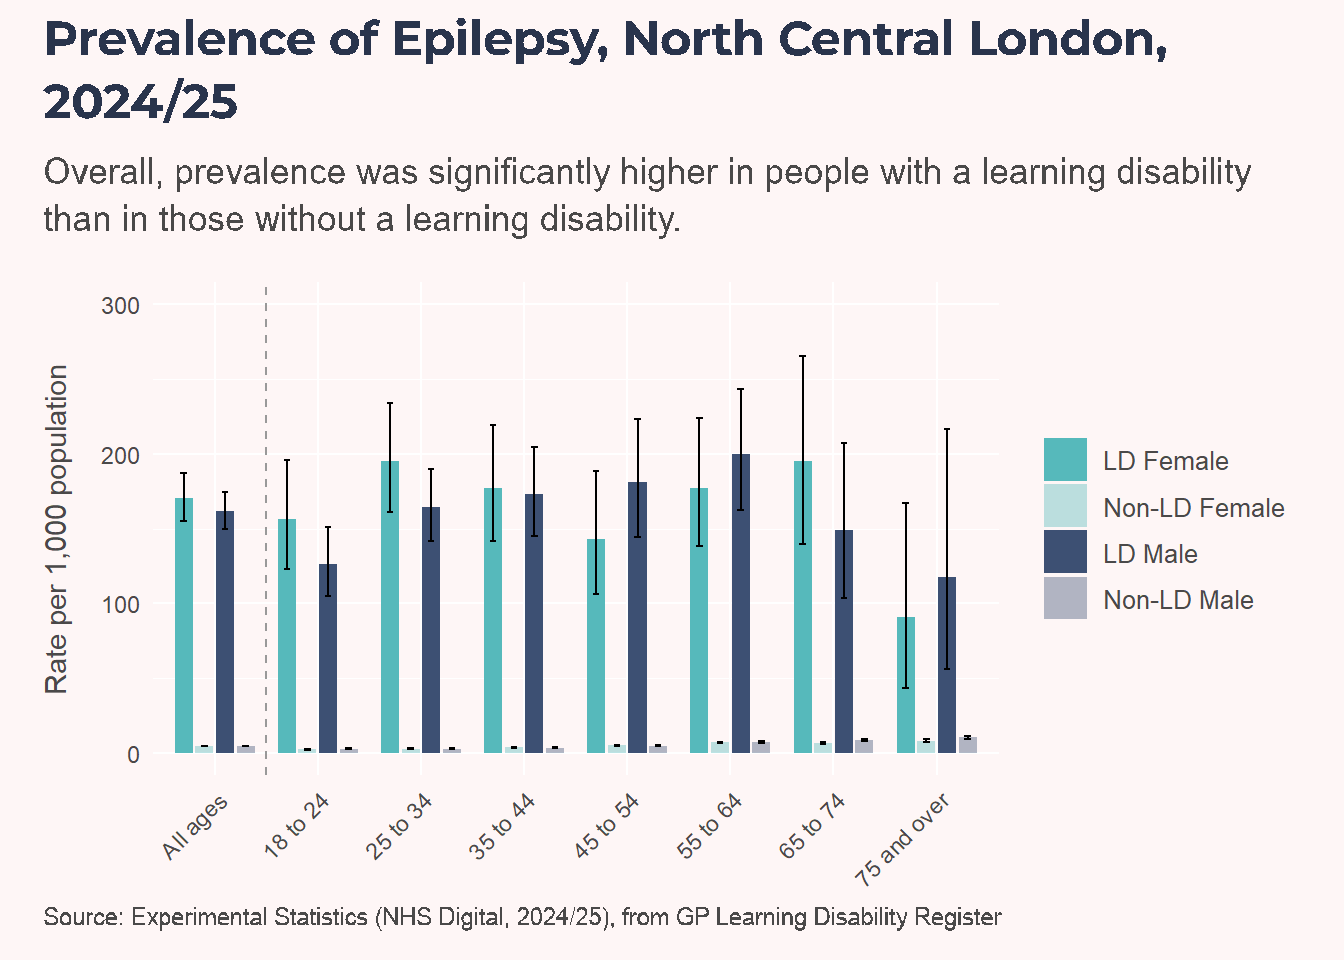
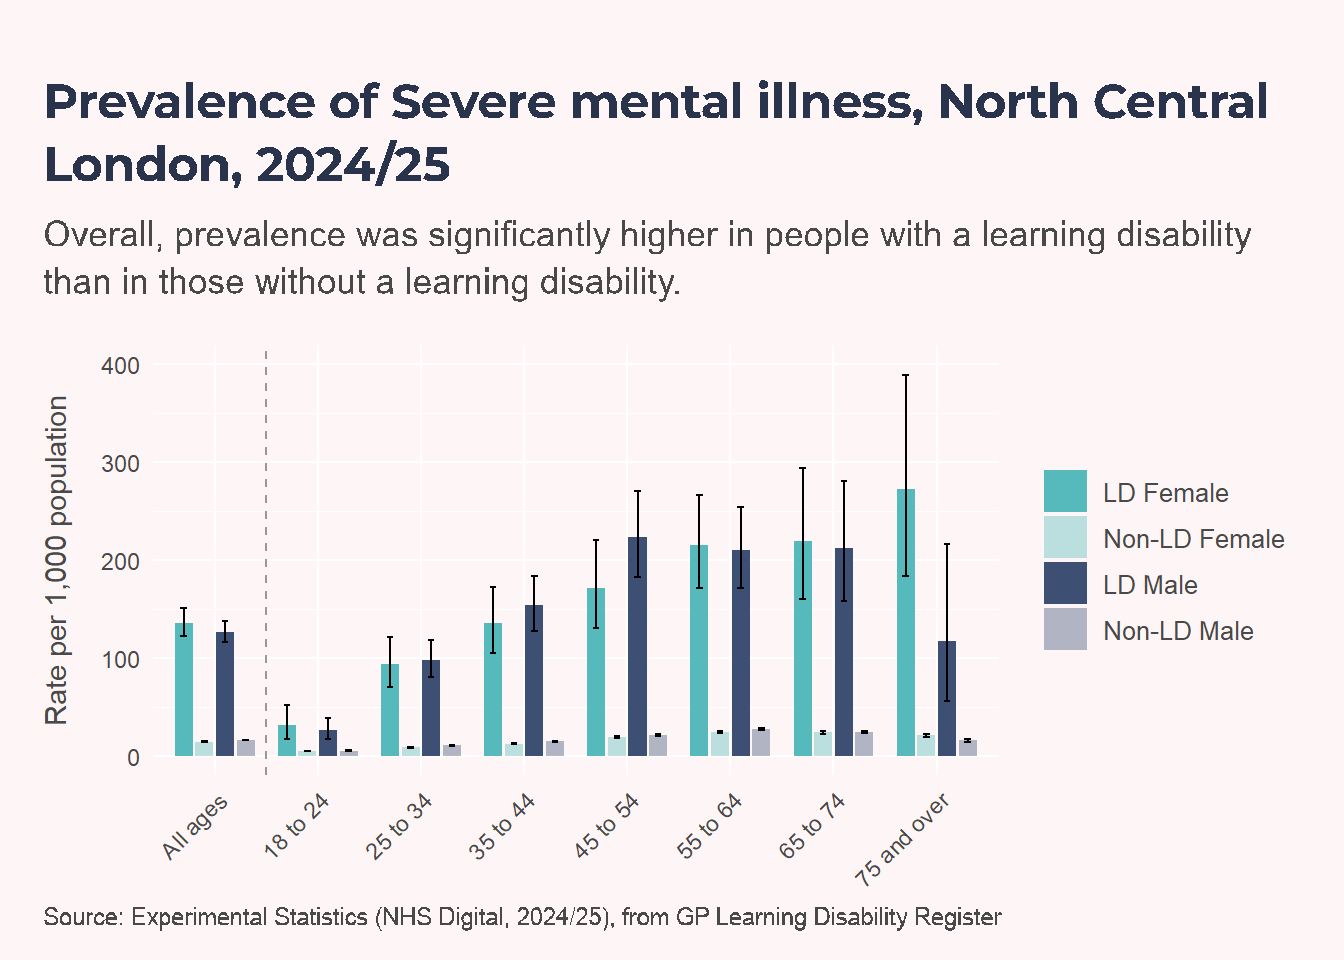
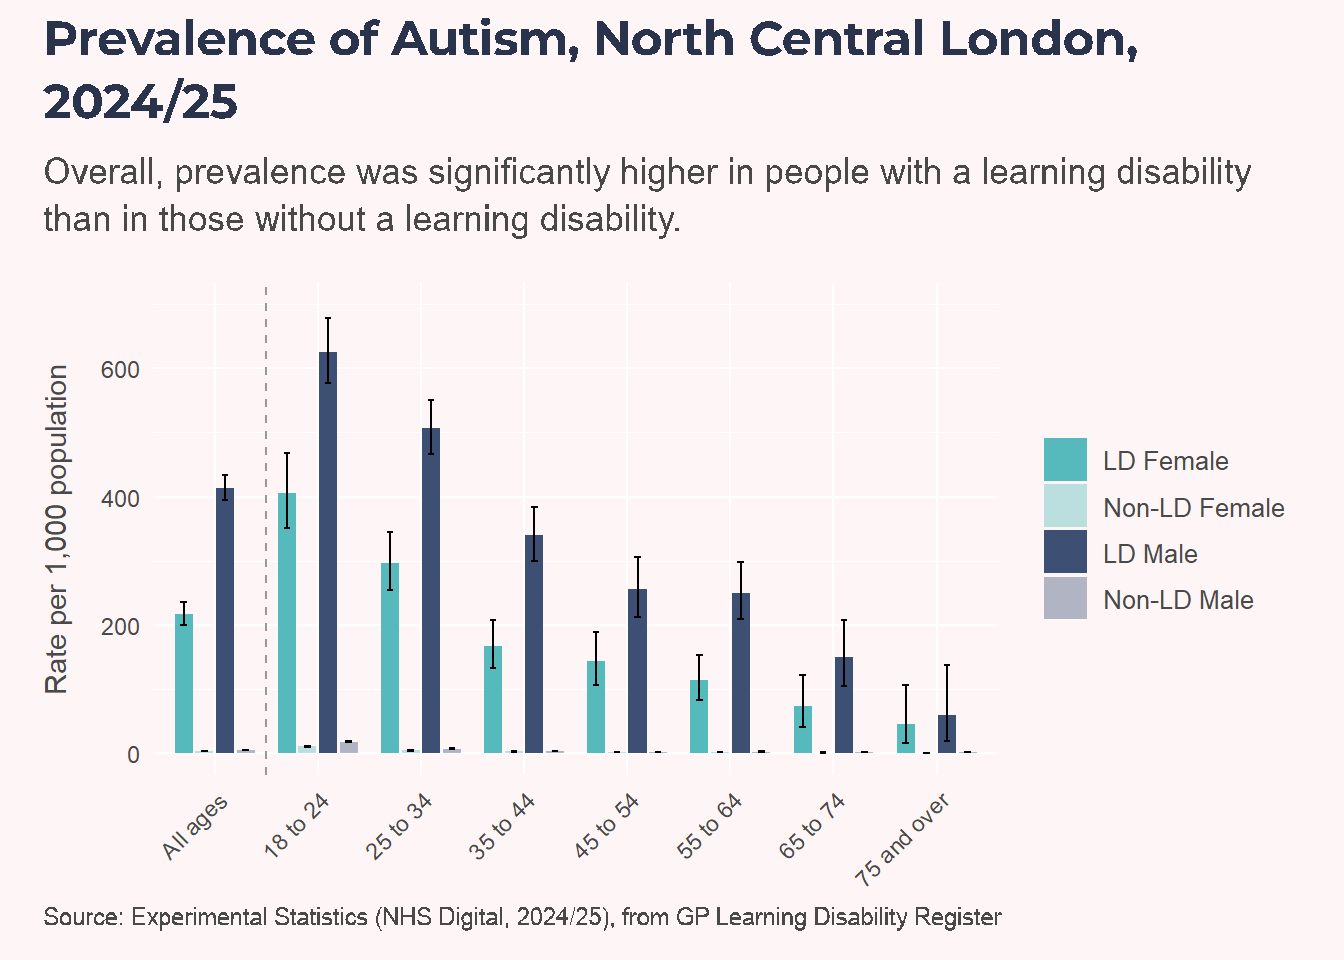
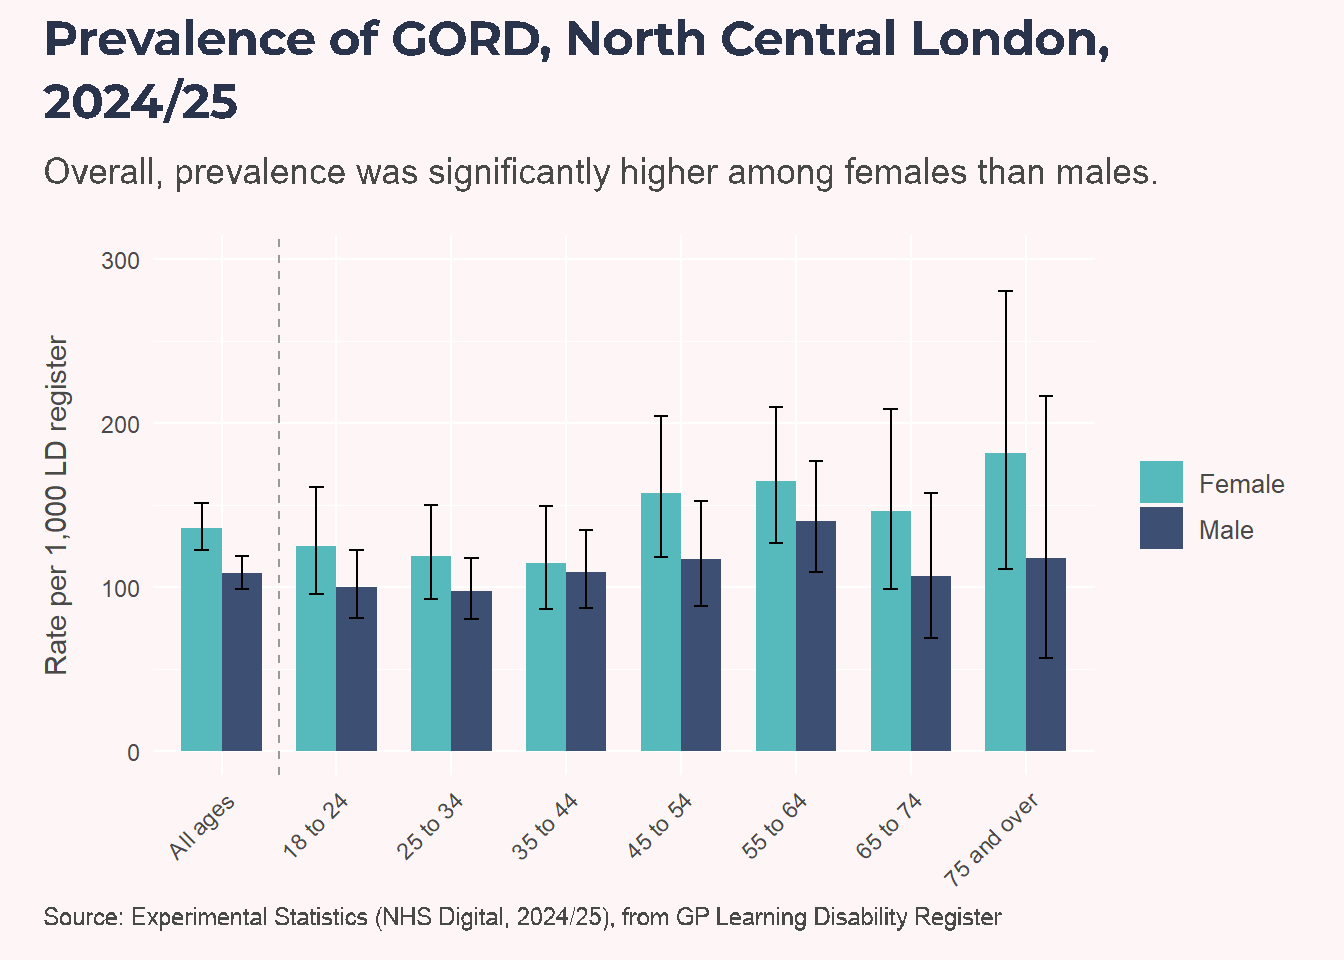
In the meantime, this section uses NHS England’s Health and Care of PWLD Experimental Statistics (2024/25). These statistics are derived from the same underlying primary care dataset but, as a public release, are only available at Sub-ICB Location level. As a result, findings are presented for North Central London rather than Camden and are limited to breakdowns by age and sex.
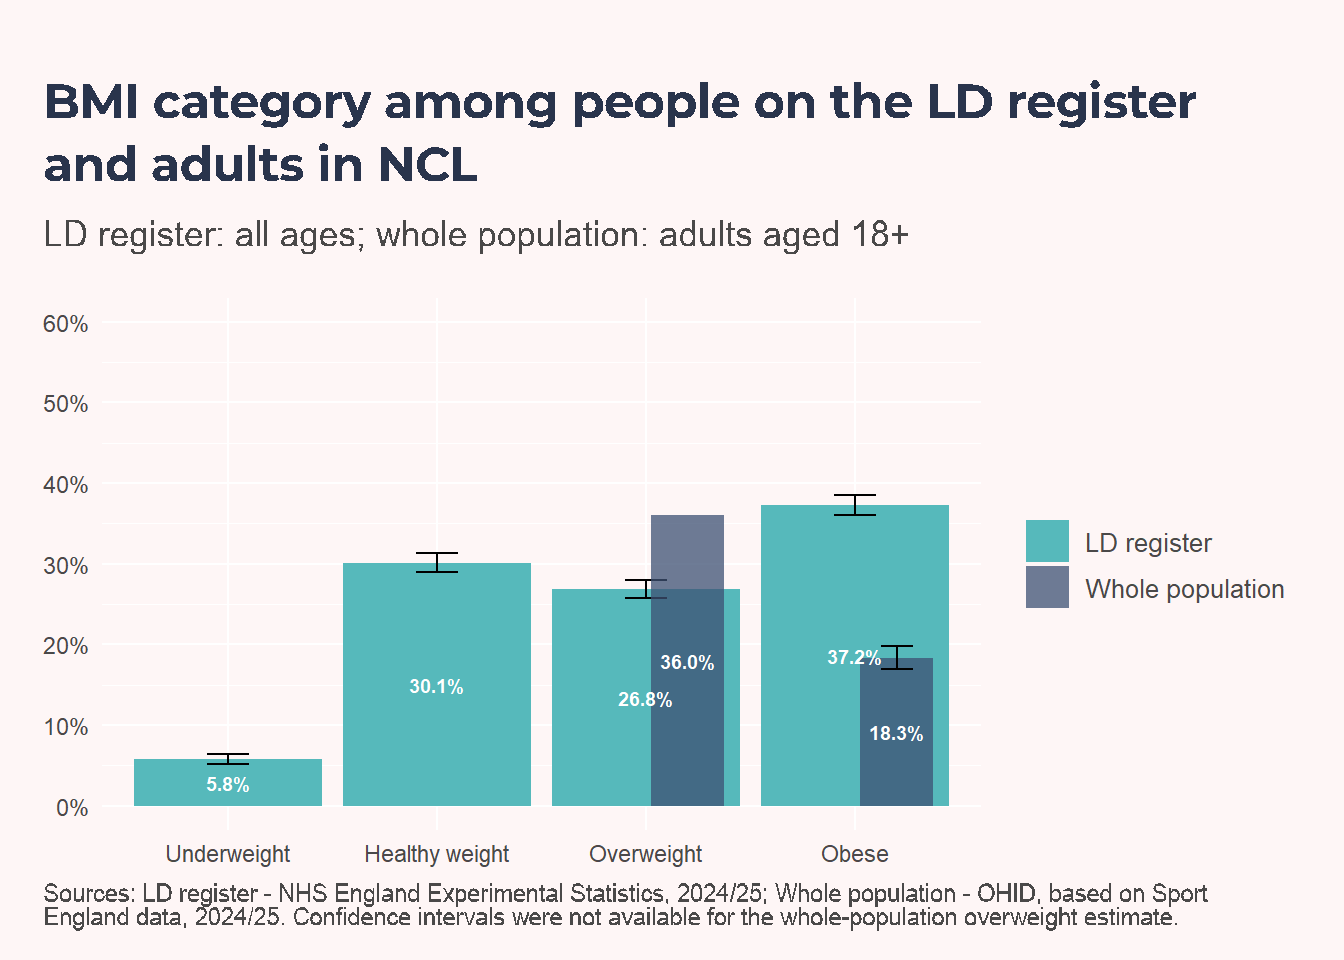
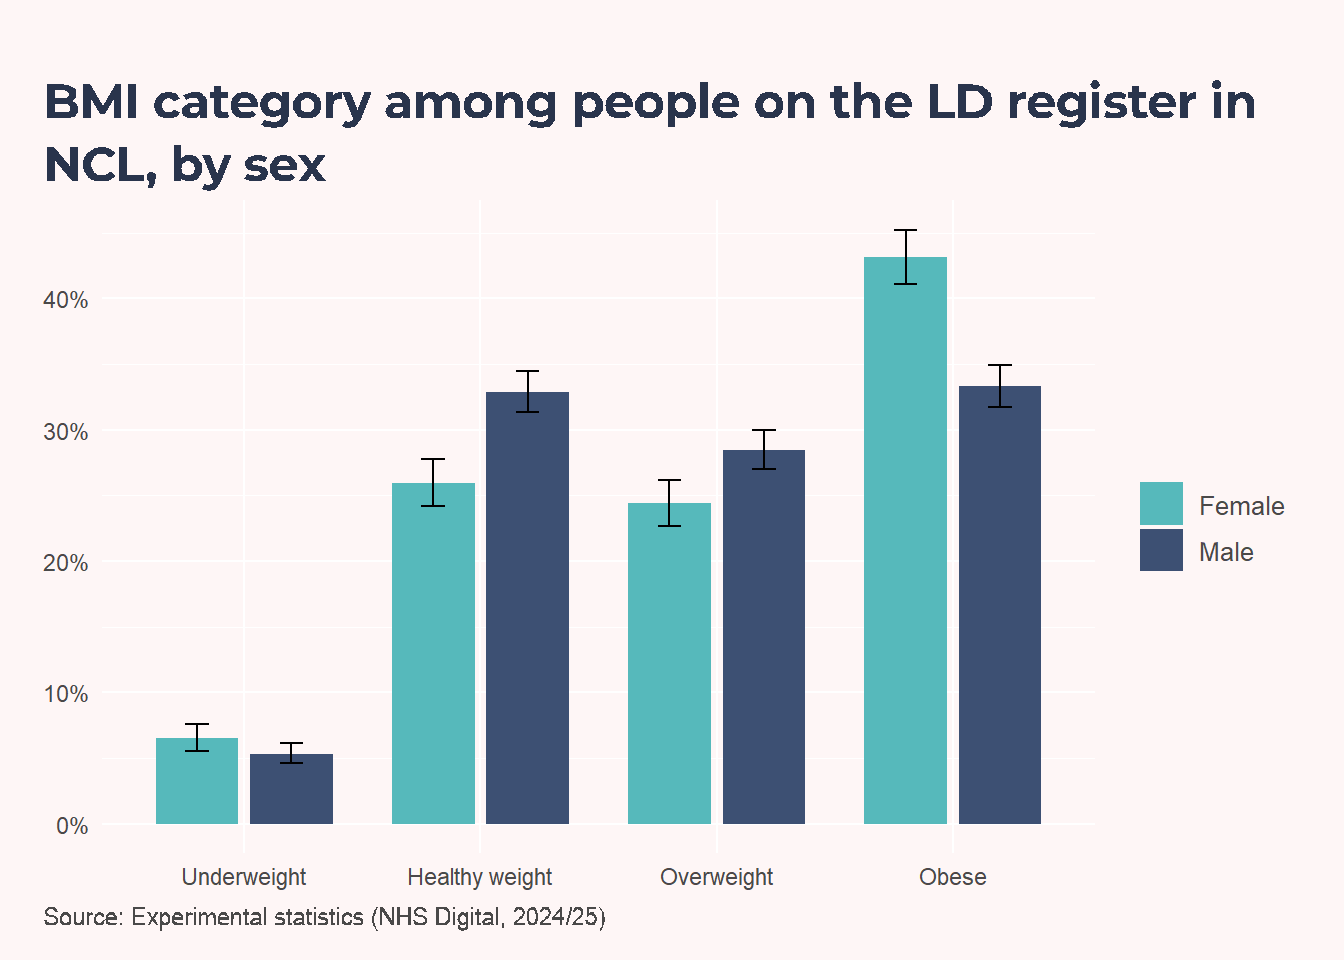
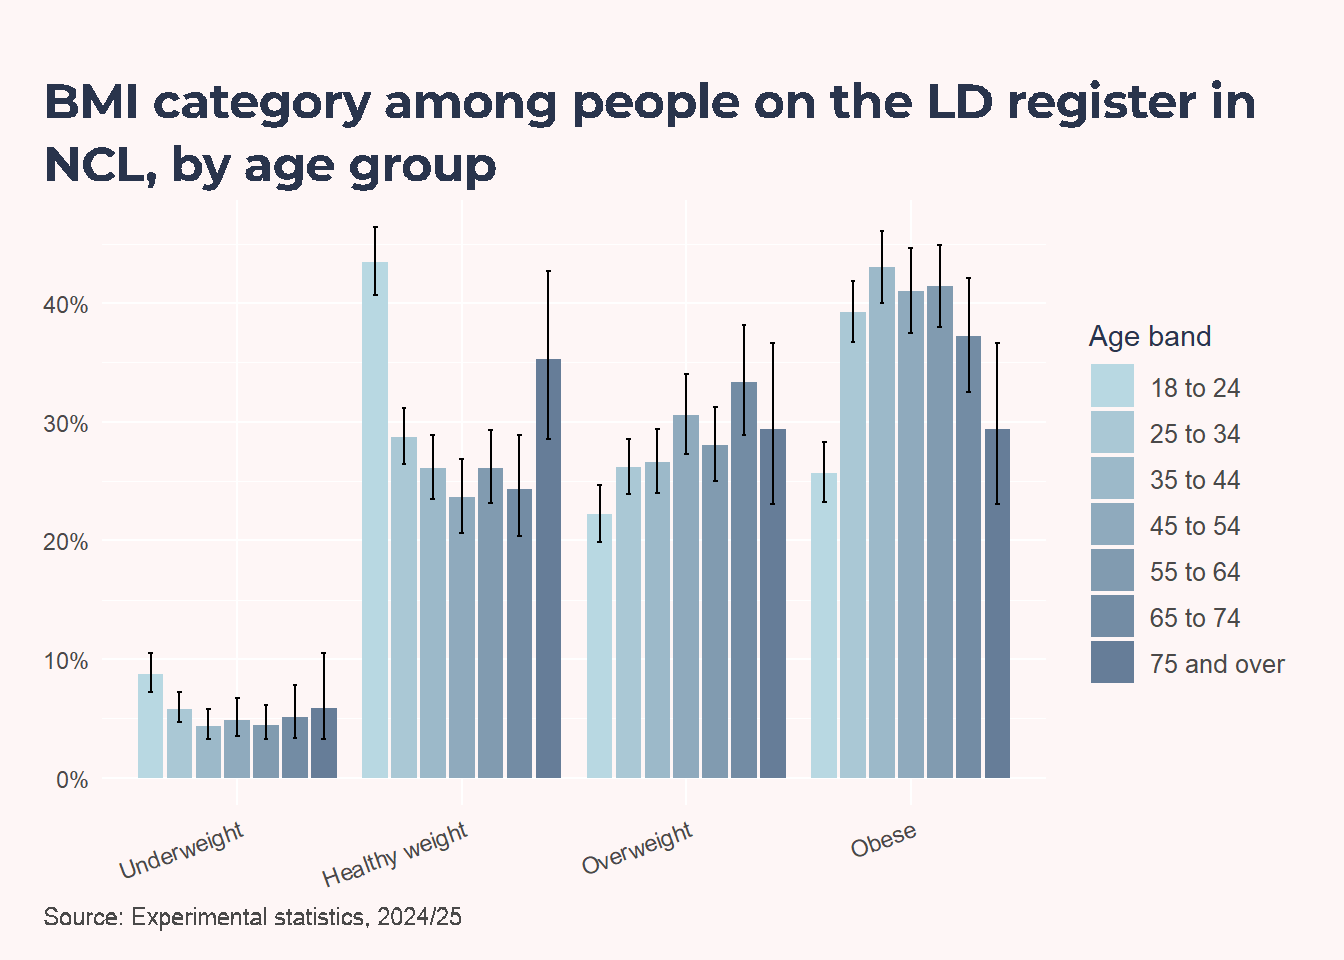
PWLD are less likely to be overweight, but more likely to be obese
In 2024/25, 64.1% of people on the NCL learning disability register were overweight or obese, compared with 54.4% of the whole NCL adult population.
On the LD register, 37.2% were obese, compared with 18.3% of the whole NCL adult population. Women were significantly more likely to be obese than men (43.2% versus 33.3%) and significantly less likely to be a healthy weight (26.0% versus 32.9%).
Underweight was more common in younger age bands, with year olds showing underweight and healthy weight. Overweight and obesity were most concentrated around the 45 to 54 age band, but these rates fall in the oldest groups because reaching older ages implies a comparatively healthier underlying profile.
People with a learning disability are more likely to have type 2 diabetes
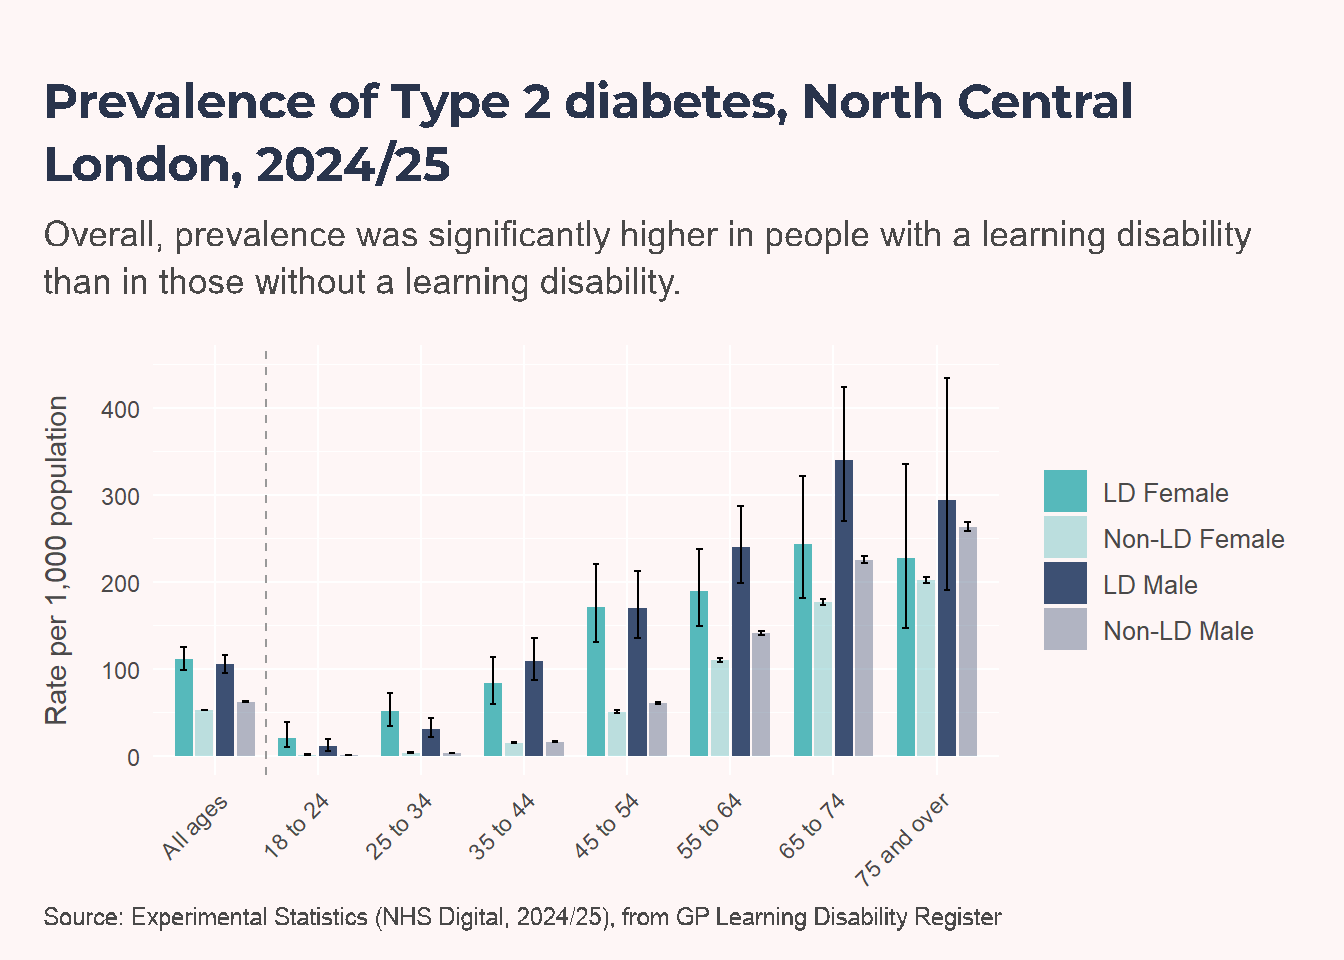
107 per 1,000 people on the LD register had type 2 diabetes, compared with 57 per 1,000 in the general population. Risk tended to increase with age. Only in the 65 to 74 age group was the difference between sexes statistically significant; rates were higher in males (p = 0.035). Differences were not statistically significant in the other age groups. These comparisons use two-sided tests at the 5% significance level.
The risk of type 2 diabetes increases linearly with an increase in BMI, and type 2 diabetes can be ameliorated and even normalised with adequate weight loss.[@Gatineau2014] In England, 90% of adults with type 2 diabetes are overweight or obese.[@Gatineau2014] The presence of obesity with type 2 diabetes increases morbidity and mortality from both conditions. Excess adiposity accentuates insulin resistance and complicates the treatment of type 2 diabetes.[@BMJ2011] The risk of diabetes-based mortality is doubled in those with a learning disability.[@WingMathur2025]
PWLD are over-prescribed psychotropic medication
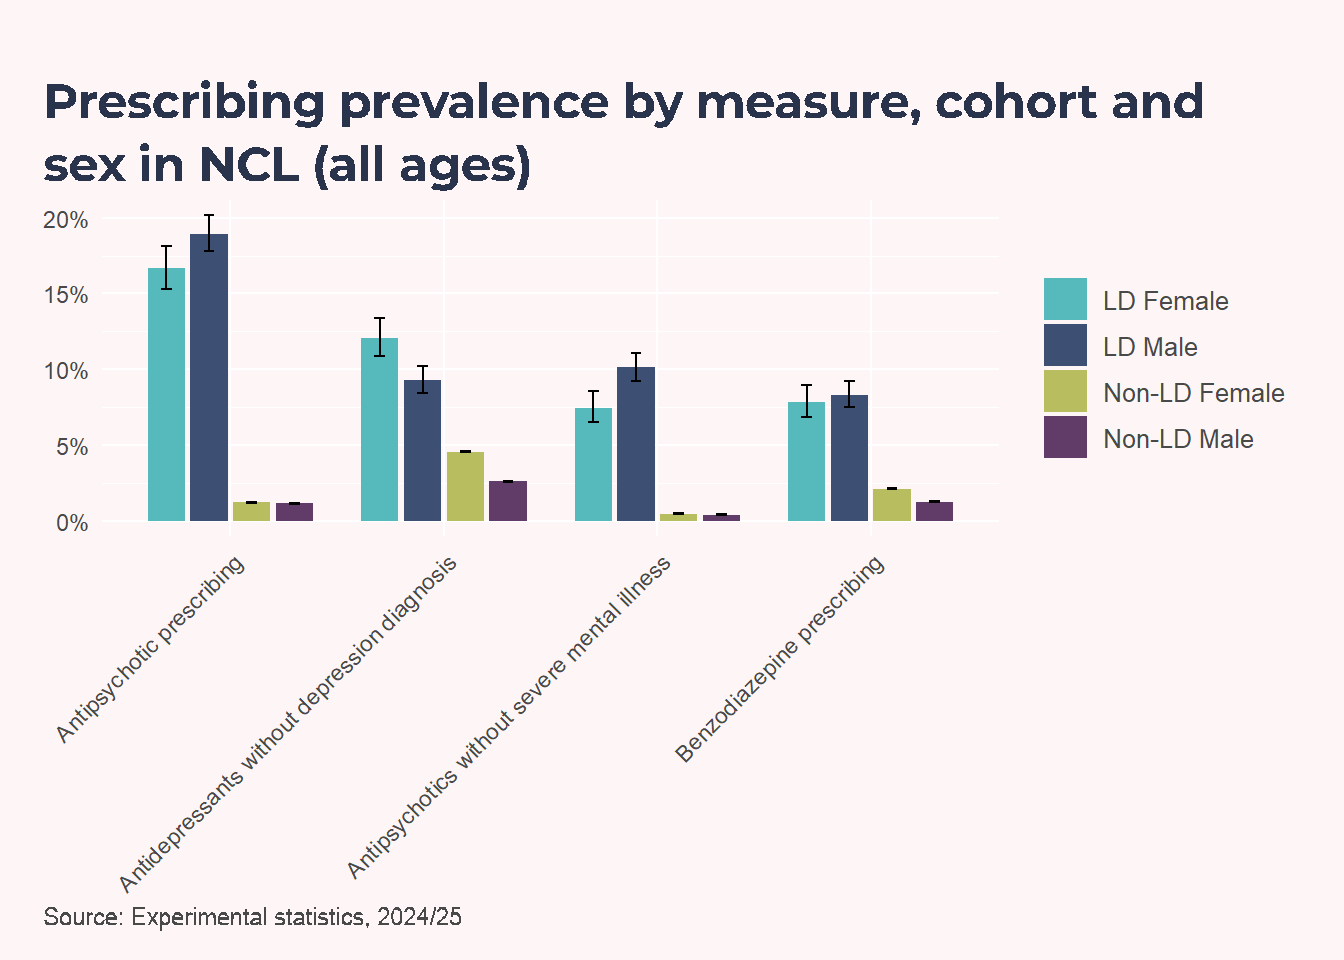
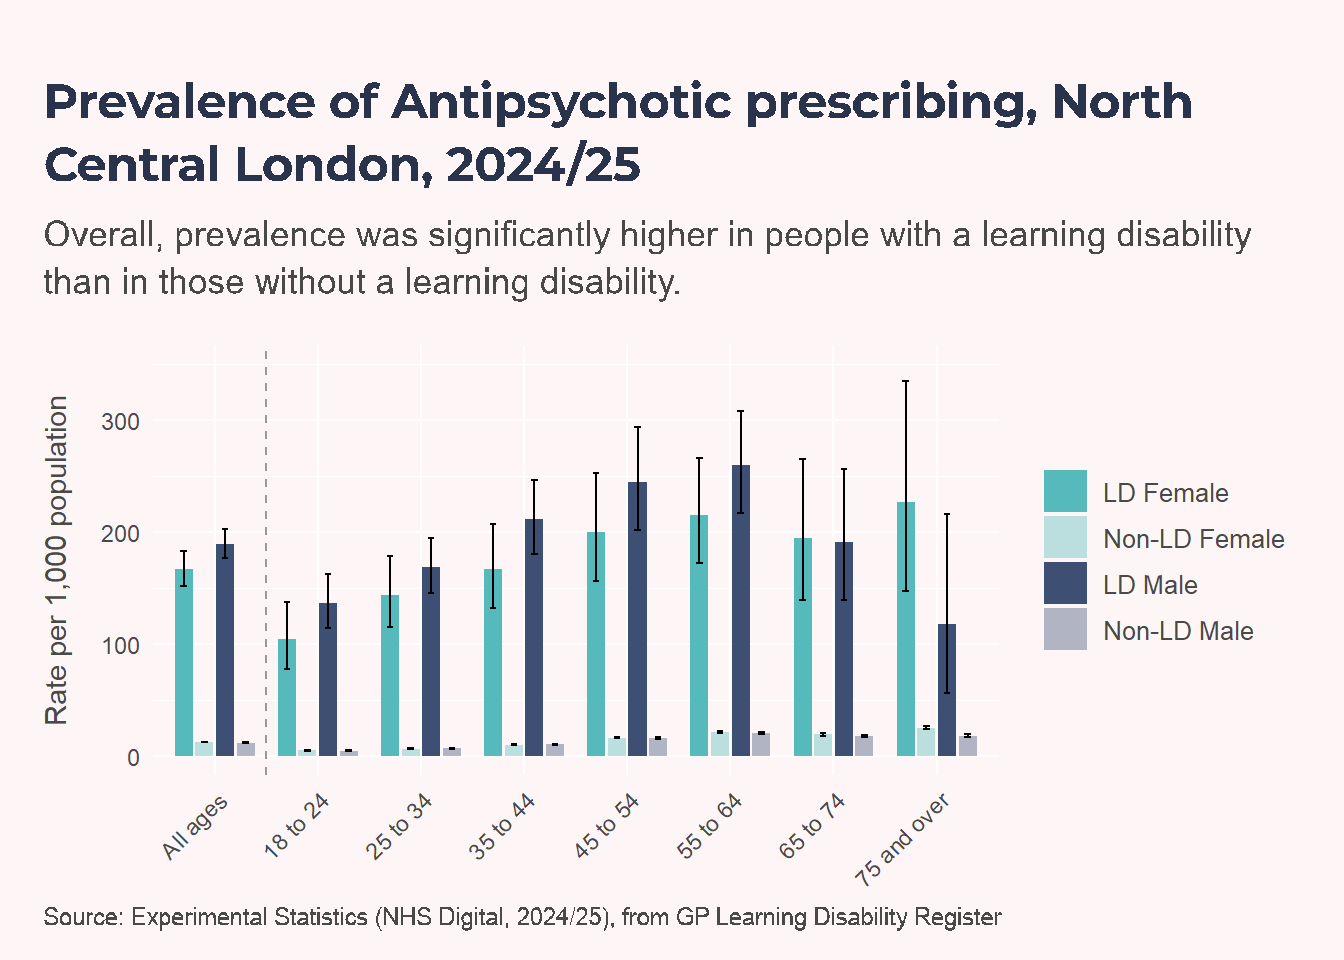
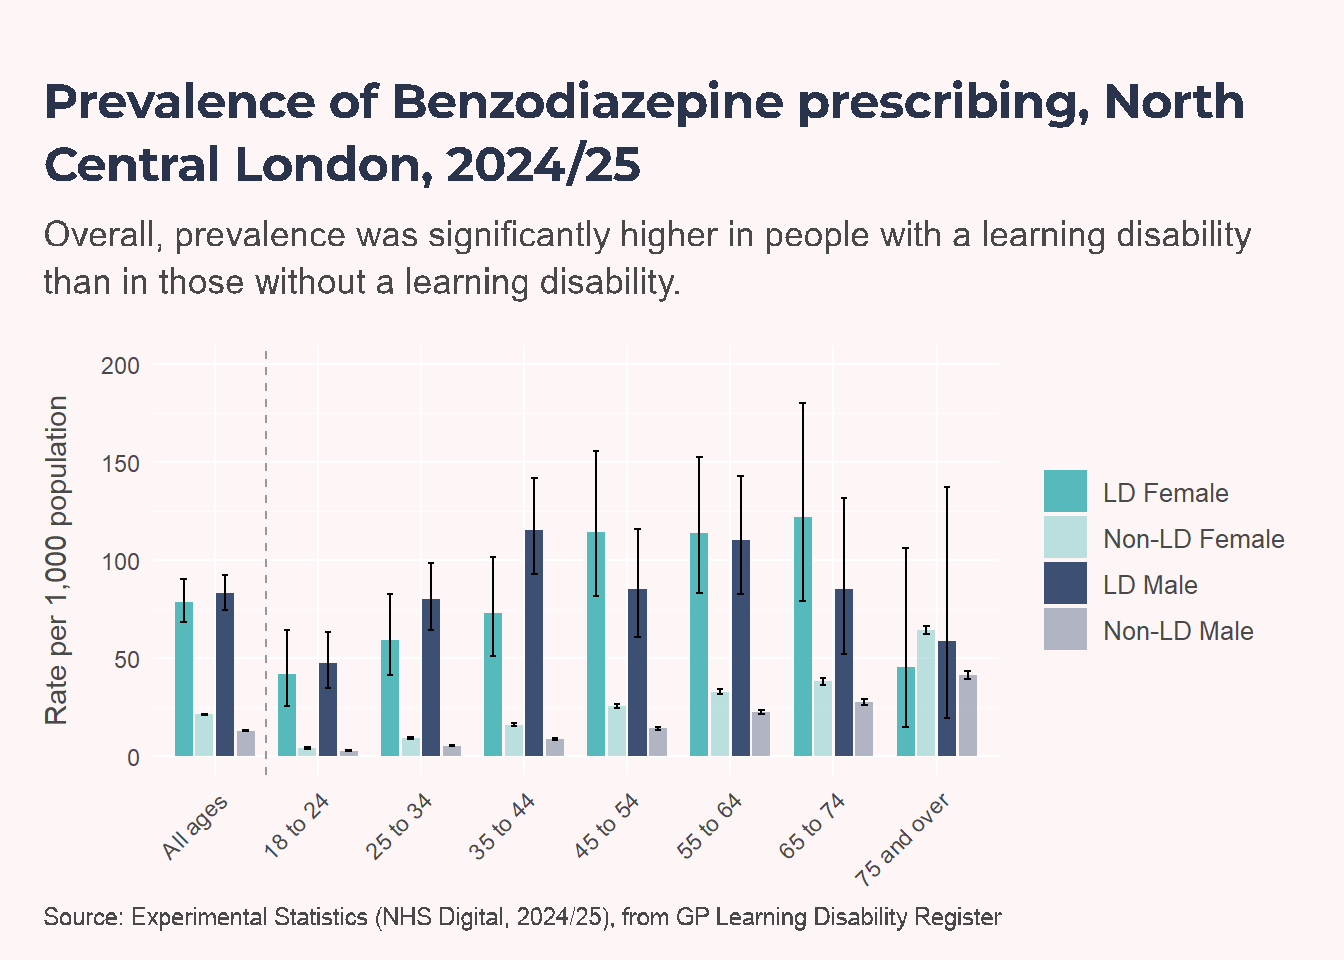
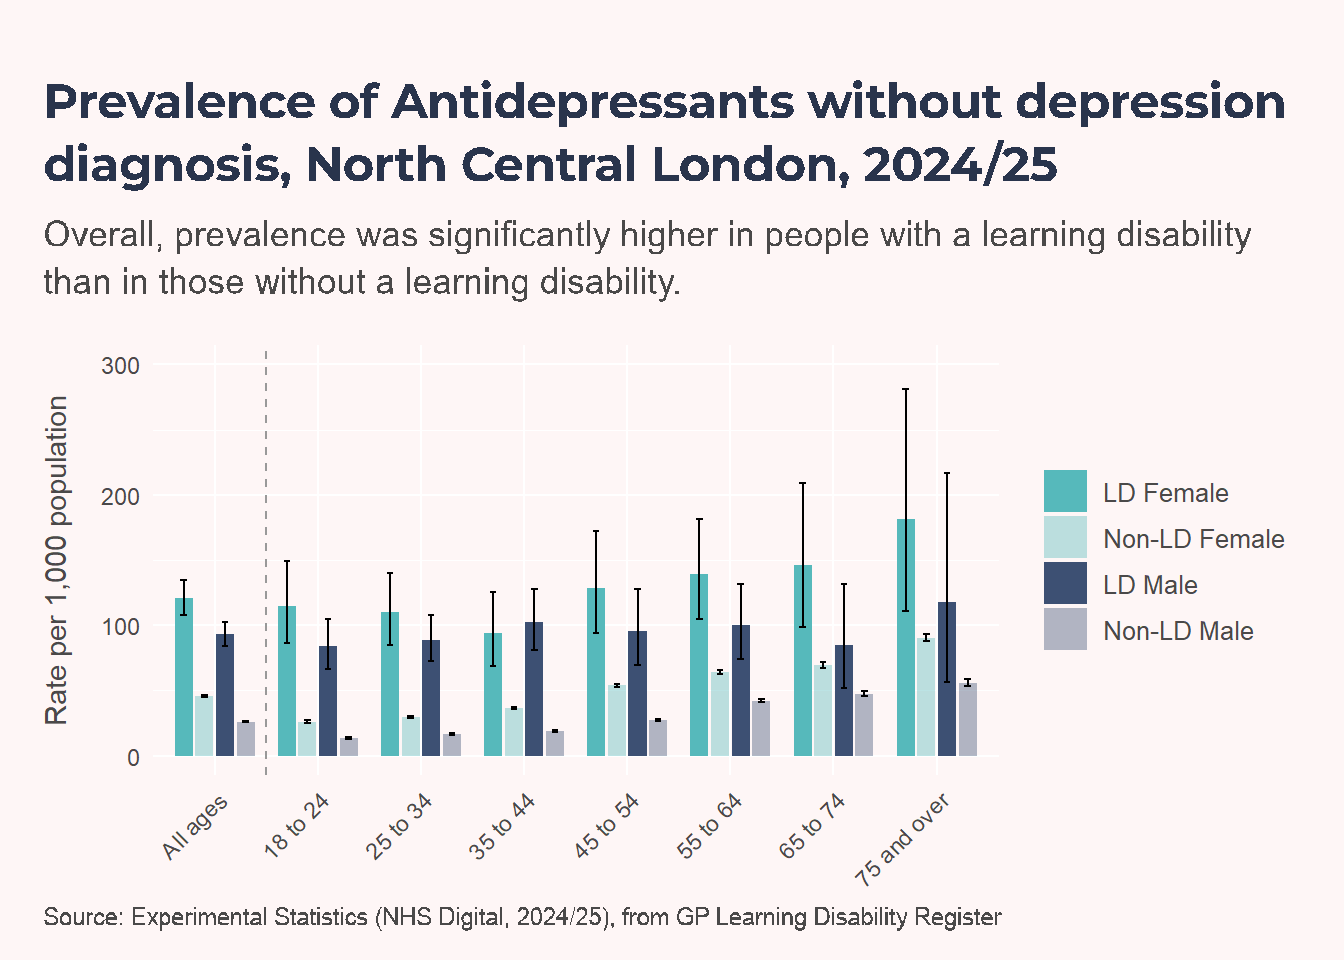
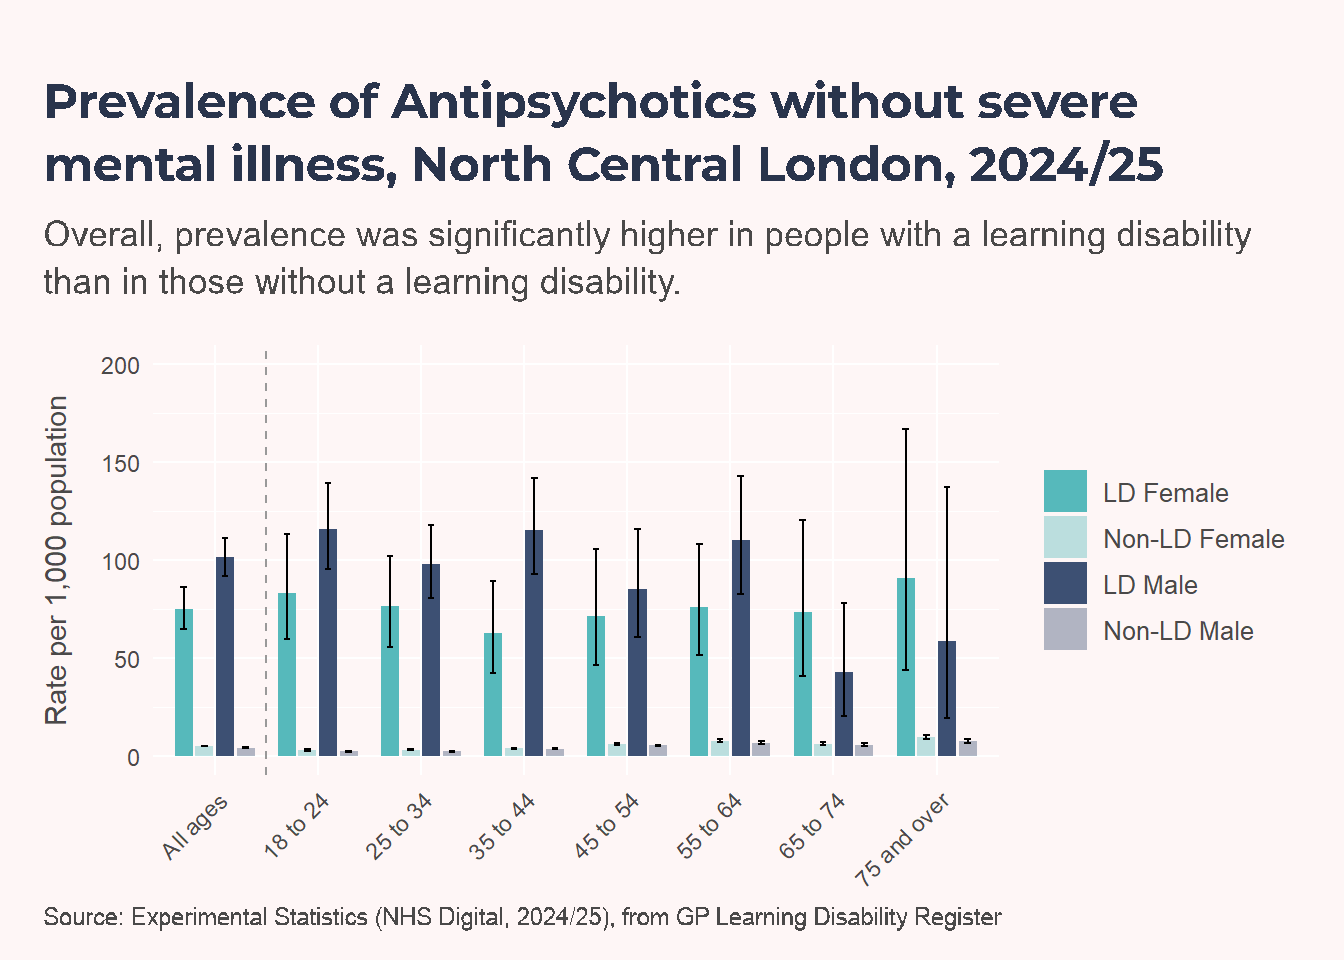
In 2025, PWLD are thought to be 15 times more likely to be prescribed an antipsychotic than the general population (NHS England, 2026). People should only be given psychotropic medication for the right reasons, in the lowest dose, for the shortest time, as side effects can impact on a person’s quality of life. For more information on the NHS England STOMP programme to stop over medication of PWLD, see the relevant evidence chapters.
Across all four measures of over-prescribing, PWLD were more likely than the general population to experience these issues.
The largest difference was in antipsychotic prescribing: 18.1% of PWLD were prescribed an antipsychotic, compared with 1.2% of the general population, meaning PWLD were 15.0 times more likely to be prescribed an antipsychotic than the general population.
Antidepressants were more likely to be prescribed without a depression diagnosis to females and antipsychotics were more likely to be prescribed without a severe mental illness diagnosis to males.
Depression is more common for PWLD
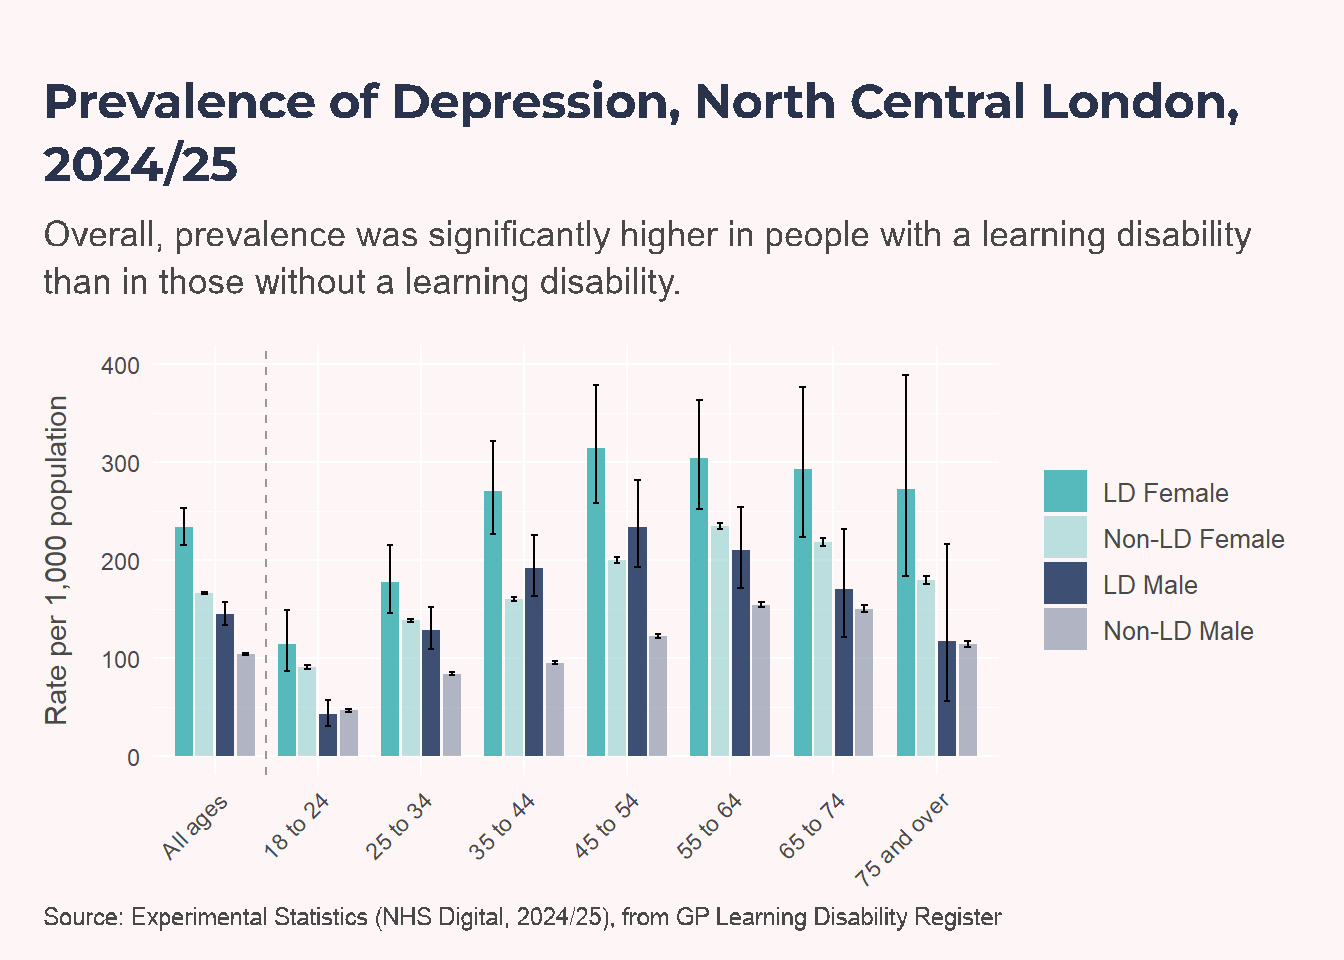
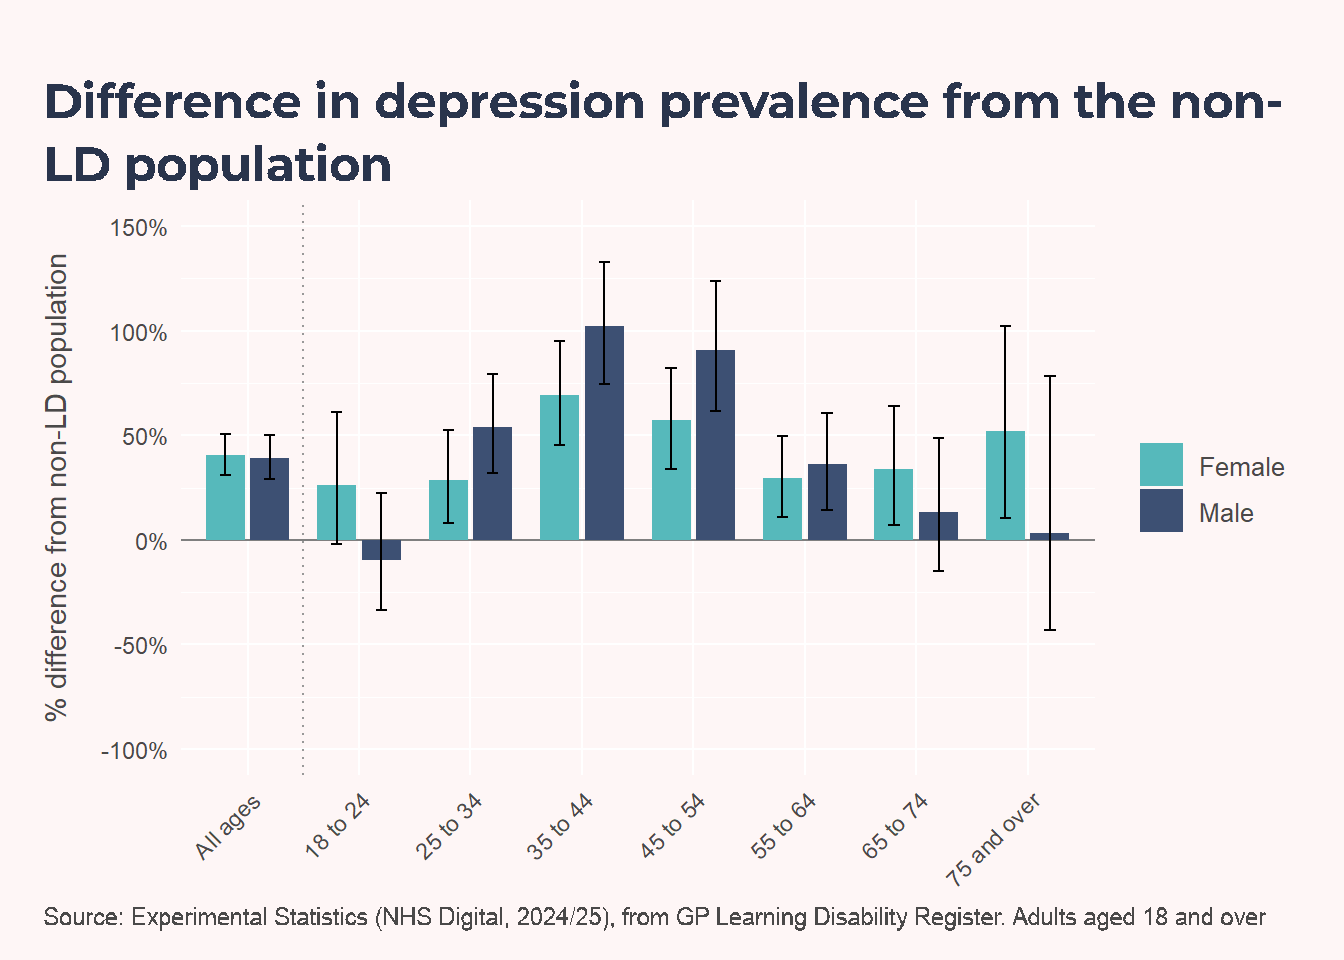
Around 179 per 1,000 PWLD in NCL had a depression diagnosis, compared with 135 per 1,000 in the rest of the population. Depression prevalence generally increased with age through middle age before declining in the oldest age groups.
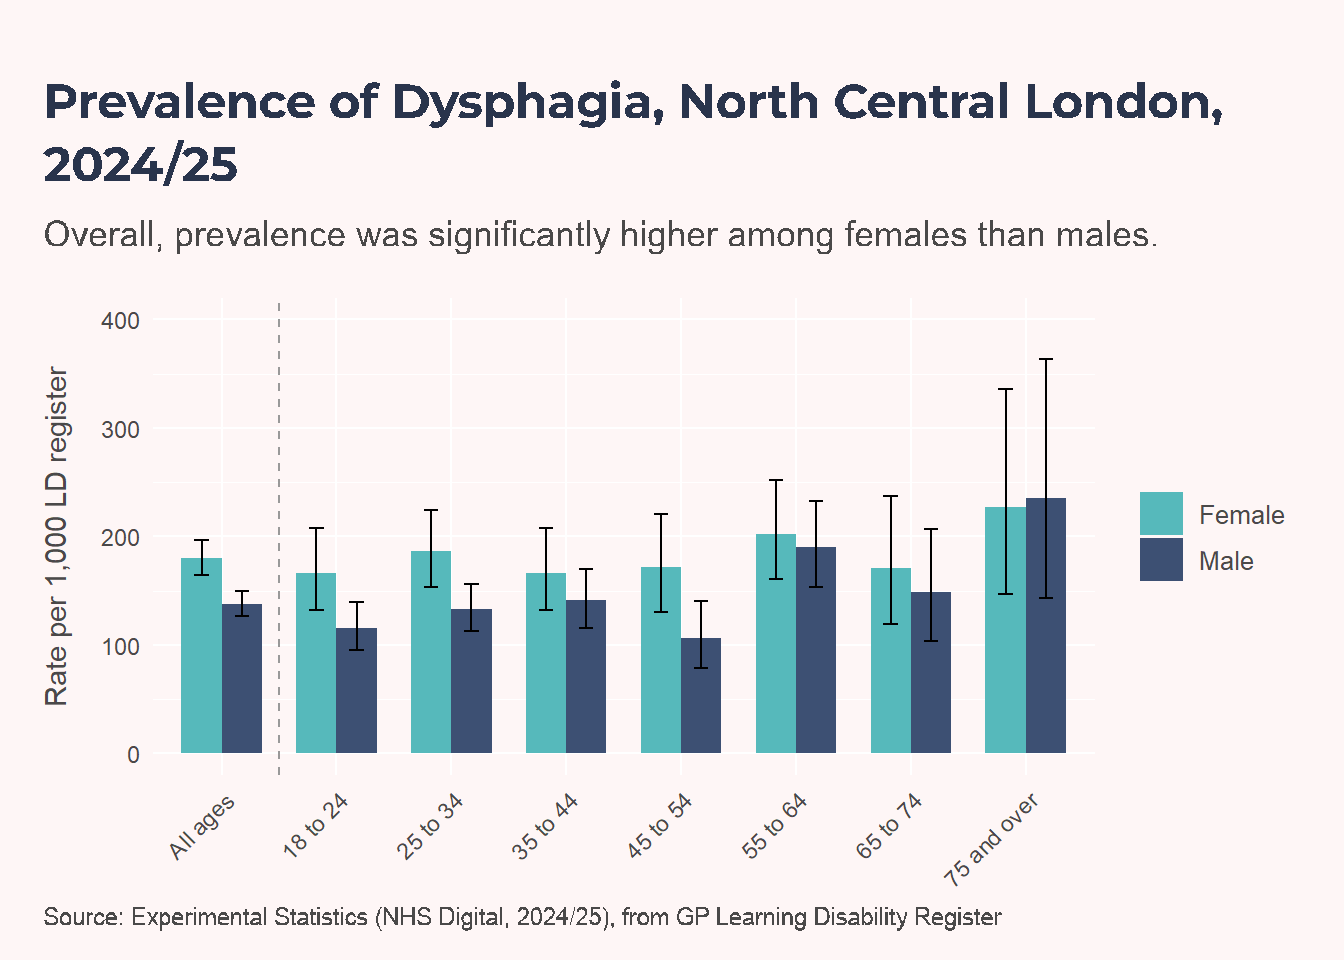
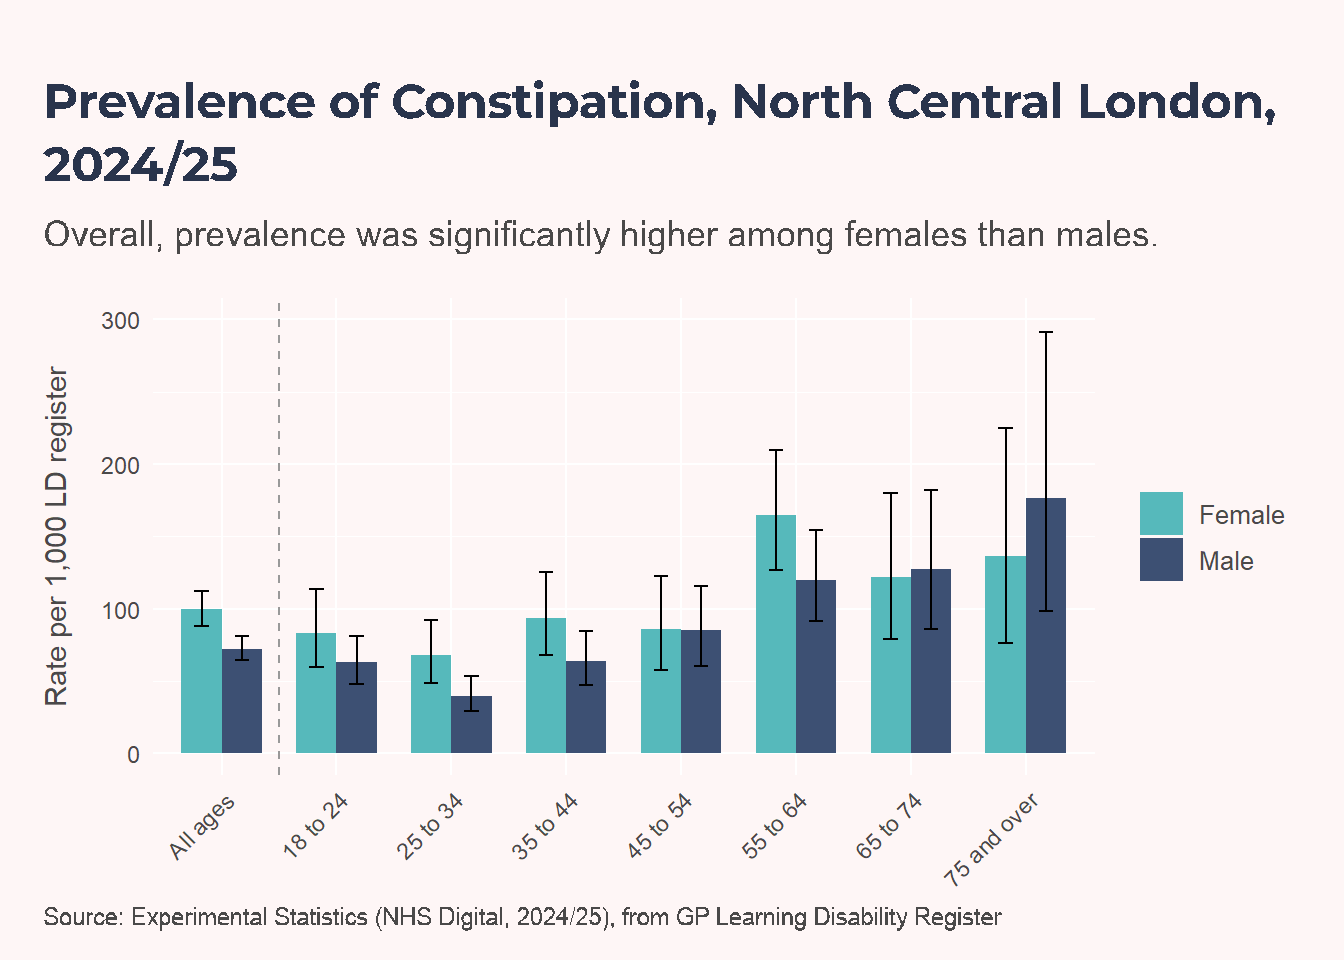
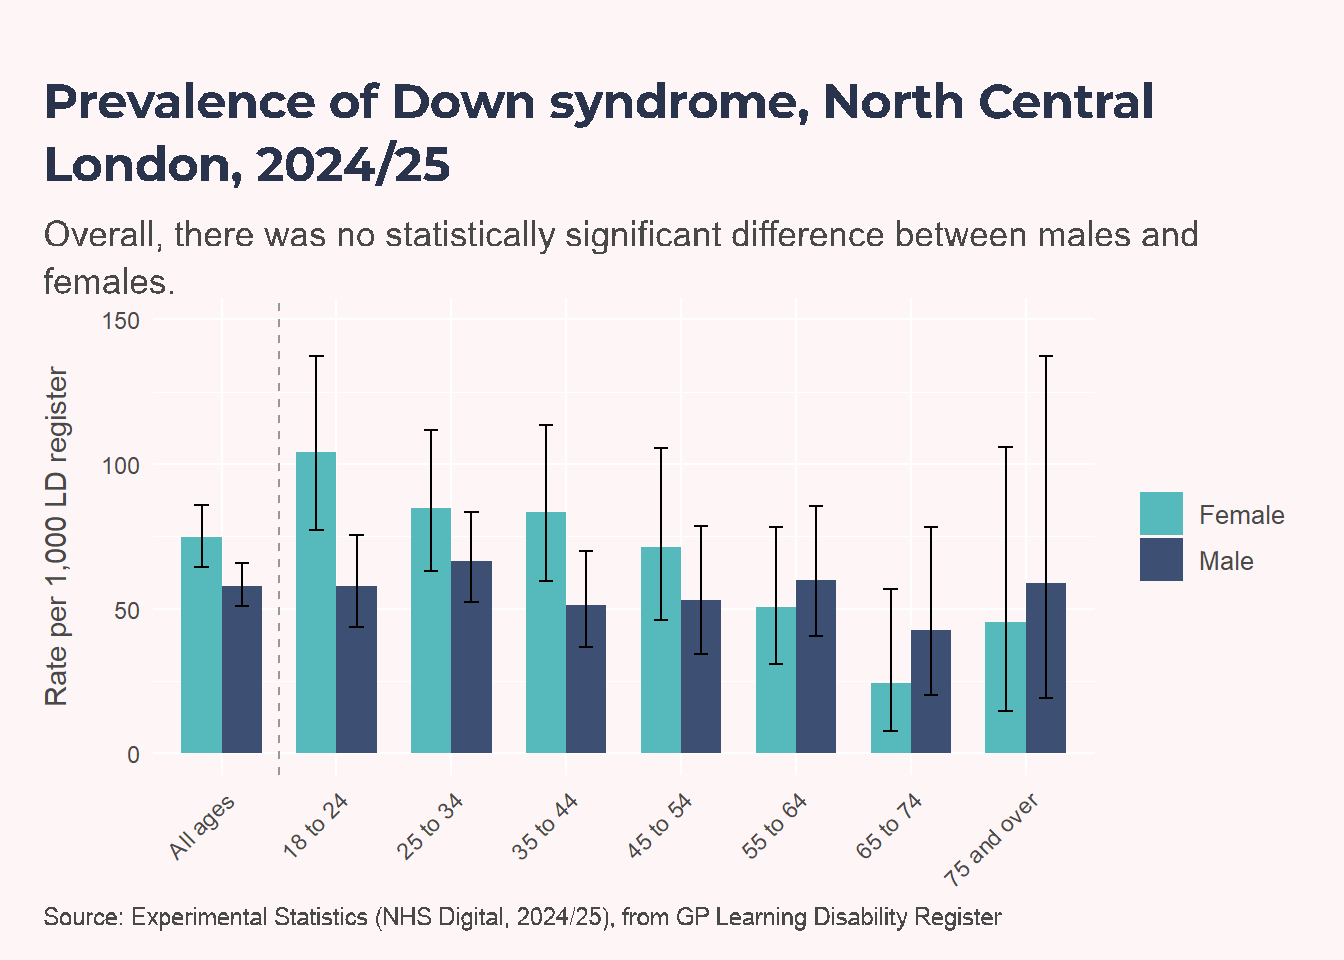
Prevalence of other conditions
NoteInterpret with caution
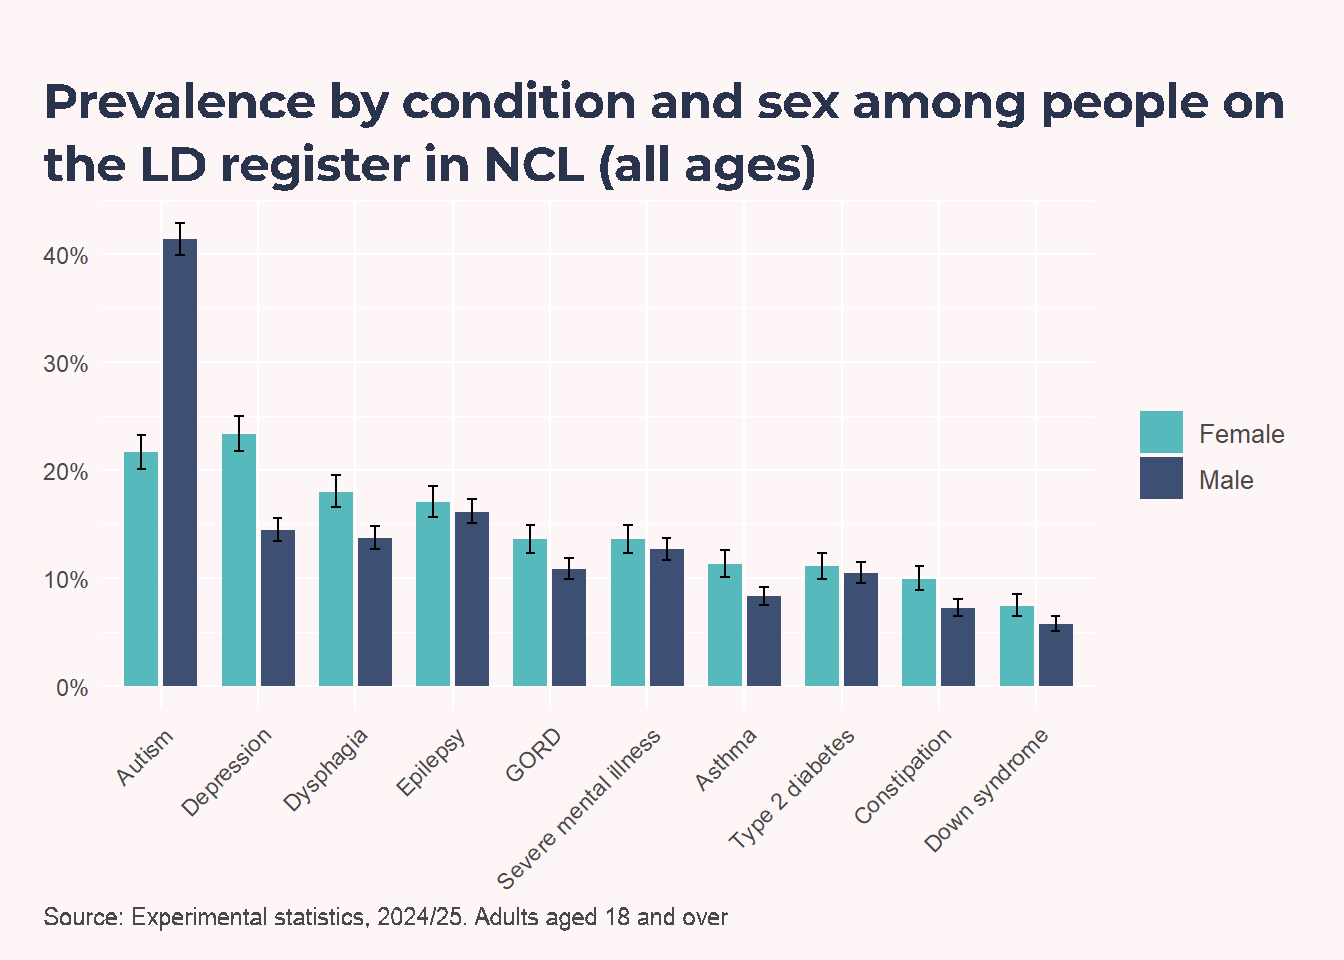
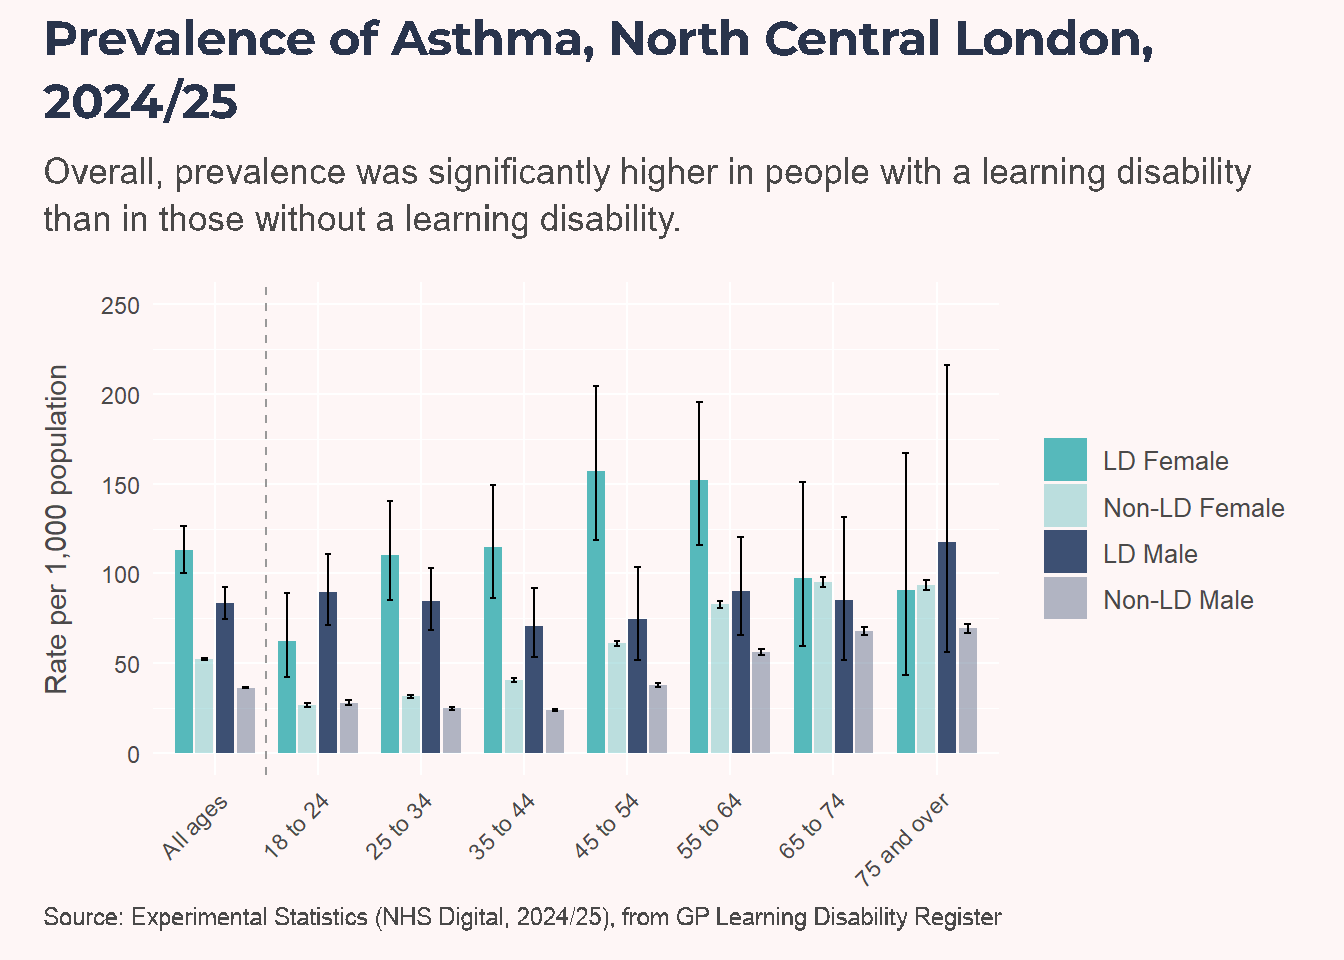
These prevalence estimates are based on recorded diagnoses. PWLD are more likely to receive AHCs and ongoing monitoring, increasing the likelihood that conditions are identified and coded in health records. Higher recorded prevalence may therefore partly reflect more complete recording rather than solely a higher underlying prevalence. This caveat primarily applies when drawing comparisons between PWLD and people without a learning disability.
Hospital admissions
NoteTechnical Note
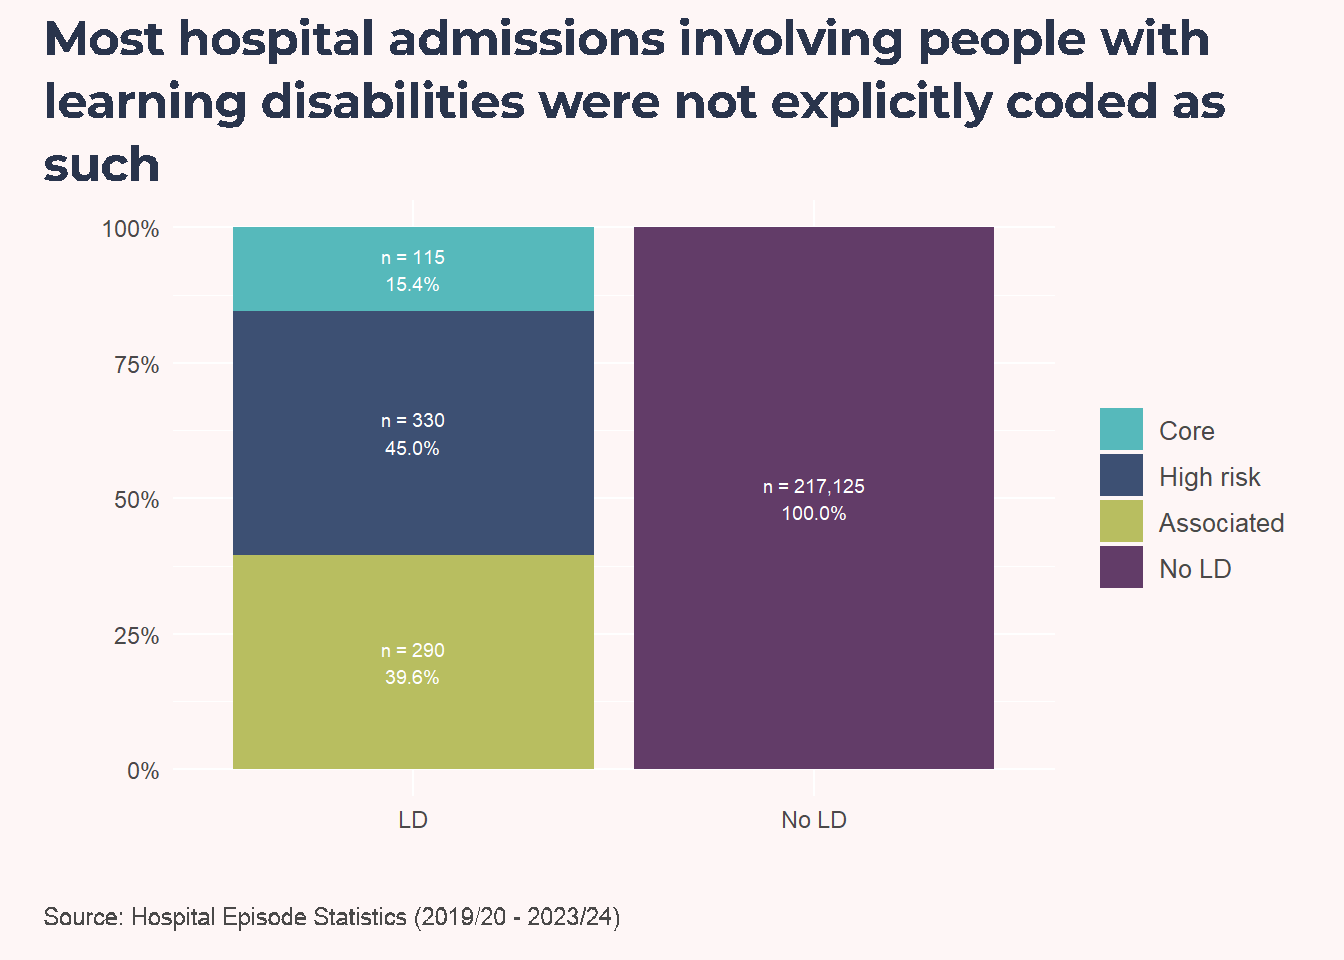
Learning disability status is often incompletely coded in Hospital Episode Statistics. To improve case identification, this analysis applies the Zylbersztejn et al. approach using three code groups in a hierarchy:
Core learning disability diagnoses,
High-risk underlying conditions, and
Associated underlying conditions
Admissions with no match in these groups are classified as non-learning-disability admissions.
The original code list was developed for children and young people, and defines:
- Core: ICD-10 F7 learning disability codes.
- High-risk: conditions where most people are likely to have a learning disability.
- Associated: conditions where a substantial minority are likely to have a learning disability.
Of 380 admissions identified among Camden residents over the last five years, 300 were identified using the expanded case-finding methodology rather than direct coding of a learning disability.
This suggests that direct learning-disability coding alone would miss a substantial share of relevant activity, so case-identification strategy materially affects interpretation of local acute-care patterns.
PWLD were more likely to be admitted on an unplanned pathway
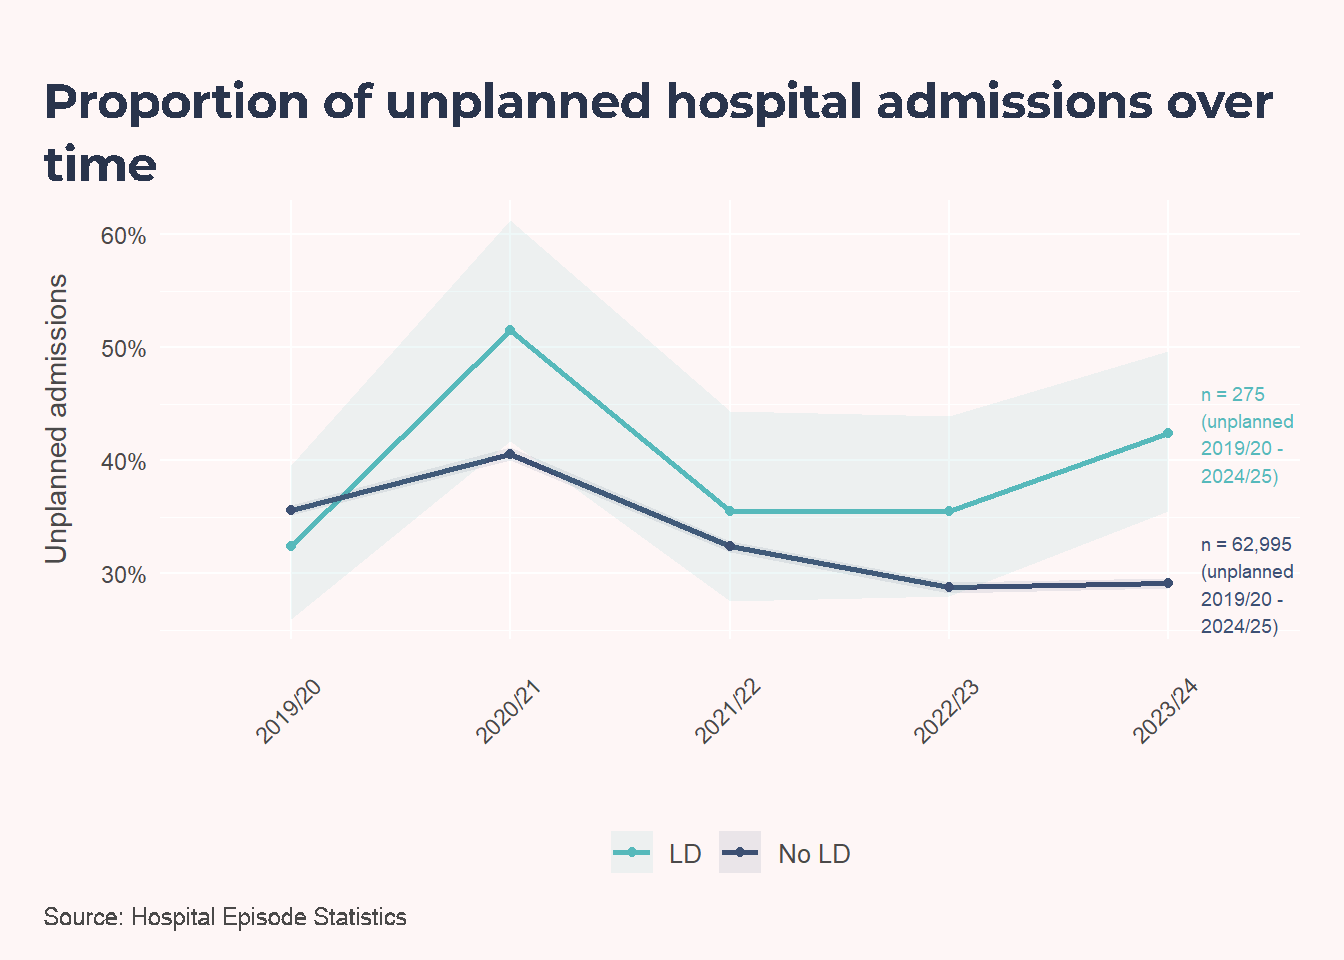
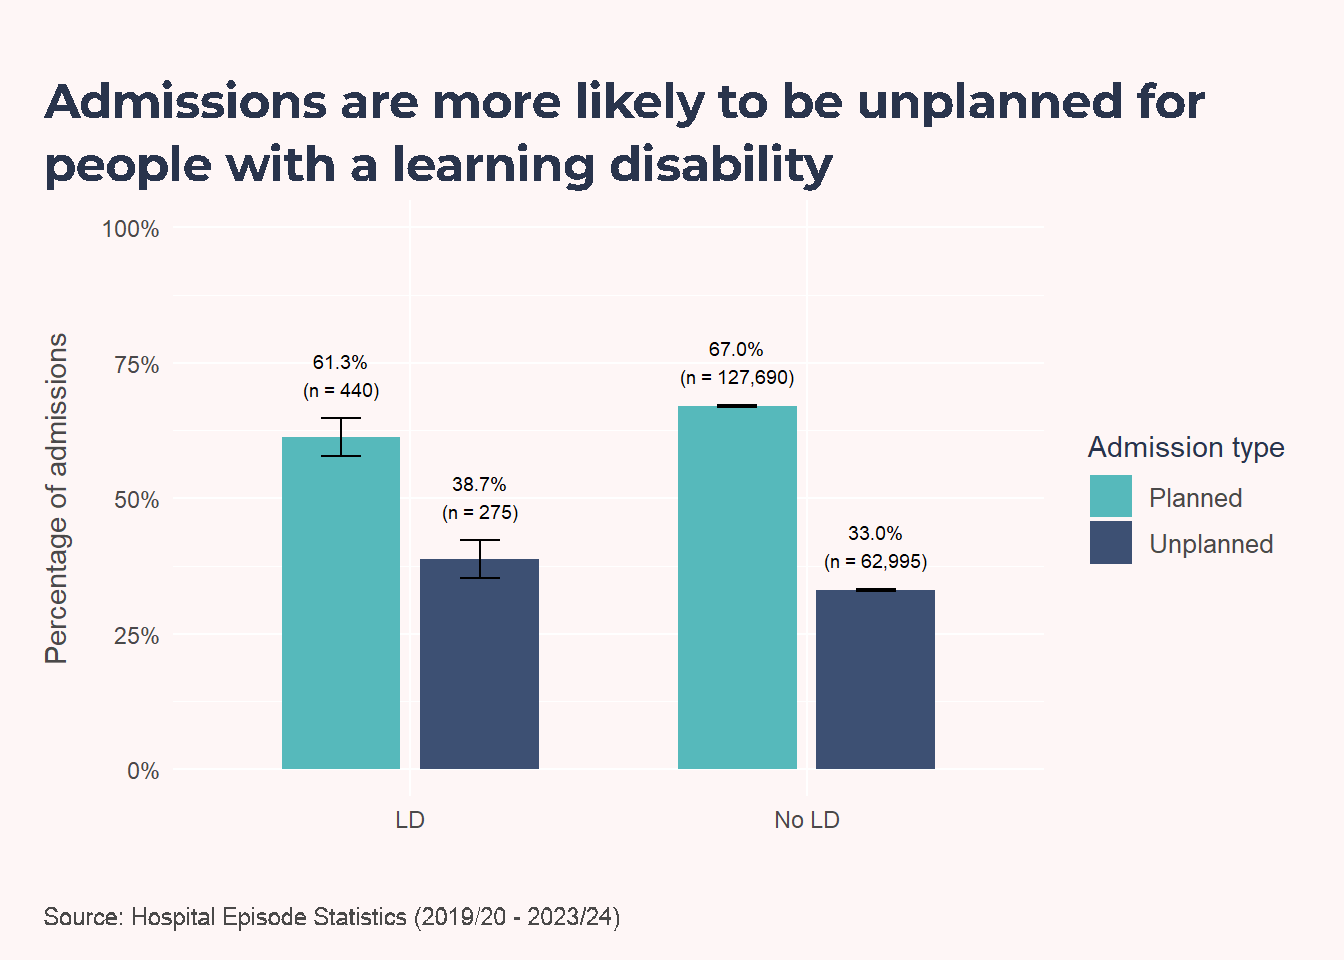
This comparison asks whether admissions among people with learning disabilities are more likely to enter via an unplanned pathway (including day cases). Across 2019/20 to 2023/24 in Camden, 38.7% of admissions in the learning disability group were unplanned, compared with 33.0% in the non-learning-disability group. That corresponds to a relative difference of 17.1% (p = 0.00153).
PWLD were more likely to be admitted for epilepsy or a respiratory infection
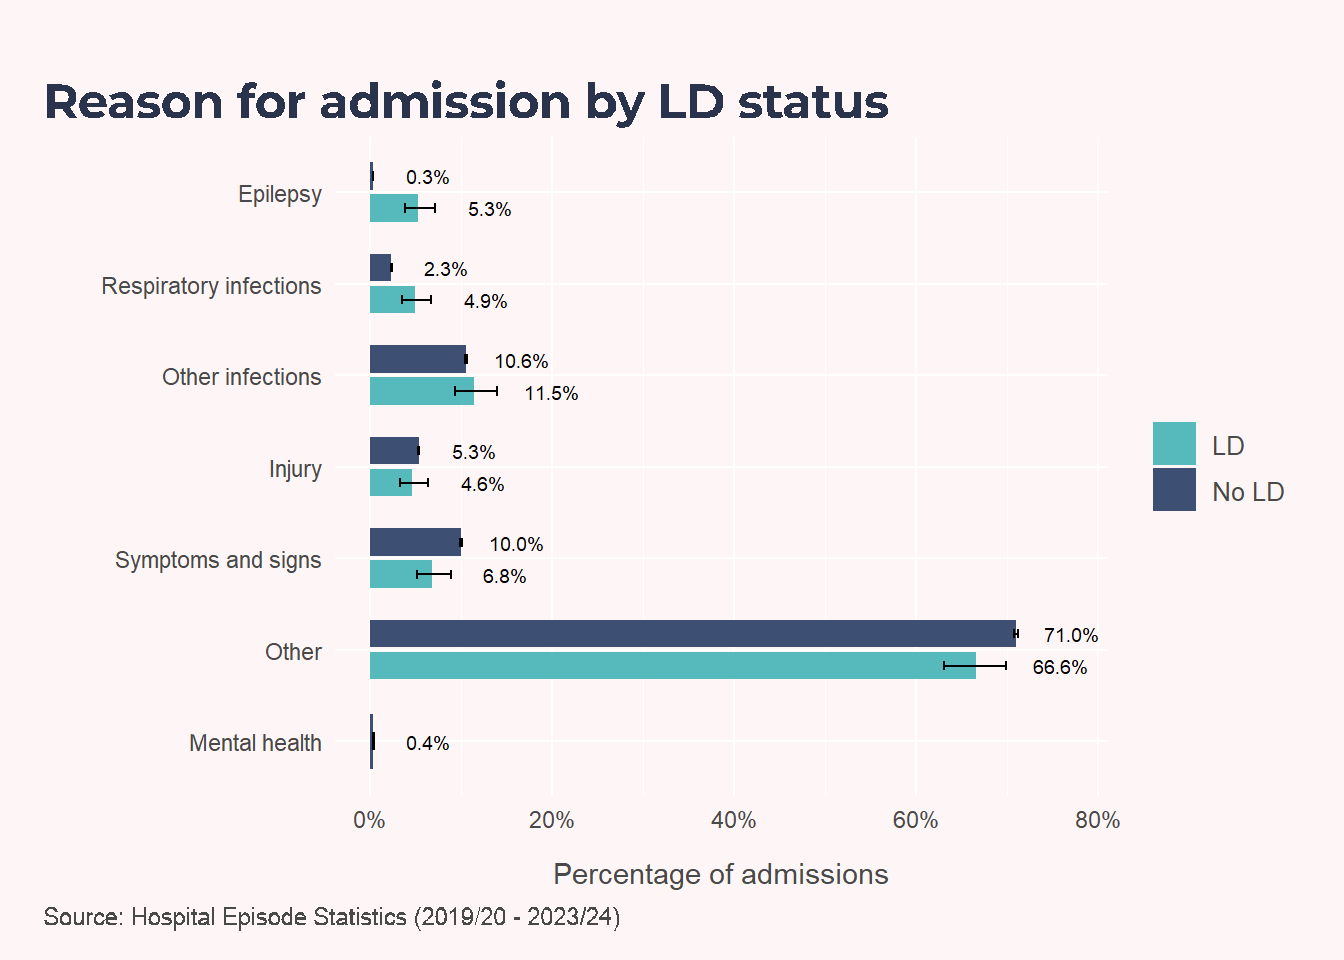
Epilepsy accounts for a higher share of admissions in the learning disability group (5.3%) than in the non-learning-disability group (0.3%), and respiratory infections are also more common (4.9% vs 2.3%). By contrast, non-specific symptoms/signs (6.8% vs 10.0%) and the broad ‘Other’ category (66.6% vs 71.0%) make up a smaller share of admissions in the learning disability group.
This distribution indicates where preventable or better-managed conditions may be contributing disproportionately to admissions in the learning disability group.
PWLD had a longer average length of stay
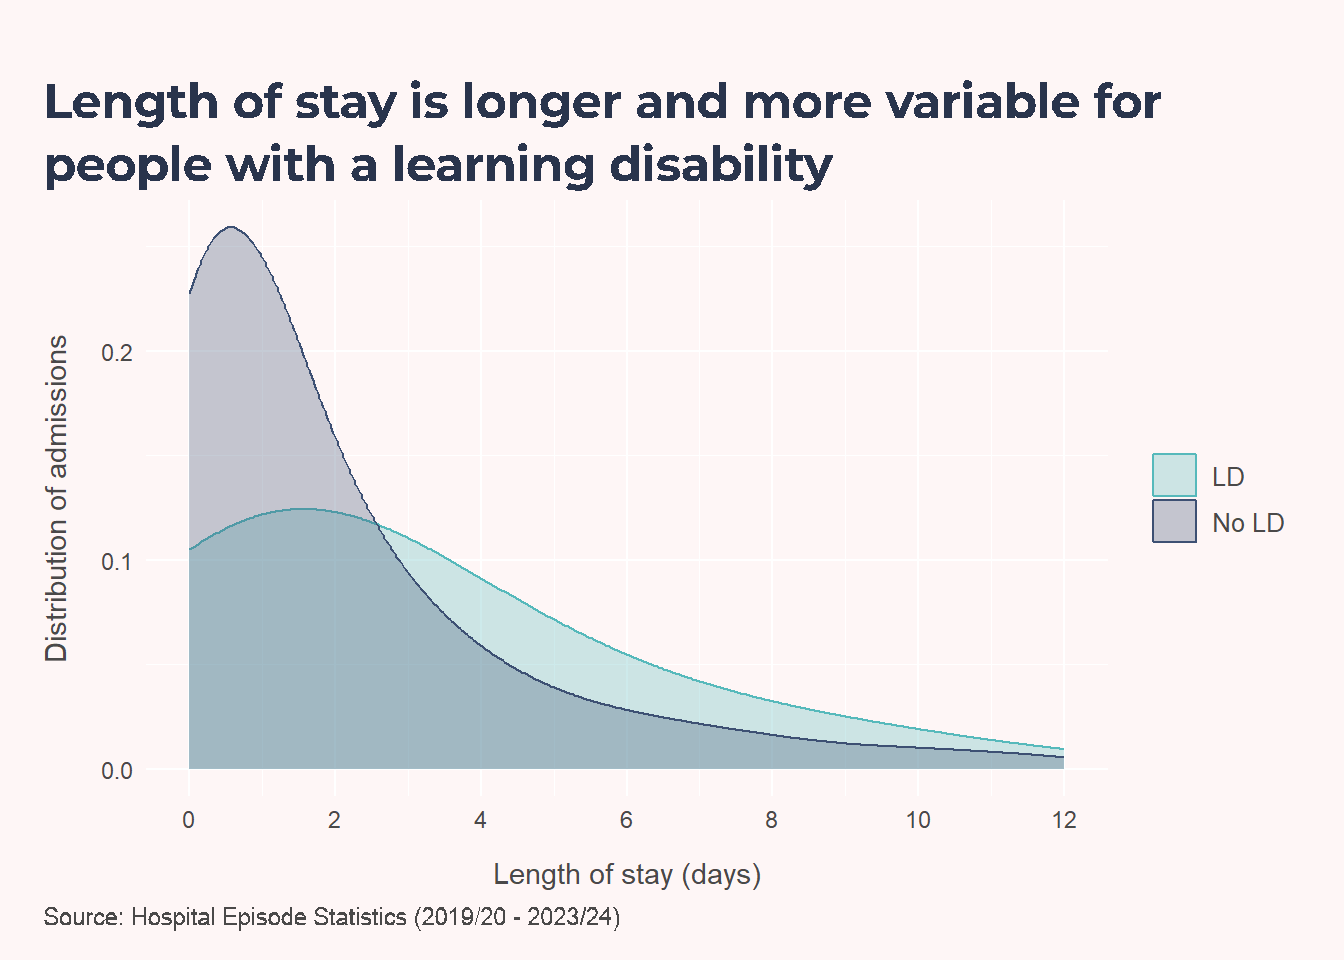
The density curves show where admissions are most concentrated in each group. In this dataset, admissions of a week or more were 19.1% in the learning disability group and 11.9% in the non-learning-disability group. These admissions include planned and unplanned episodes, including day cases.
NoteTechnical Note
Length of stay is not a direct proxy for delayed discharge, but it can partly reflect discharge barriers alongside clinical complexity and care-process factors.
Services
The CQC assessment highlighted a number of strengths relevant to adults who are PWLD in Camden. The local authority has taken a strategic approach to developing accommodation and support options, with planning driven by an ambition to support people to move away from residential care and live more independently within the community. The refreshed Learning Disability Accommodation Strategic Framework (2024) reported that all 26 supported housing schemes for PWLD were subject to annual quality monitoring, with the proportion rated as requiring significant improvement (“Red”) falling from almost one-third of schemes in 2019 to 11.4%. The Council is also investing in future capacity, with 17 new supported housing units planned by 2027/28, alongside expansion of Shared Lives and other community-based support options.
The assessment found strong partnership working and governance arrangements across learning disability services. CQC noted clear accountability, quality assurance and information-sharing processes, including integrated working arrangements within the Camden Learning Disability Service (CLDS). Partnership working on learning disability accommodation and market management was identified as an example of effective collaboration, while co-produced services for PWLD were recognised for supporting equality of experience and person-centred solutions. CQC also highlighted Camden’s strengths-based approach to prevention and early intervention, including the Living a Good Life - Opportunities Planning project, which helps PWLD identify and access meaningful opportunities, reducing or delaying the need for more intensive statutory support.
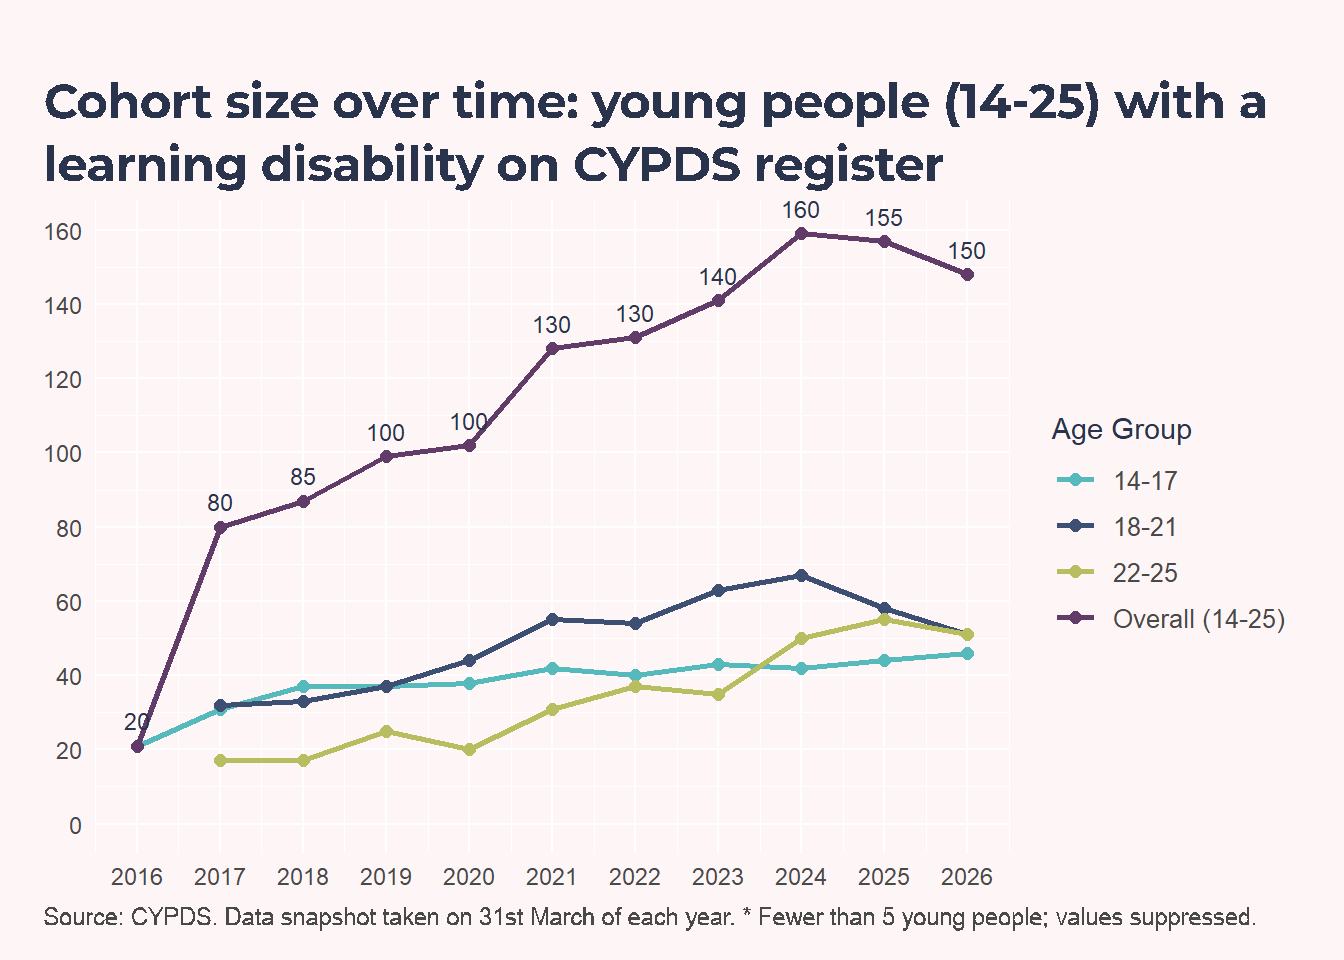
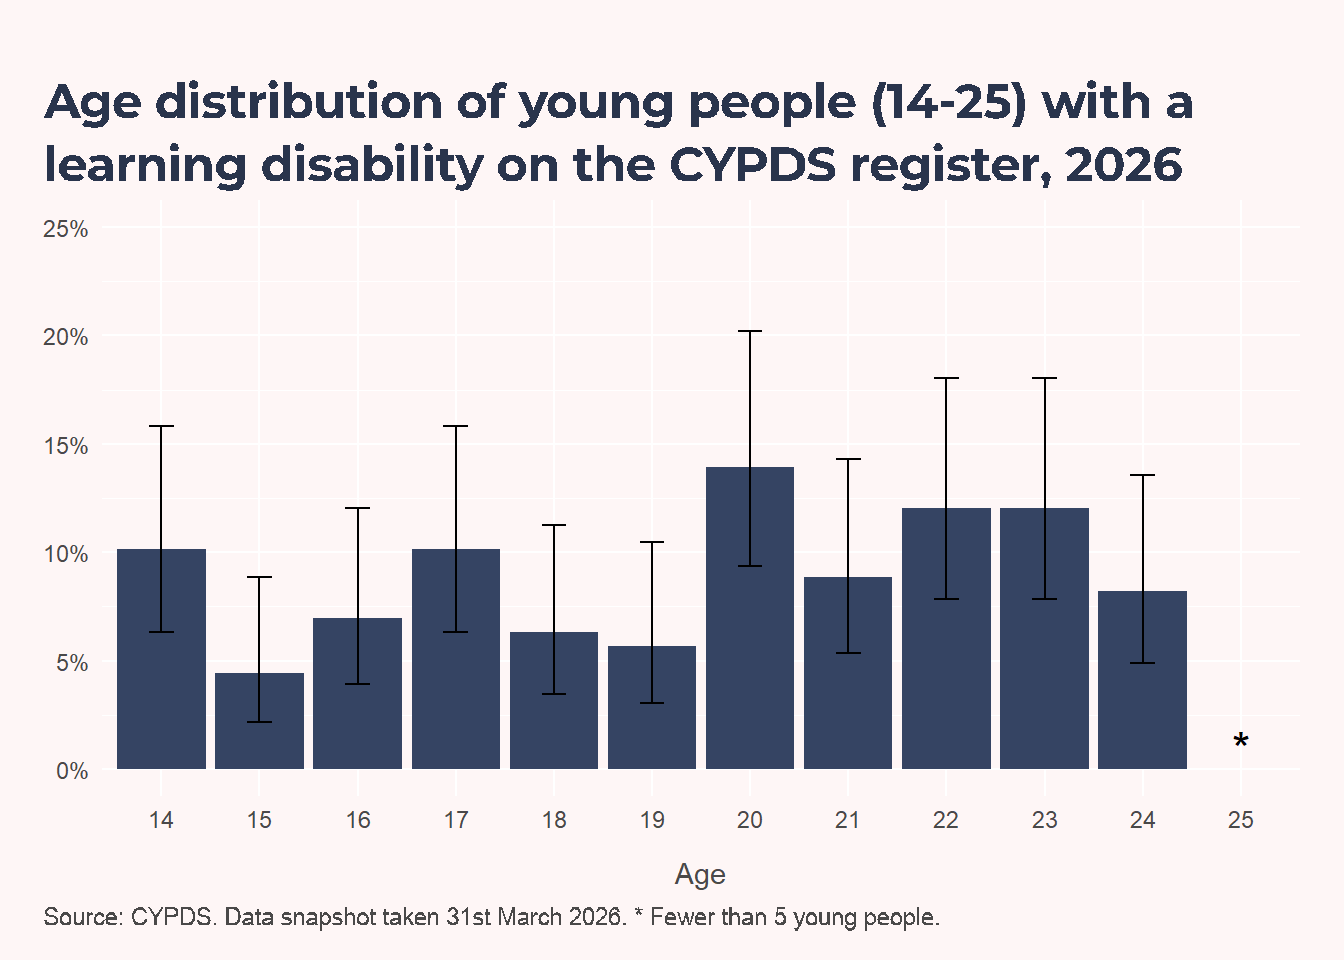
Particularly relevant to this Health Needs Assessment was the strong praise for transition arrangements between children’s and adult services. CQC identified effective communication and joint working between teams supporting young people with additional needs, highlighting the integrated 0-25 transition pathway spanning the Camden Young People’s Disability Service (CYPDS) and Camden Learning Disability Service (CLDS). The assessment described this as a notable example of successful partnership working between adult social care, children’s services and health partners, helping to ensure continuity of support as young people move into adulthood. This was cited as one of Camden’s key strengths and demonstrates a well-developed transition model for PWLD.
CLDS
Demography, language, deprivation and residence
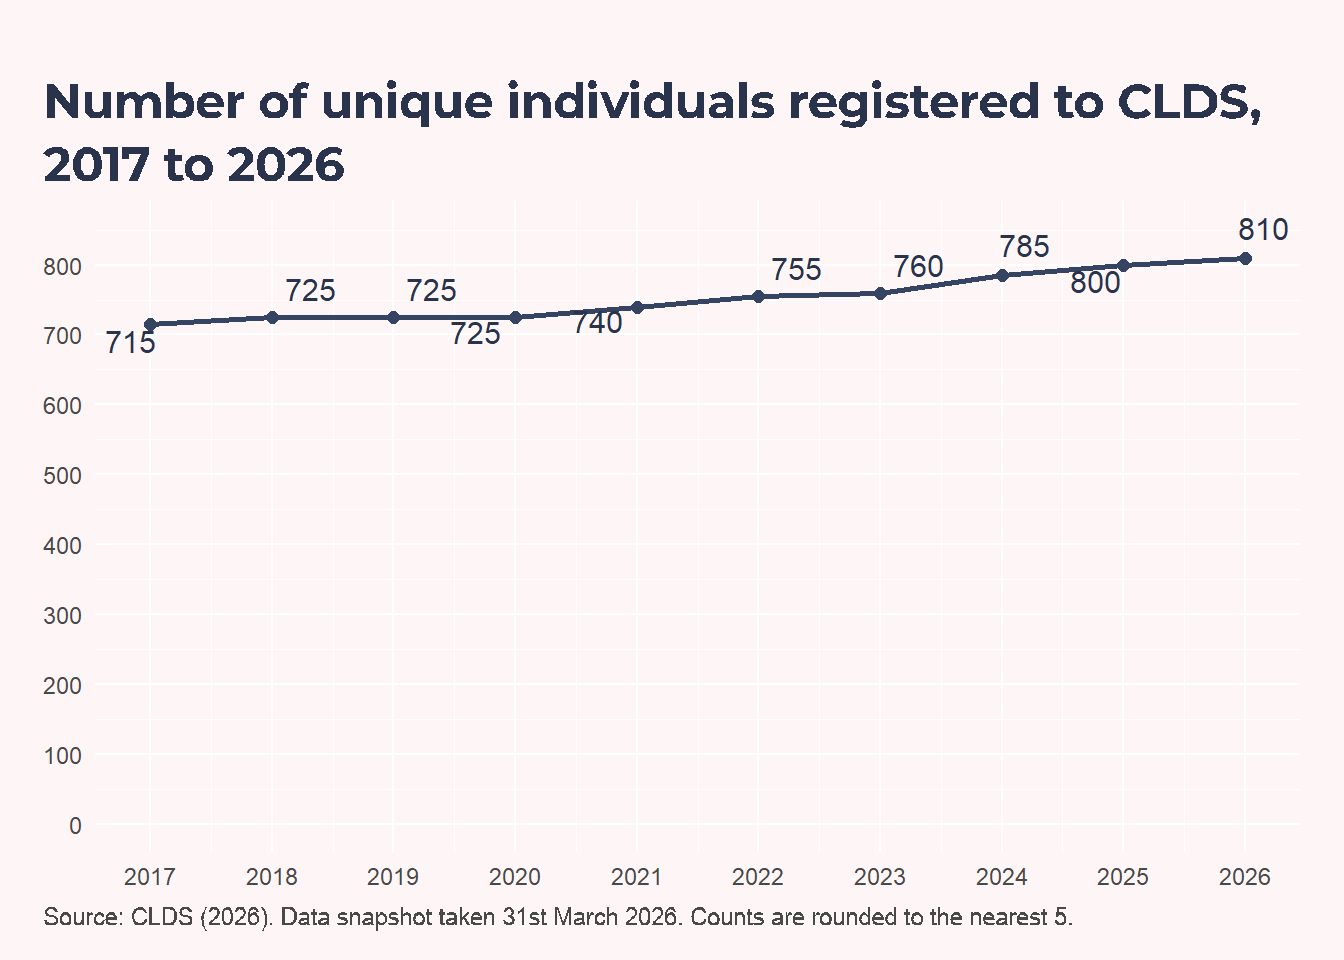
In 2026, the CLDS register includes 810 people, compared with 810 on the GP Learning Disability Register. These are not the same denominator populations: the GP register is a primary-care diagnostic register used for annual health check eligibility, while CLDS reflects people known to specialist local services. The similar headline counts provide a useful triangulation check rather than a direct one-to-one validation.
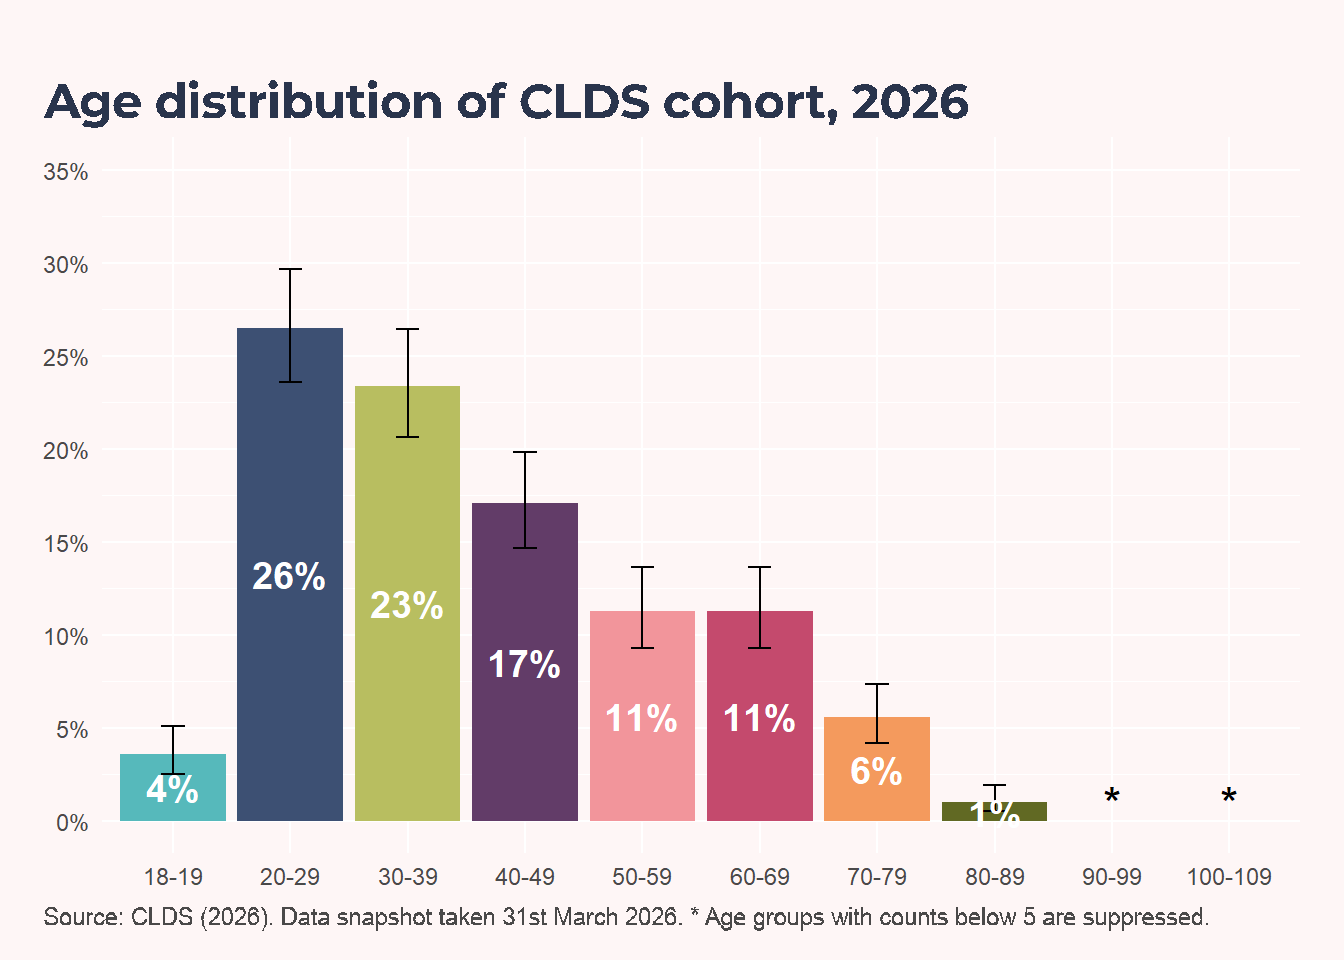
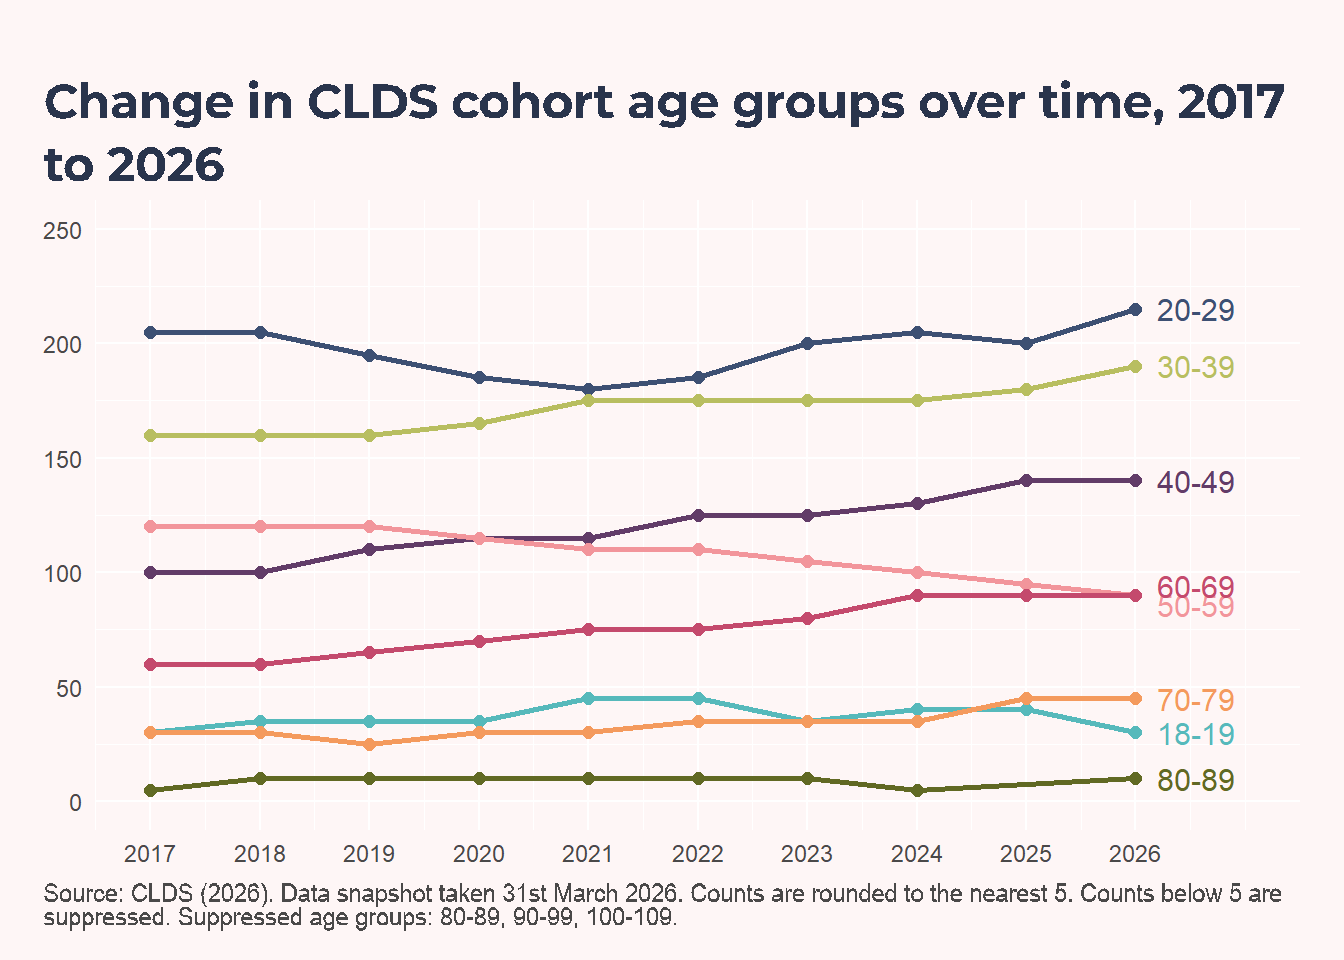
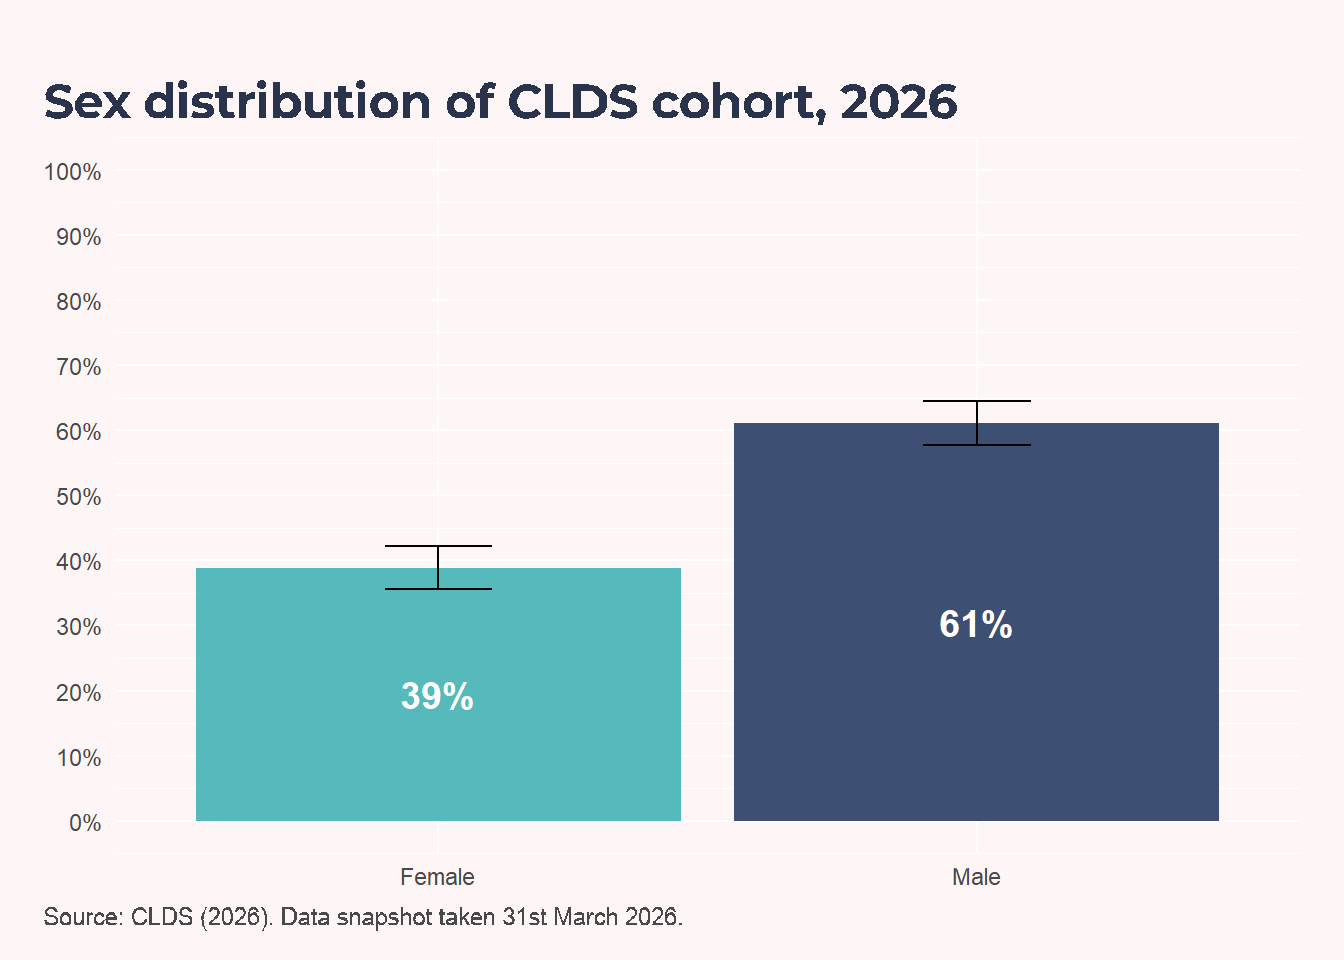
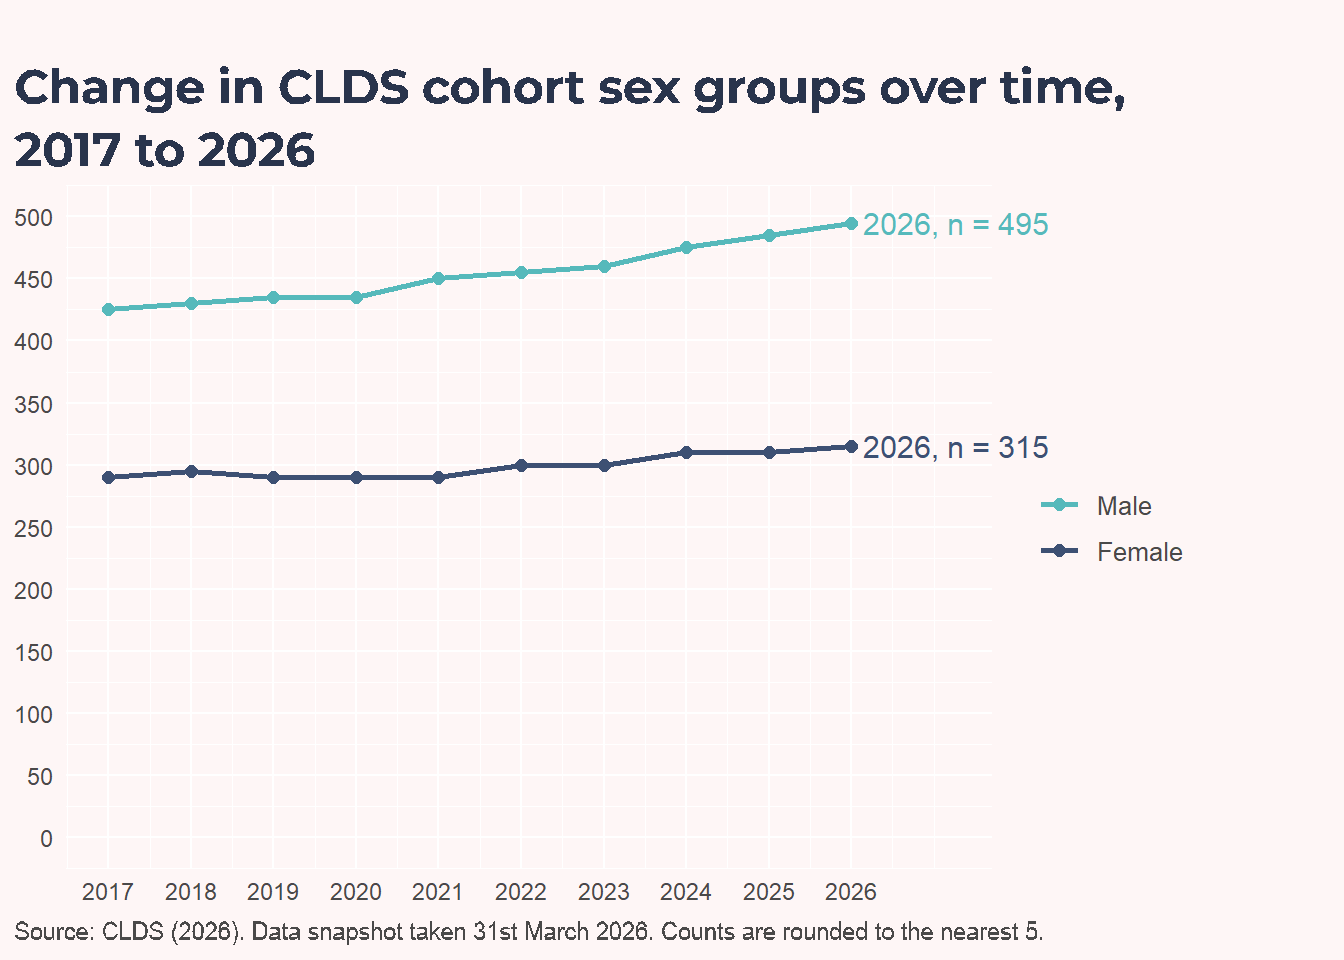
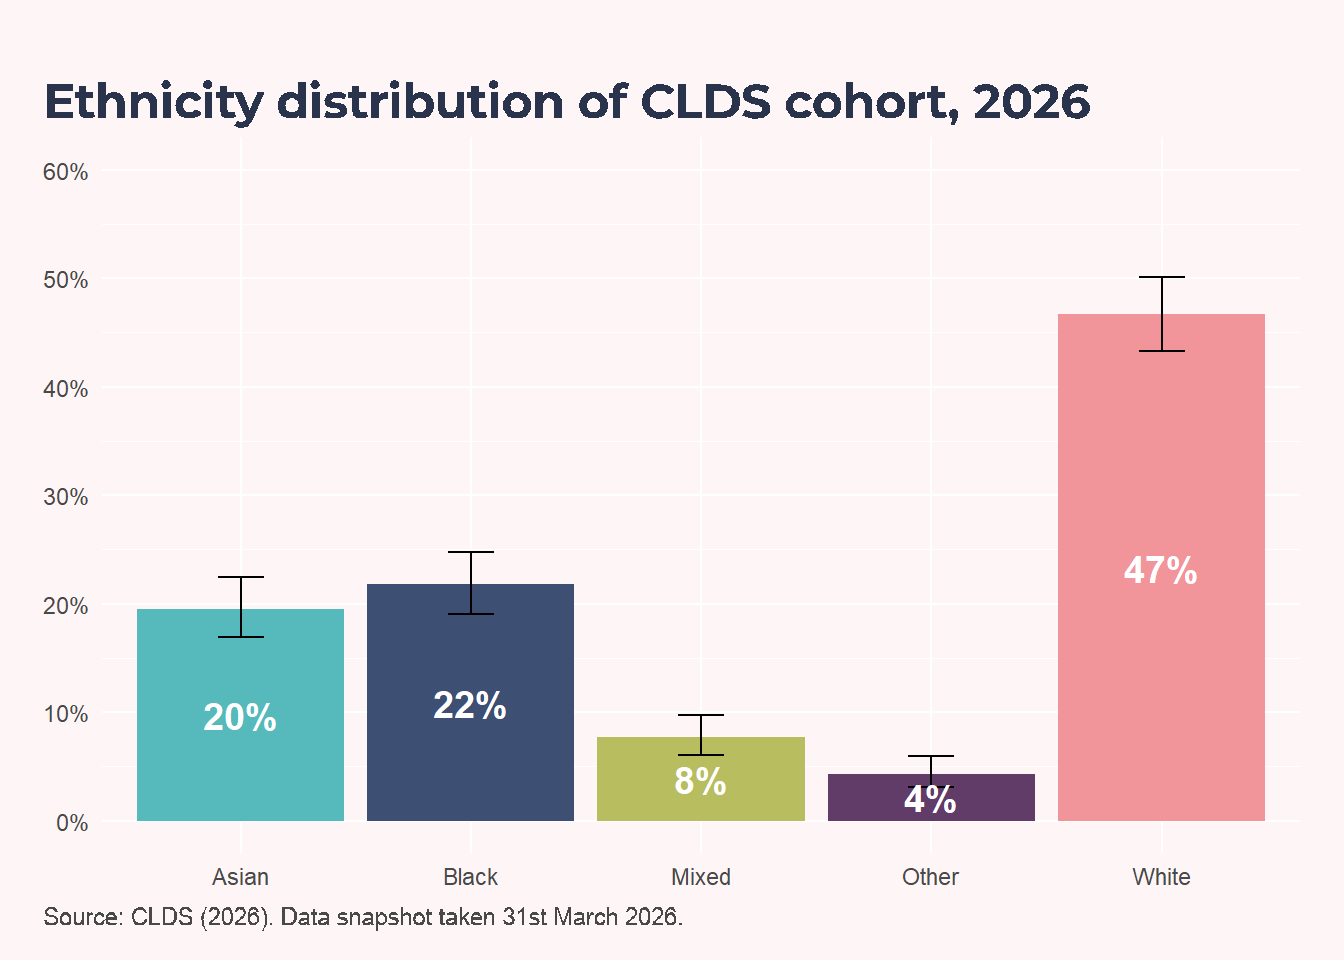
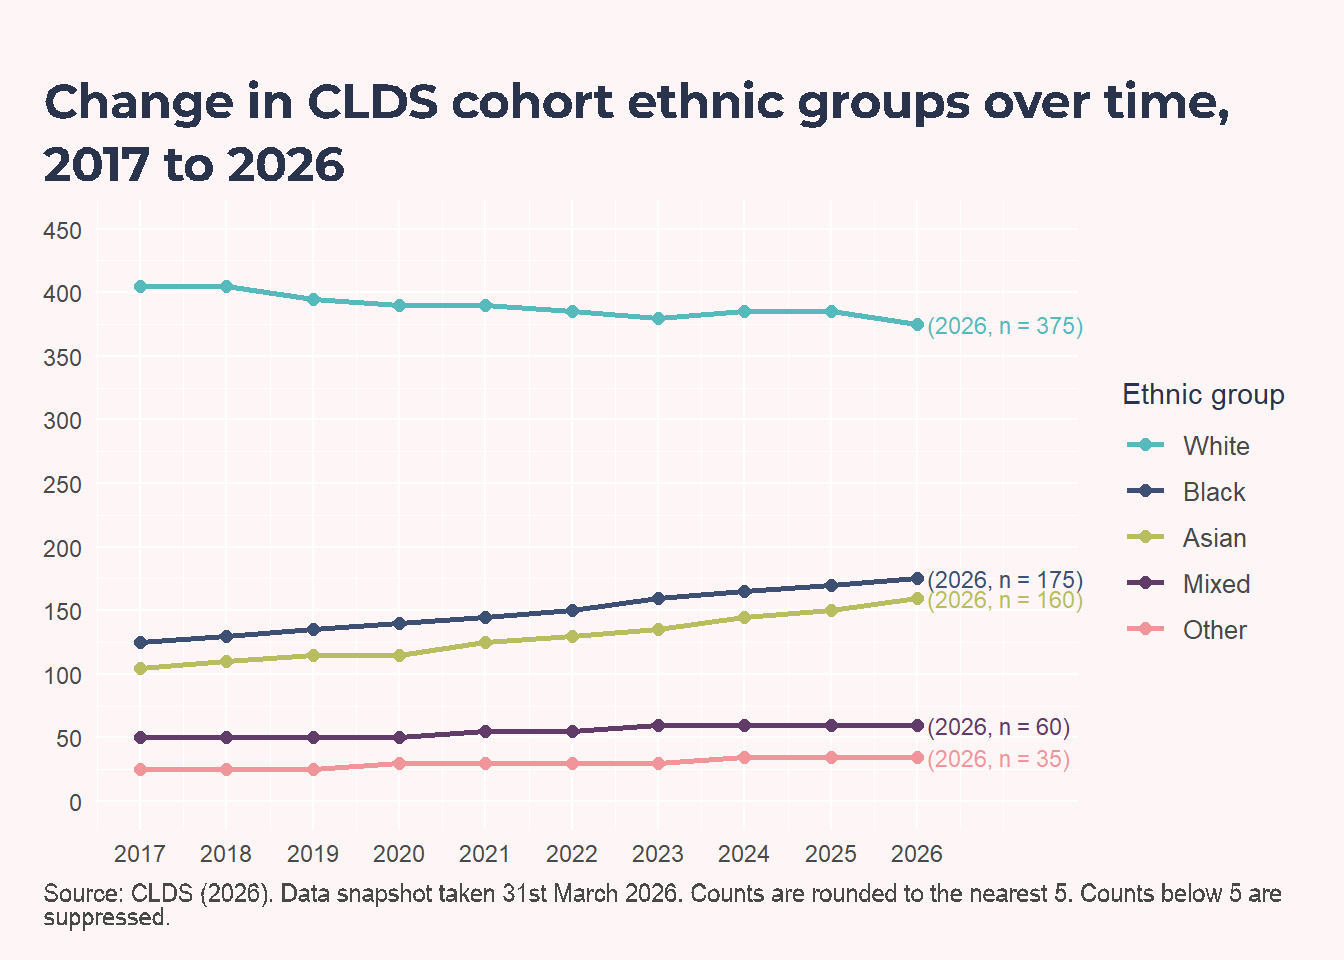
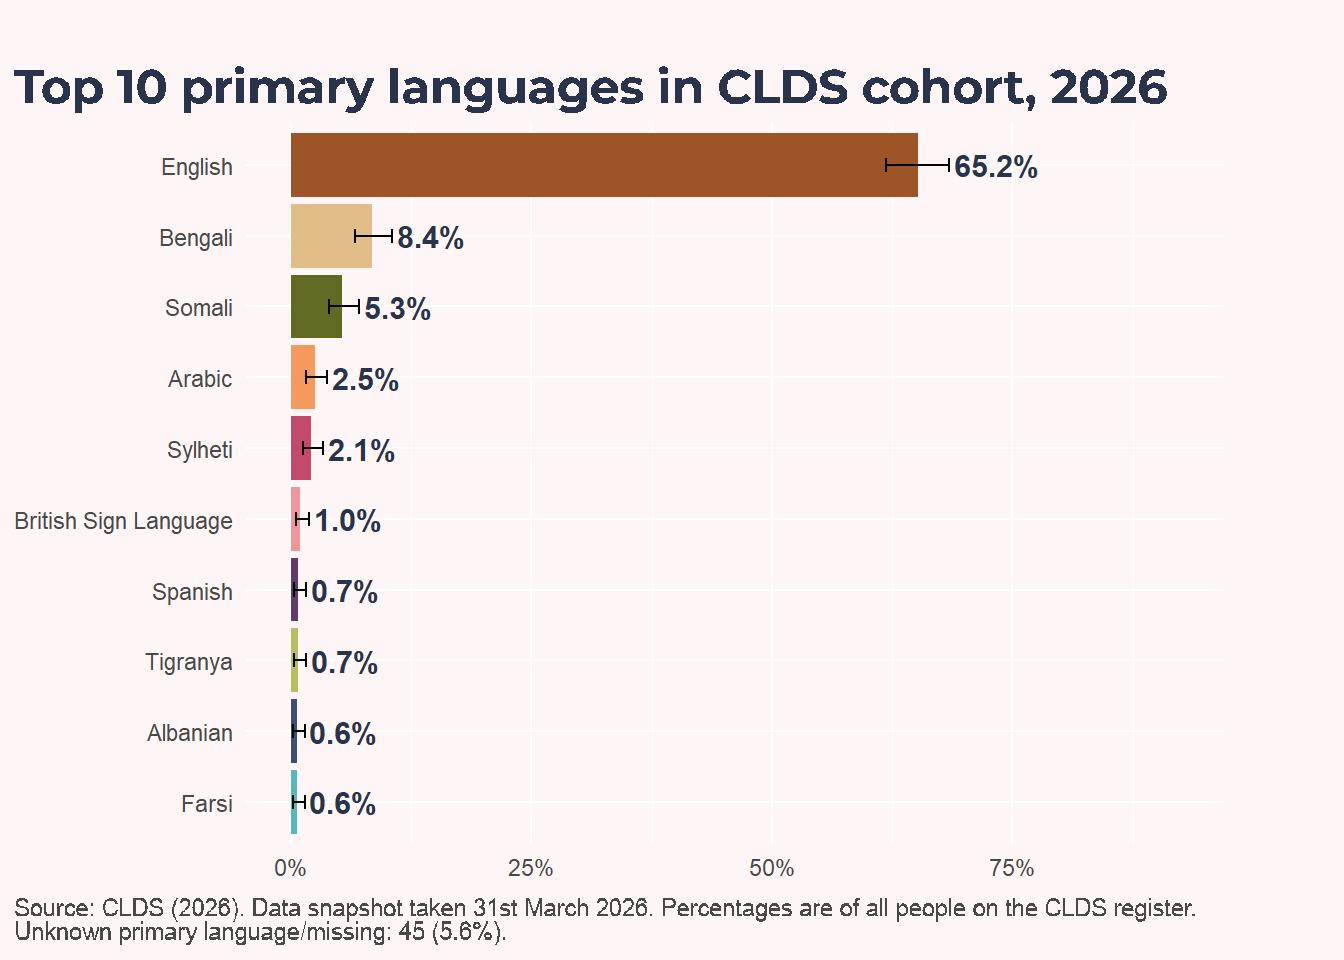
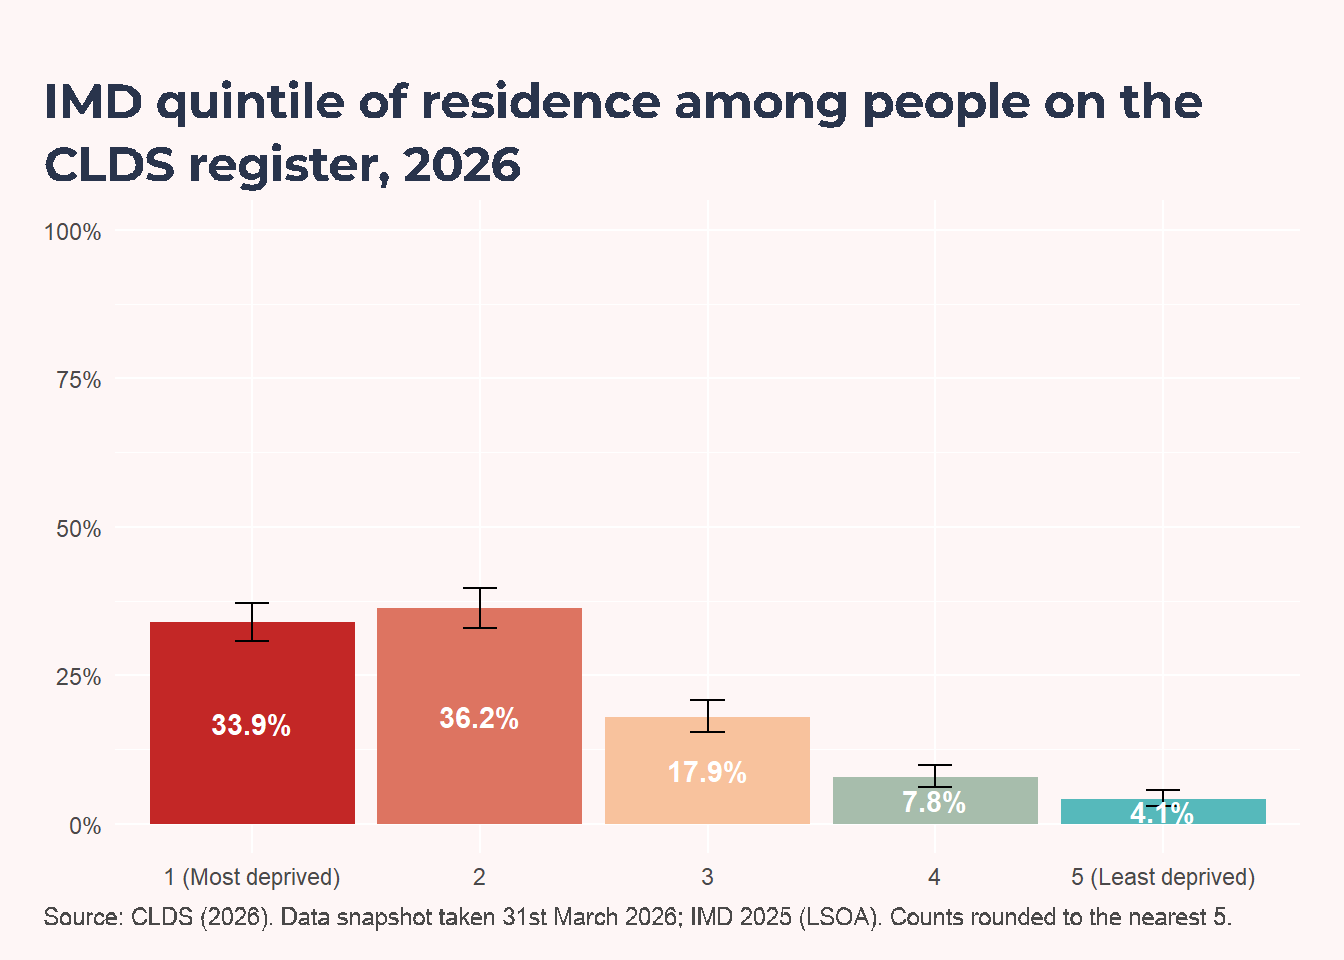
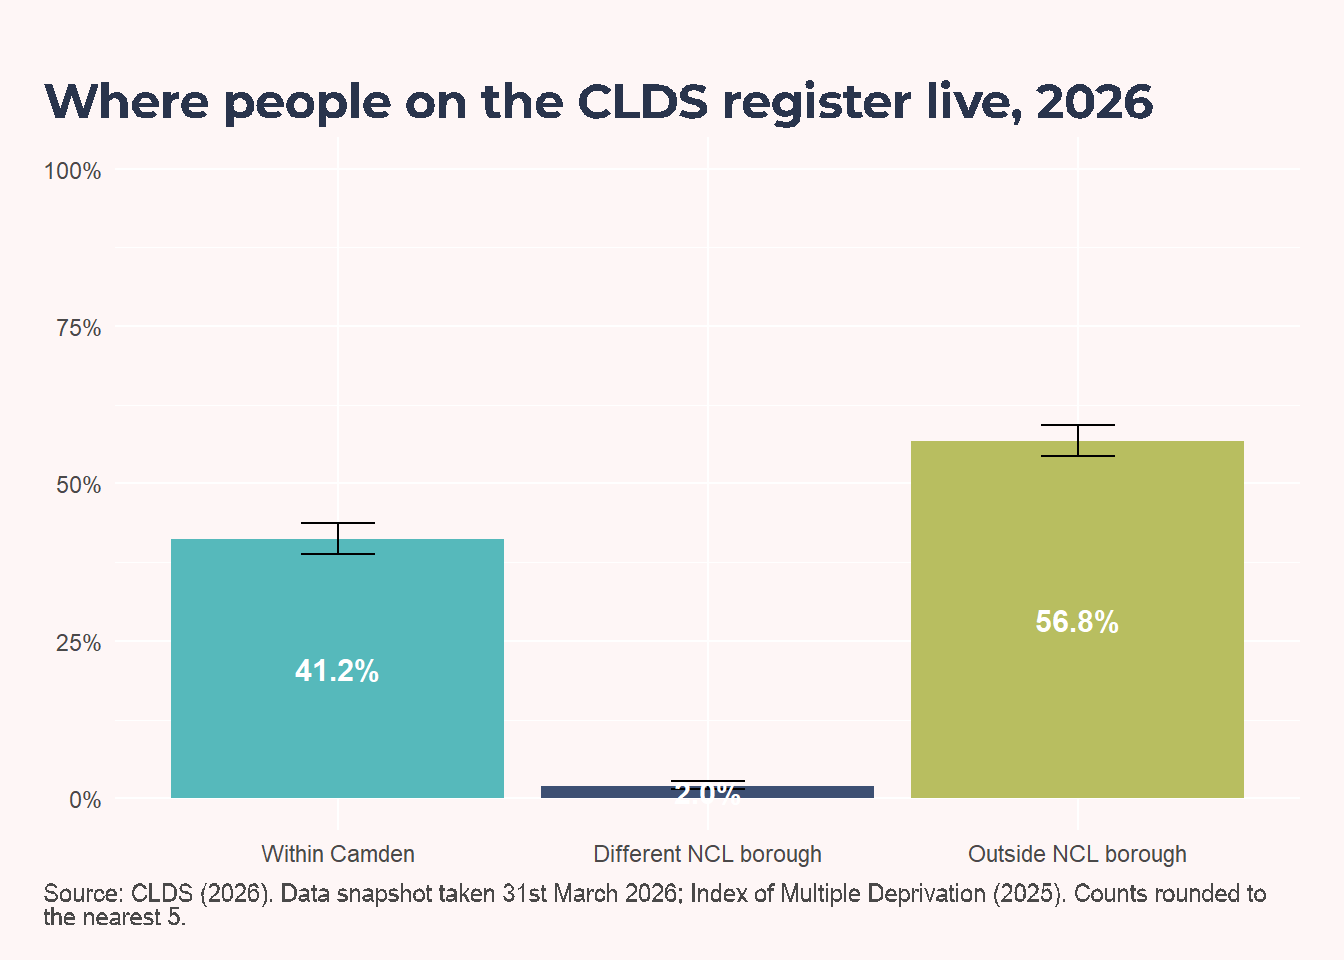
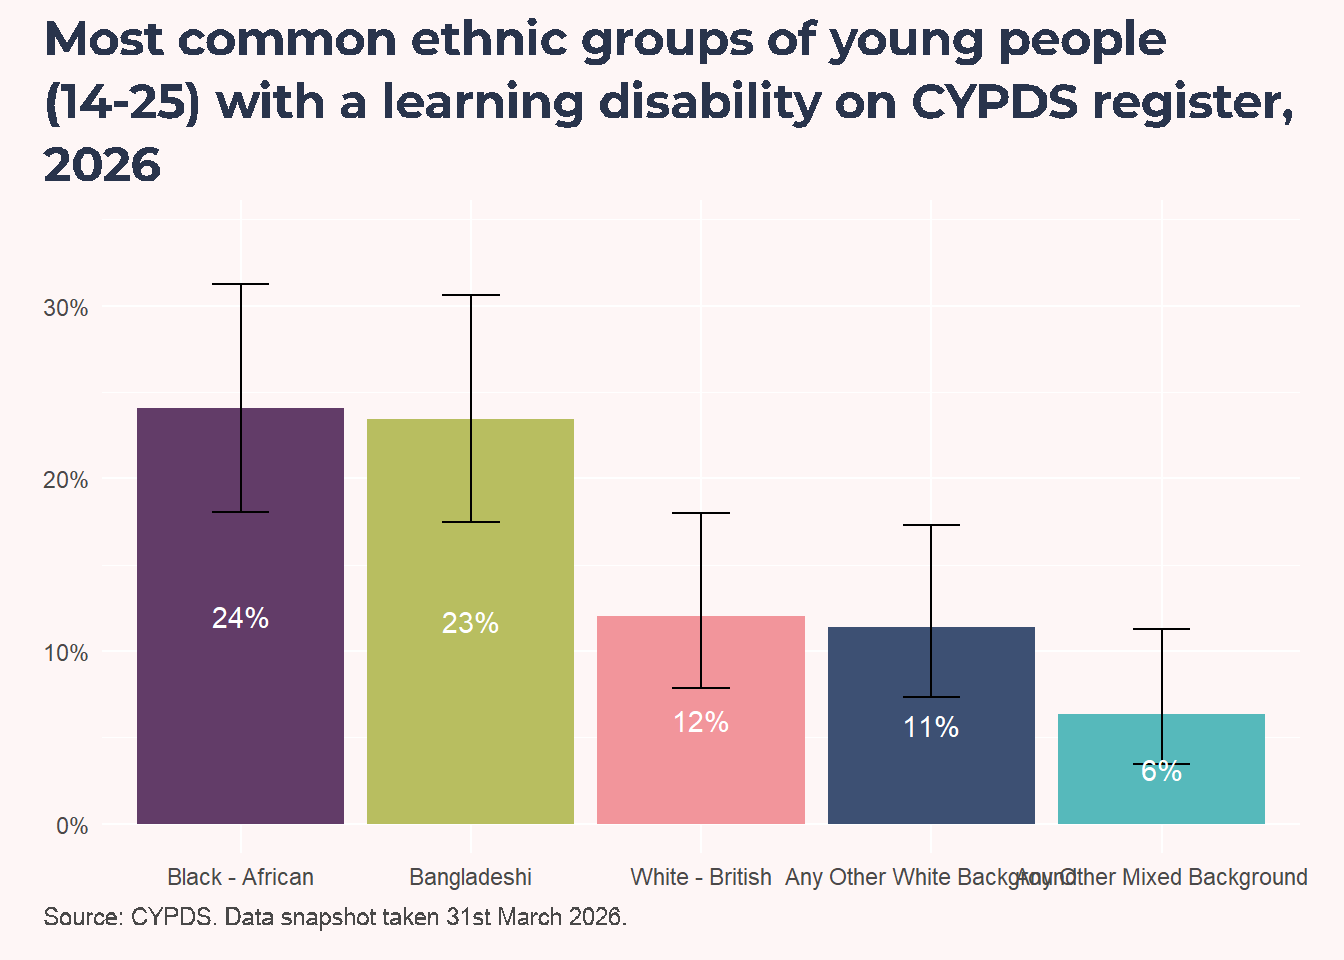
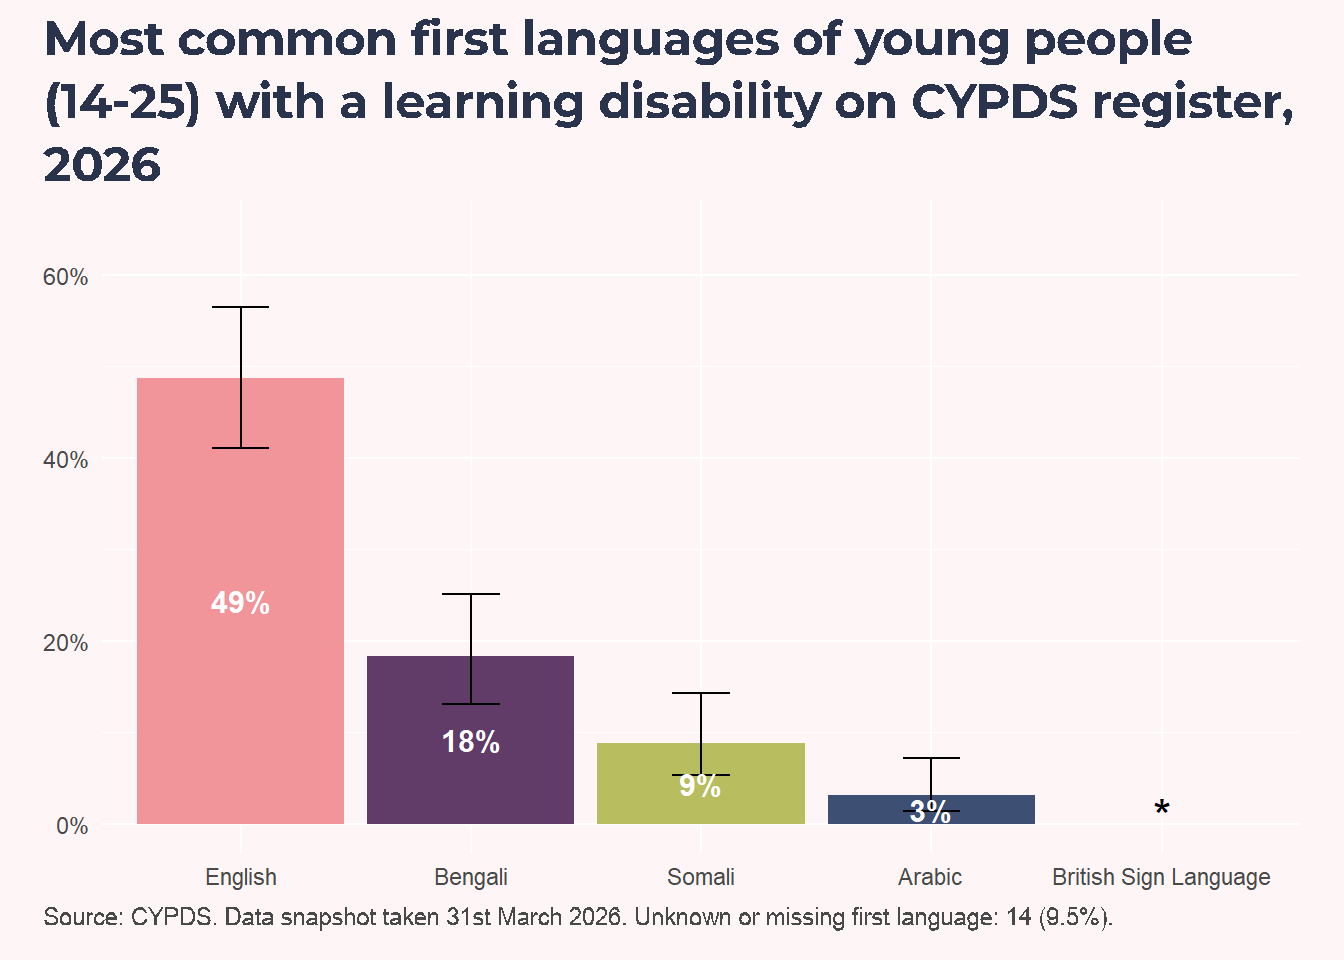
Across the current CLDS profile, the largest age group is 20-29 (26.5%). Sex distribution is Male 61.1% and Female 38.9%. The largest recorded ethnicity category is White (46.7%), and the most common recorded non-English primary language is English (65.2%), with unknown/not recorded language at 5.6%. By area, the largest IMD group is quintile 2 (36.2%), and most people live outside ncl borough (56.8%).
Learning disability severity and co-occurring conditions
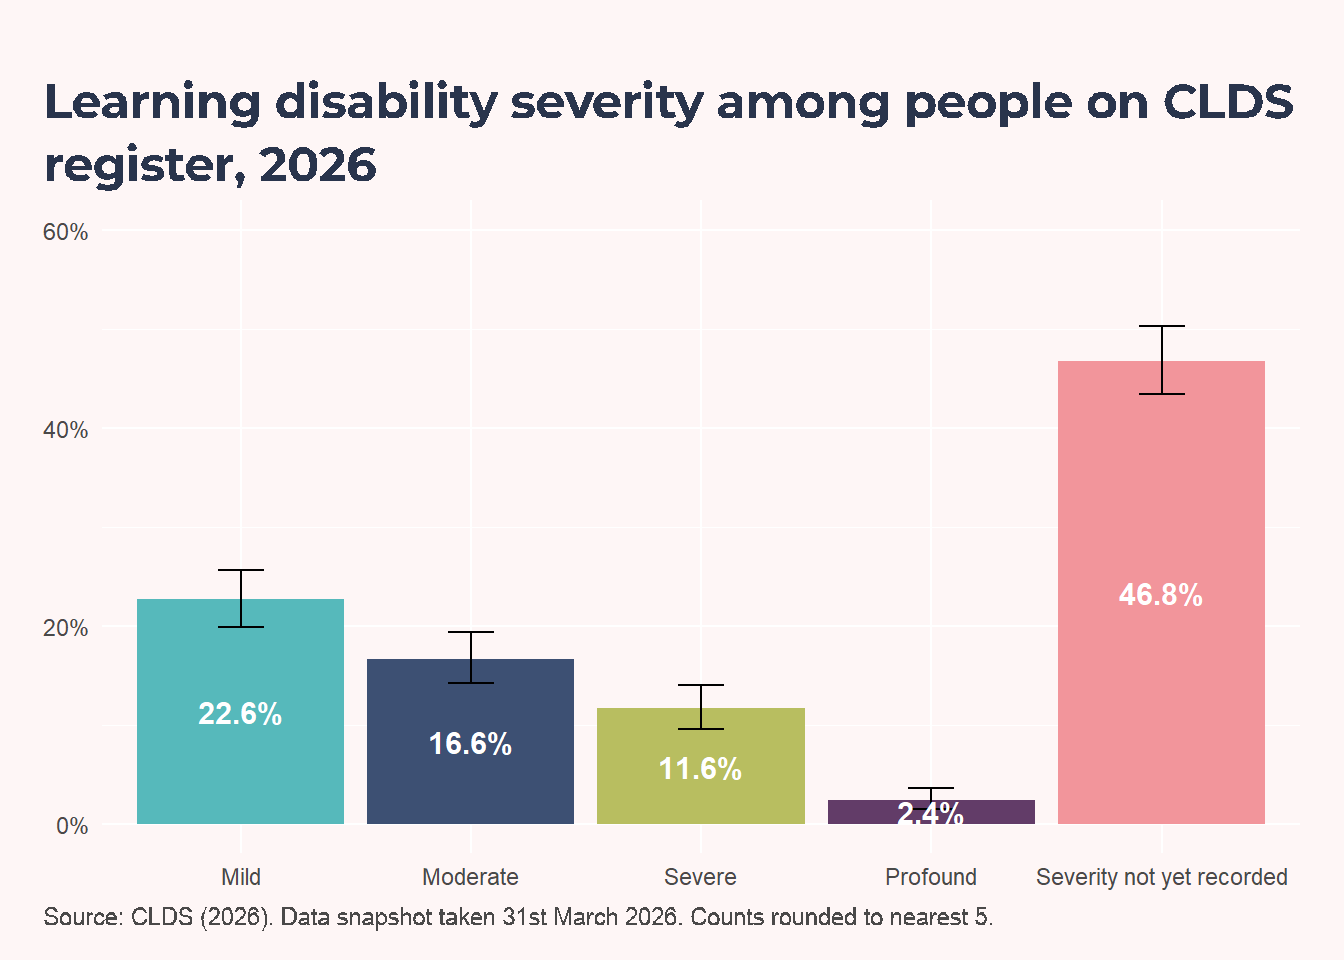
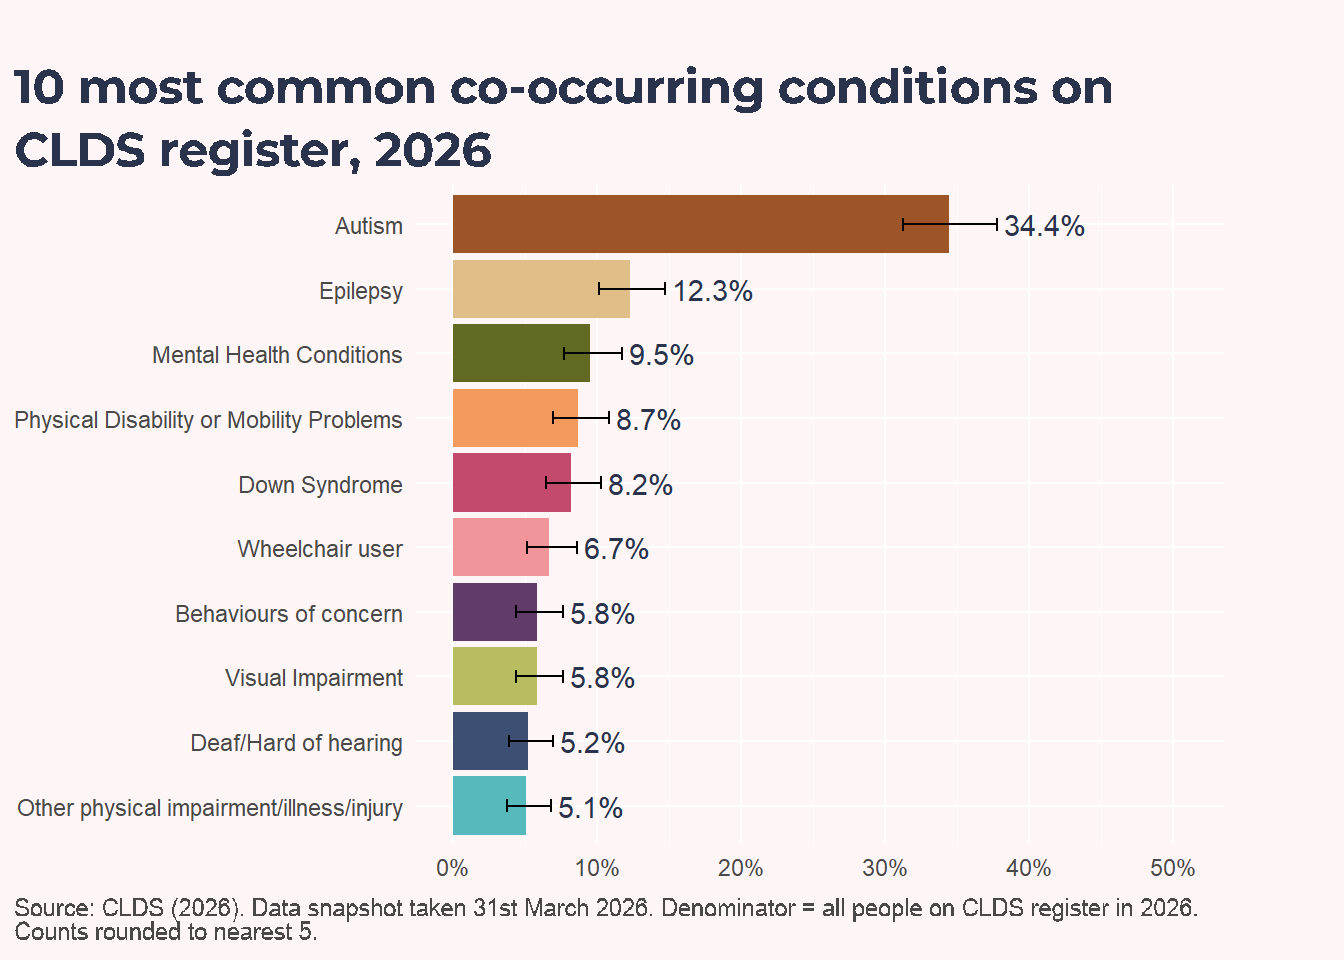
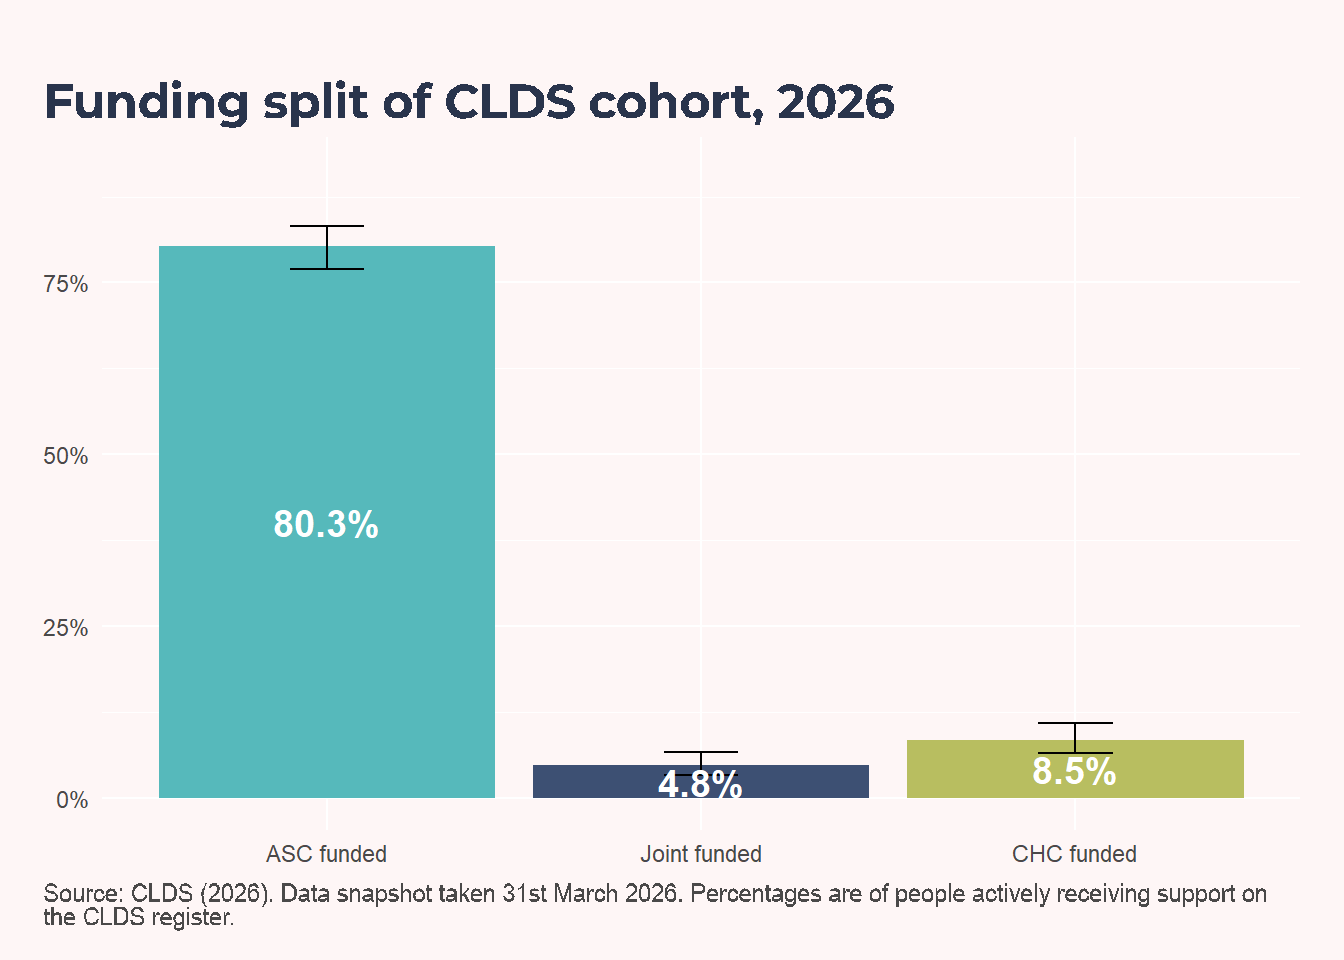
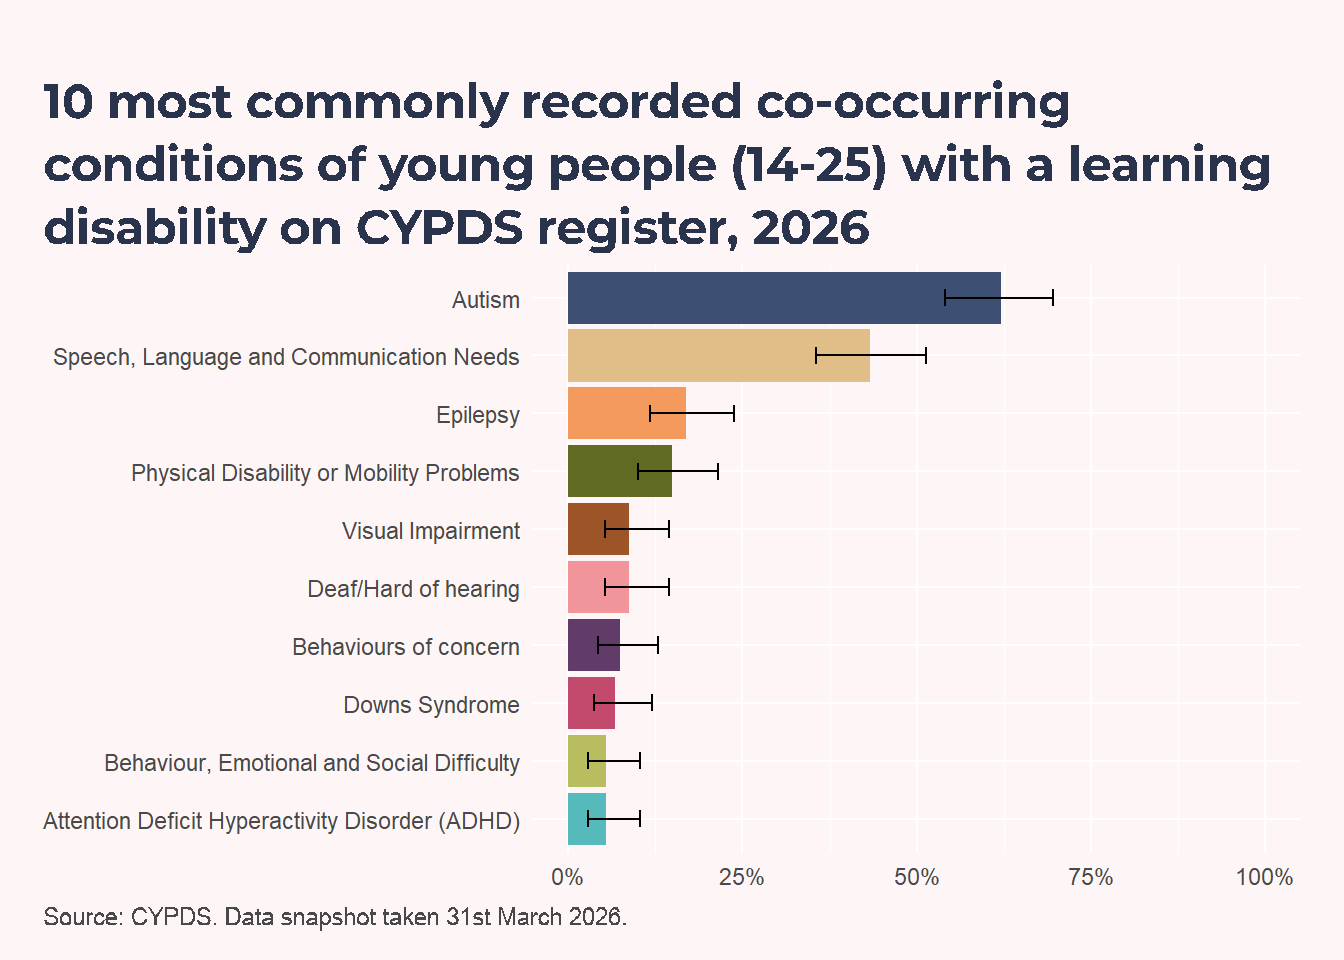
Autism (n = 280) and Down syndrome (n = 65) are among the most frequently recorded co-occurring conditions. Only 53% of people on the CLDS register have learning disability severity recorded (430 of 810), so other disabilities and health conditions may also be under-recorded. CLDS is taking active steps to review and add missing data.
Carers and living setting
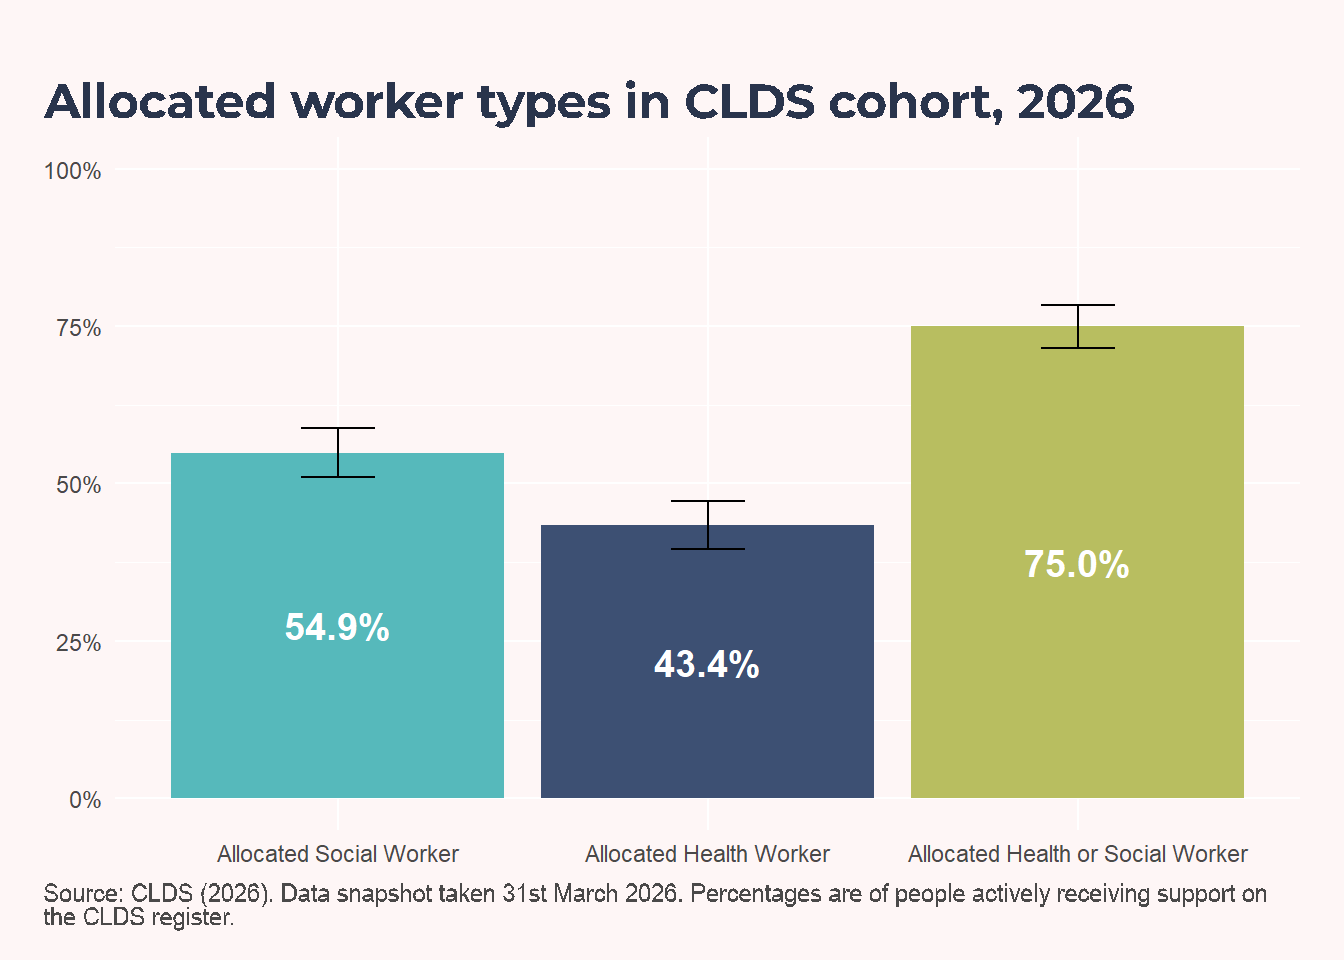
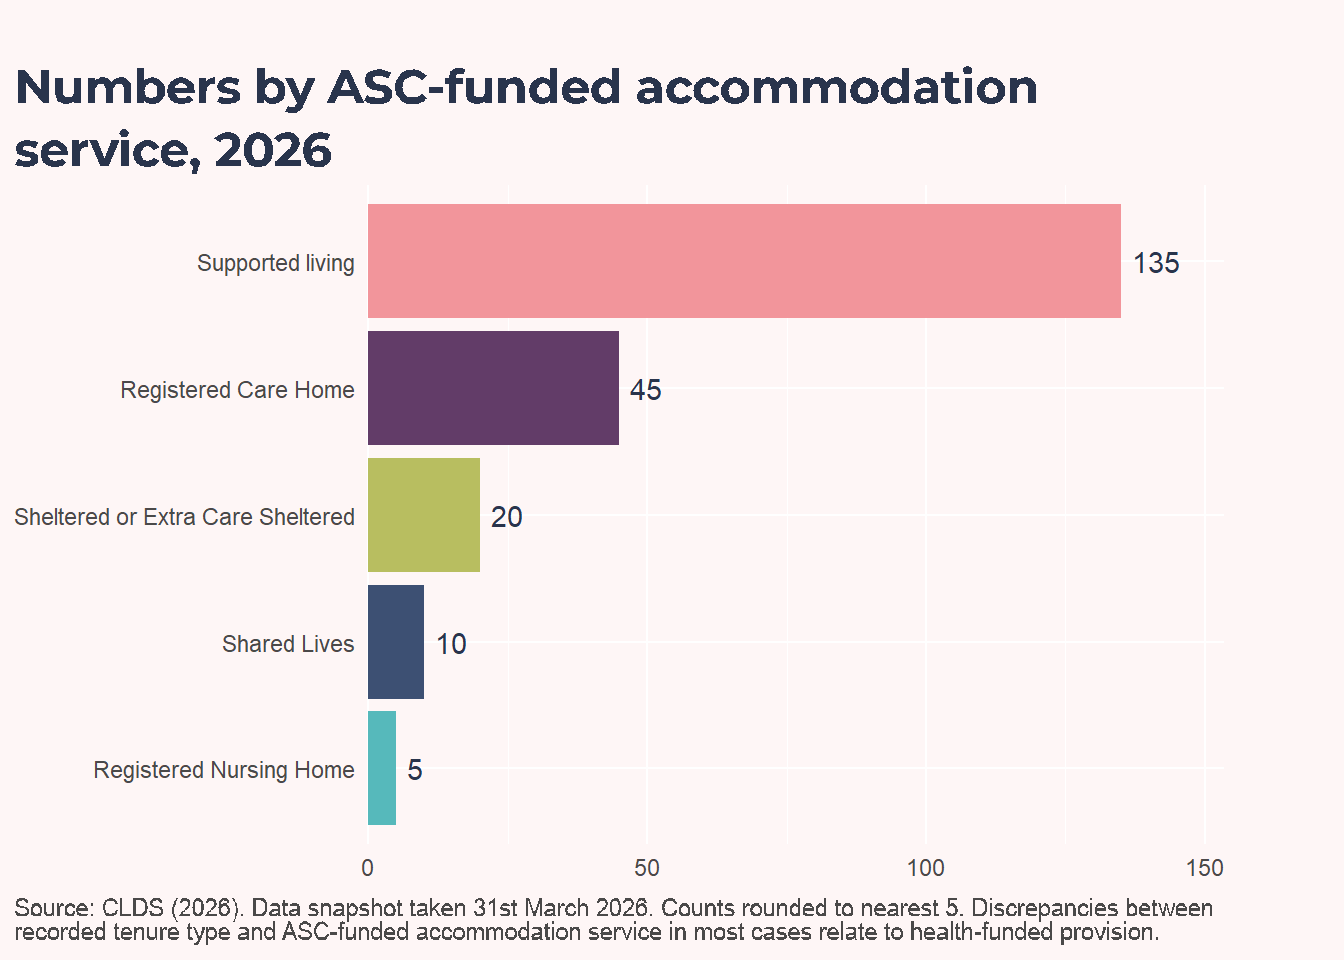
In 2026, 370 / 810 people on the CLDS register lived in the family home (45.8%).
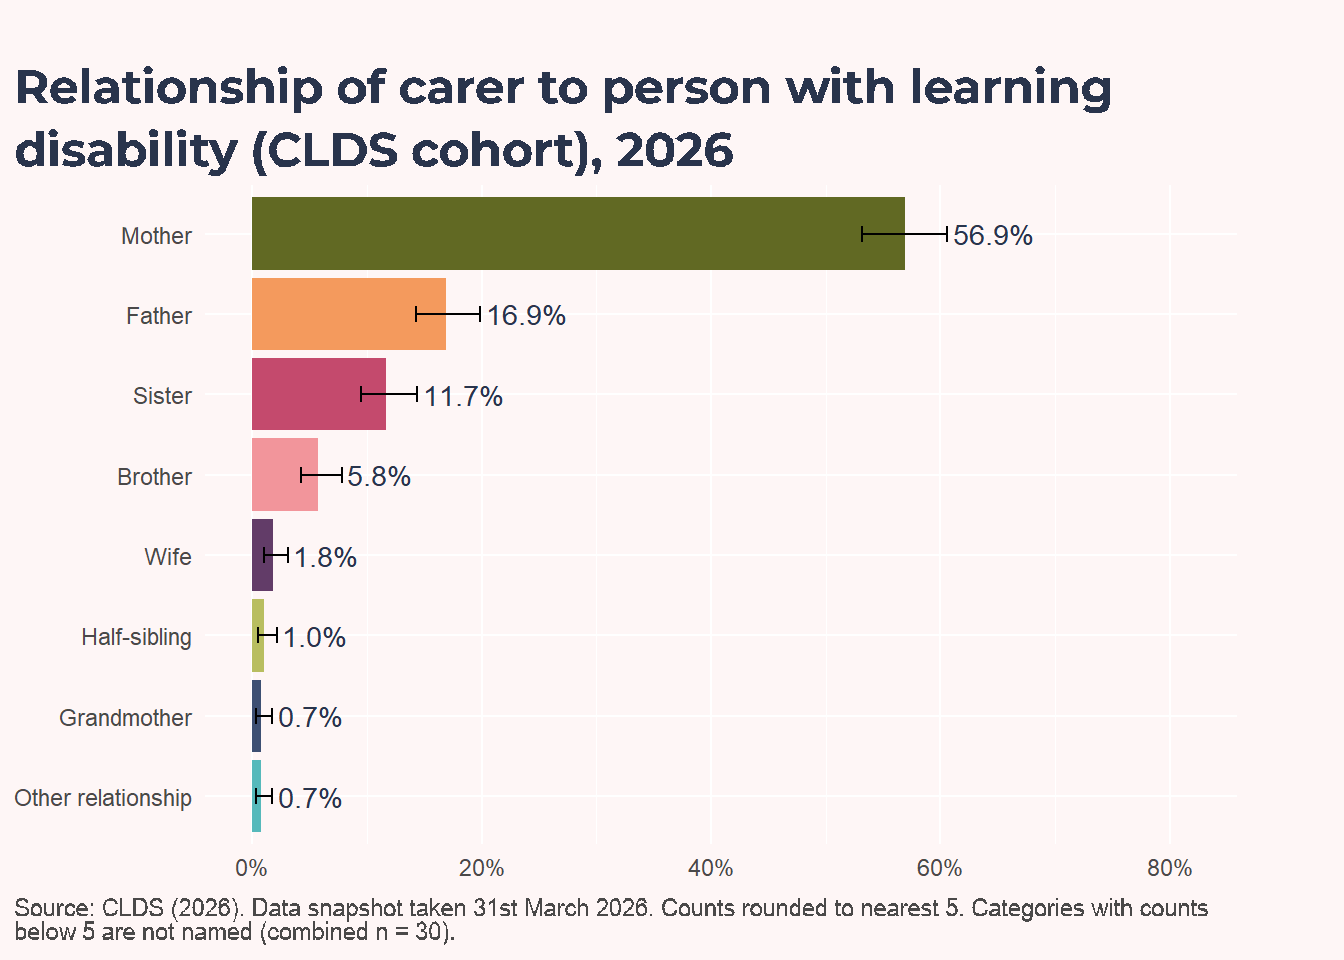
For CLDS, living in the family home is a useful proxy for having an informal carer, but it is not exact: some people may be living with family without receiving informal care, and some people receiving informal care may be living in a separate property.
In 2026, care plans were reviewed in the last 12 months for 280 people (55.6%), and not reviewed in the last 12 months for 225 people (44.4%).
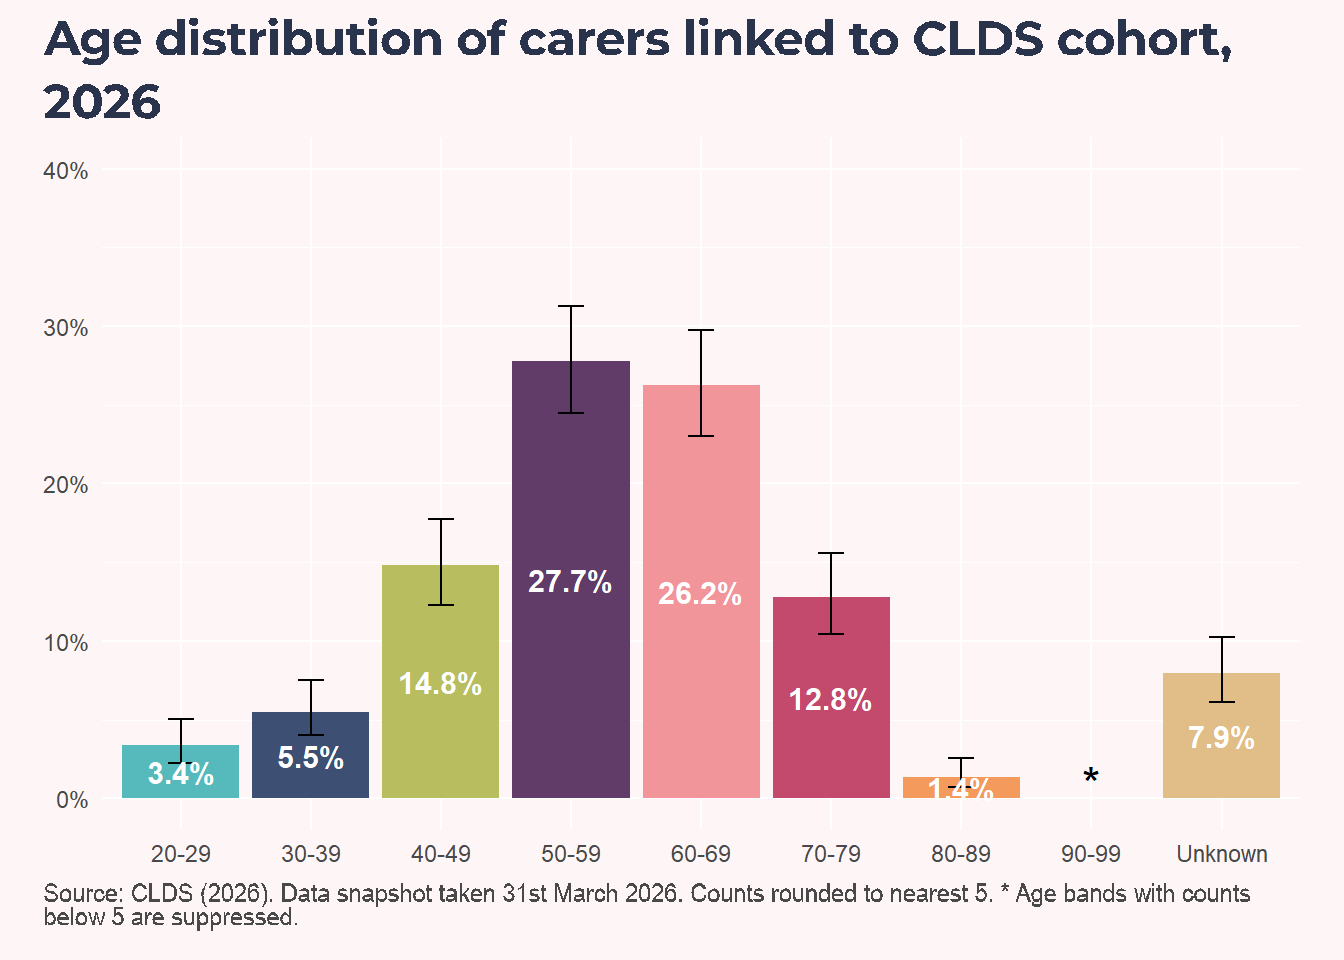
Of known-age carers linked to people on the CLDS register, around 95 are aged 70+ and around 170 are in their 60s (counts rounded to the nearest 5).
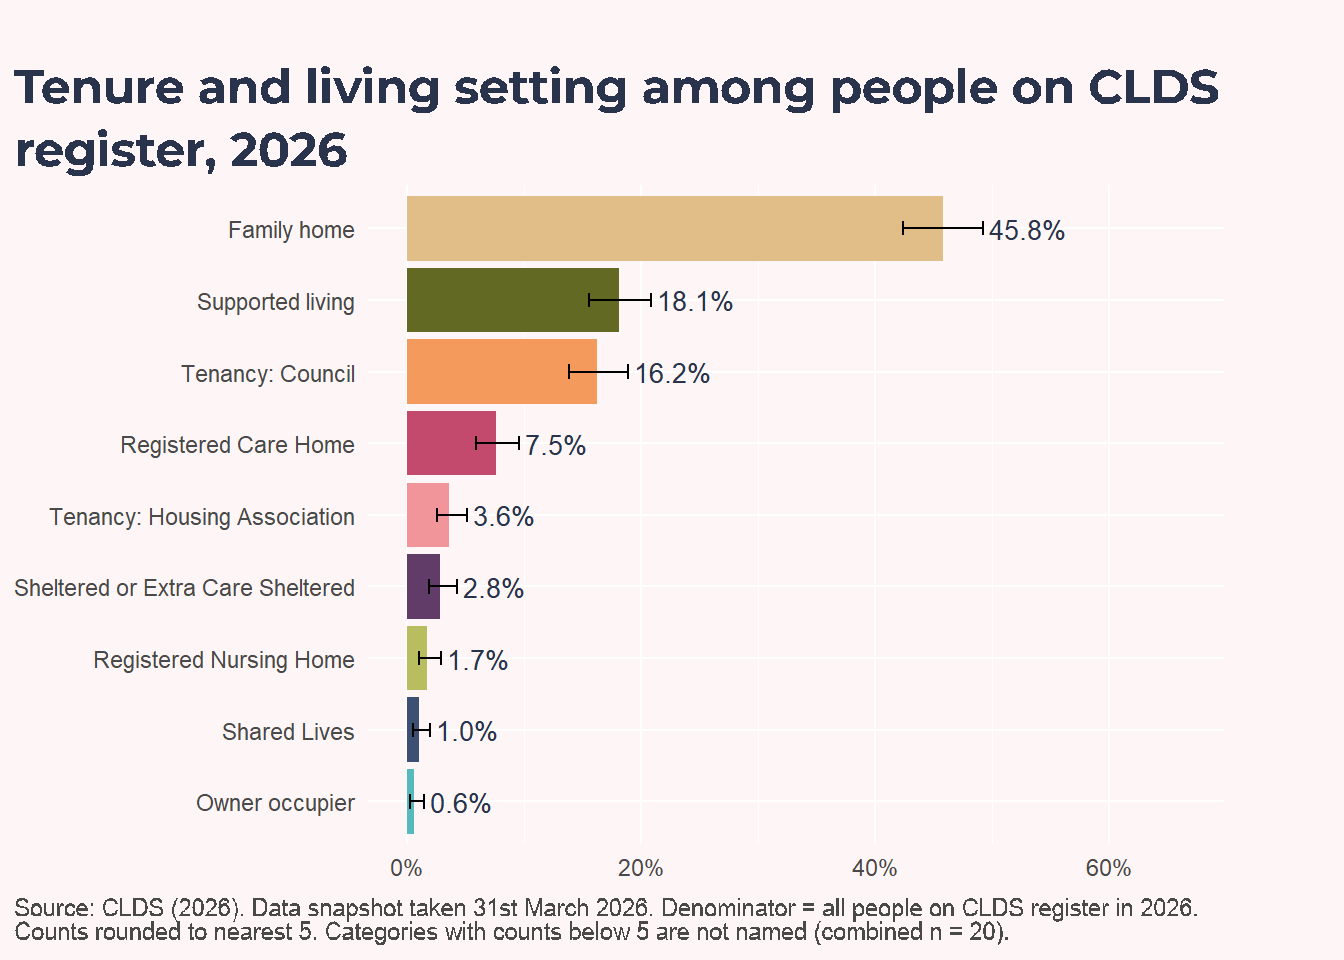
Services accessed
Employment
In 2026, 40 people were recorded as seeking work and 55 were recorded as employed. Of those recorded as employed, 14 are in receipt of services and are reviewed annually, and around six others are also confirmed to still be in employment. Because people in employment are often among those with lower ongoing support needs, some may have long periods without CLDS contact, so employment status may be out of date for a subset.
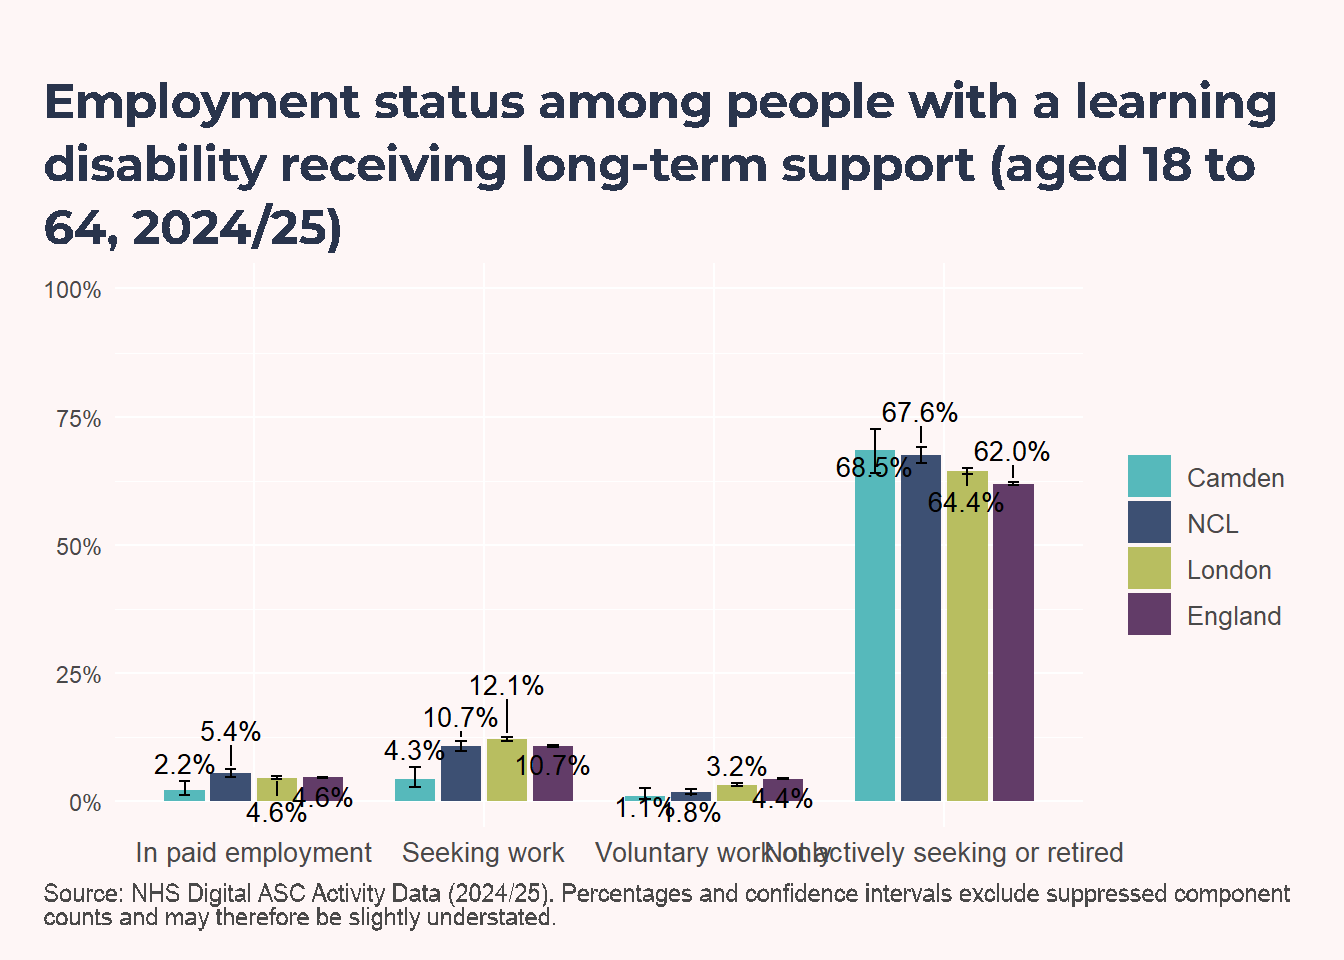
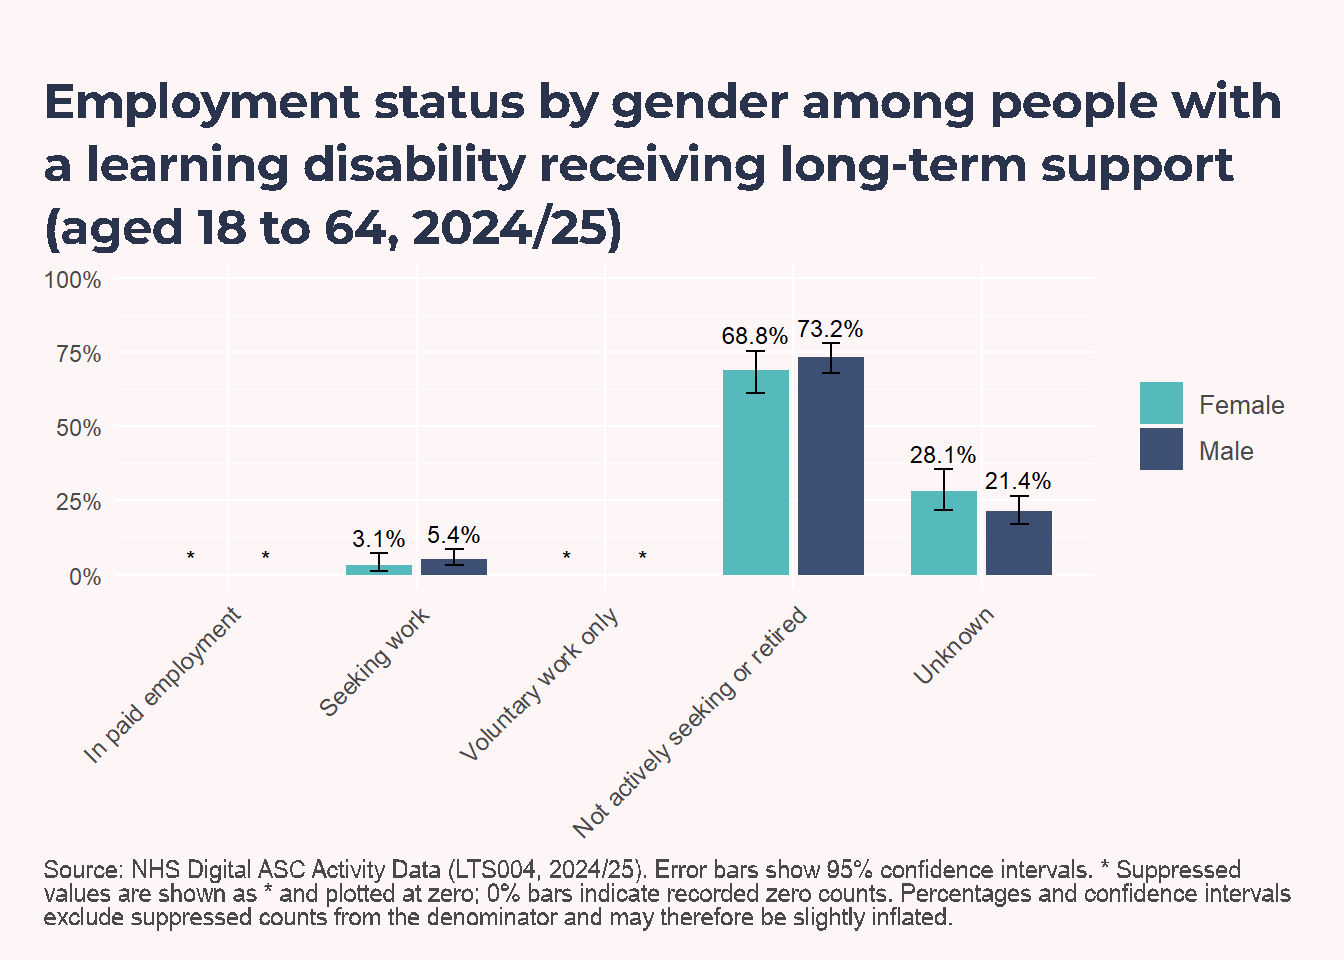
The Disability Job Hub supports both people with and without learning disabilities. However, PWLD account for three-quarters of the current waiting list, as 30 of the 40 residents waiting for support.
In 2026, about 25 residents attended in-house workshops or training sessions with the Disability Job Hub. These include
Skills for Work Training (8-week training course focused on soft skills / employability)
Group Travel Training (4-week programme that includes classroom-based learning and travelling in the community)
Around 15 residents were supported into a job (including paid, voluntary or work experience placements), and around 10 residents were supported into external education or training.
CYPDS
Demography and time trends
Referrals and support
Conditions and inequalities
Education
NoteTechnical Note - Learning Disability Proxy
In education datasets, the term “learning disability” is not used in the same way as in health and adult social care. Education coding more commonly uses “learning difficulty” categories, which can include learning disability and other needs such as dyslexia and ADHD.
For this reason, this section uses a learning disability proxy based on pupils with moderate learning difficulty (MLD), severe learning difficulty (SLD), or profound and multiple learning difficulty (PMLD). This approach is consistent with Public Health England analysis Public Health England (2020) PWLD in England: Chapter 1: education and children’s social care..
| Camden Pupils aged 14+ with a learning disability proxy by category, Summer 2026 | |||
| Summer 2026 school census (n = 3,375 pupils) | |||
| Learning disability proxy category | n | Pupils | % of pupils |
|---|---|---|---|
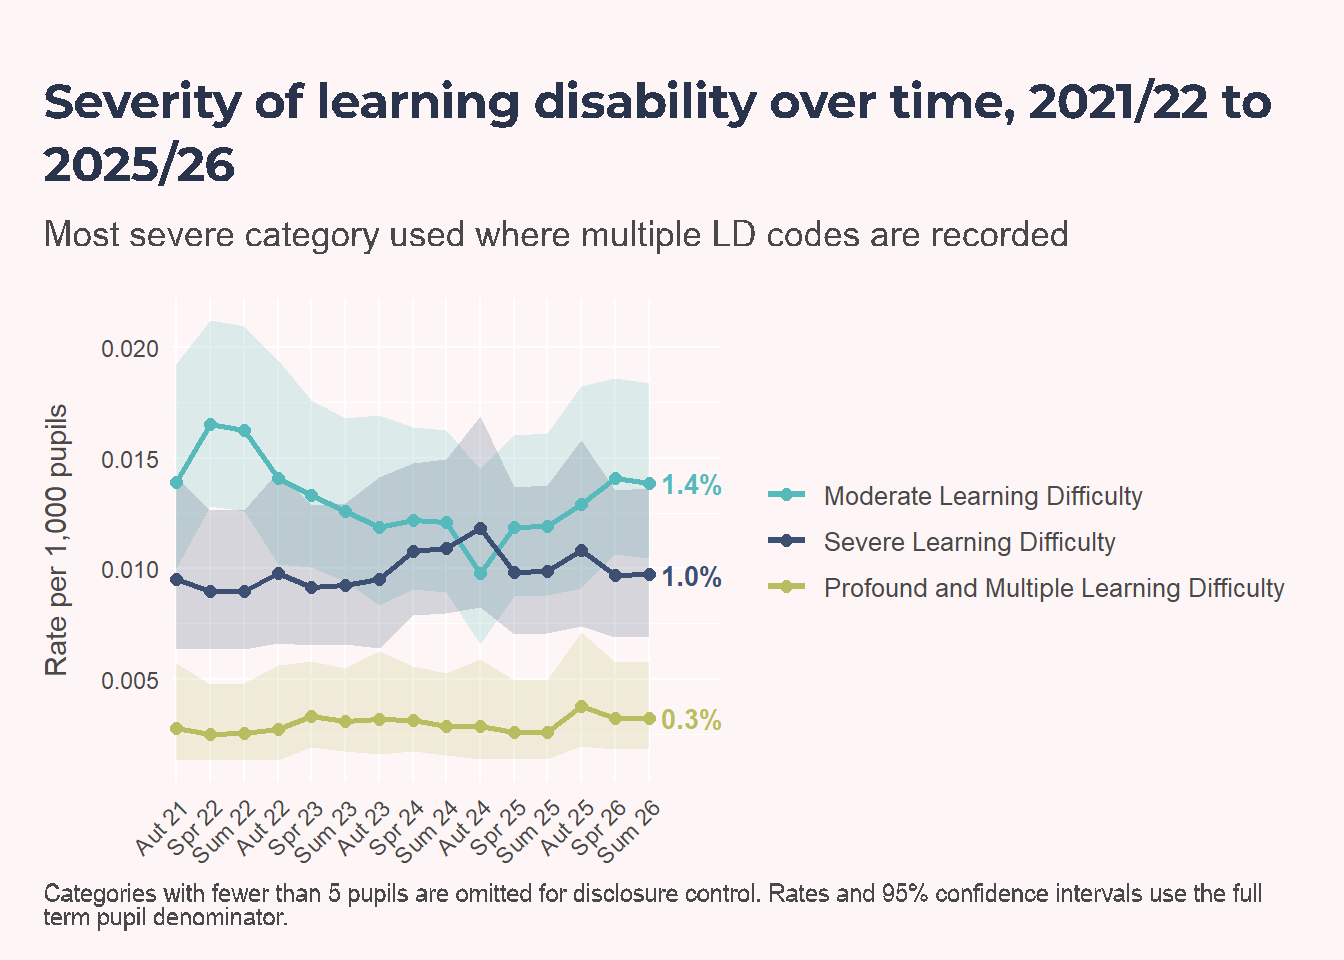
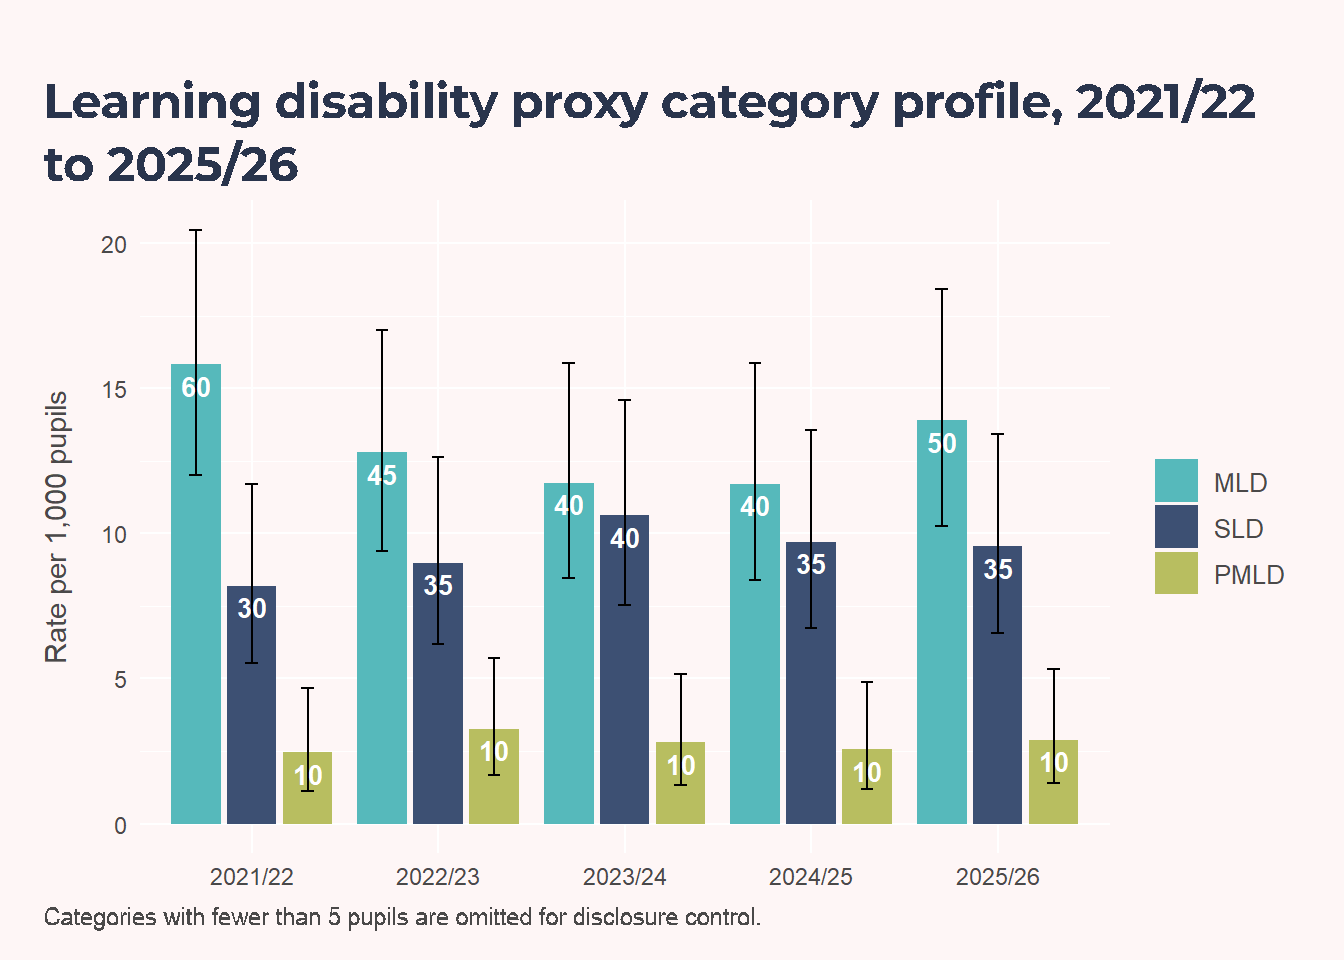
| Moderate Learning Difficulty | 47 | 45 | 1.4 |
| Severe Learning Difficulty | 33 | 35 | 1.0 |
| Profound and Multiple Learning Difficulty | 11 | 10 | 0.3 |
| Source: School Census, Summer 2026. Camden residents attending Camden state-funded schools. Categories with fewer than 5 pupils omitted. Remaining counts rounded to the nearest 5. Percentages use the full Summer 2026 pupil denominator. |
|||
Demography
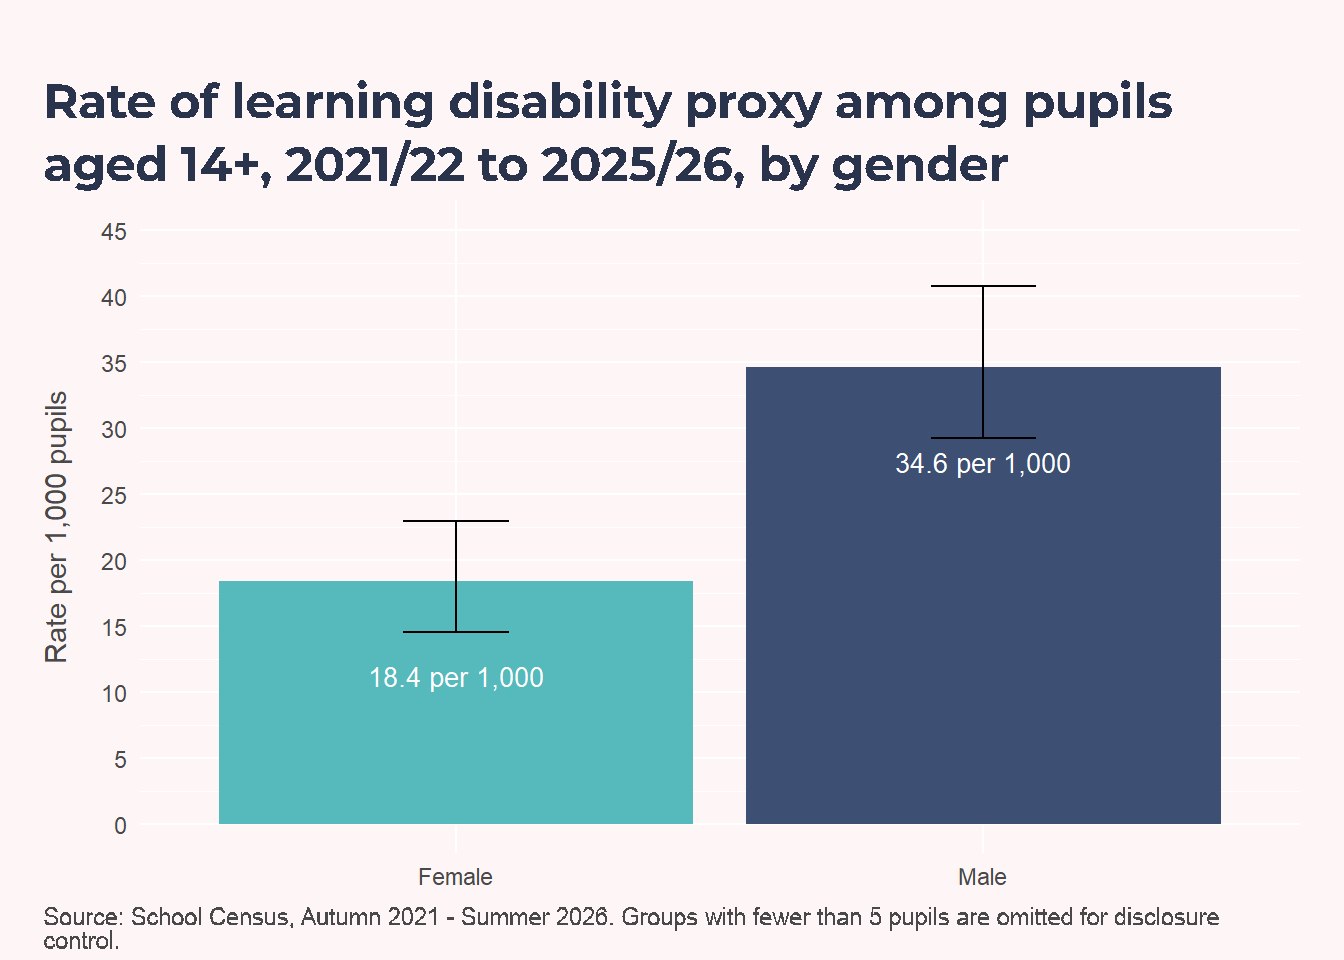
Learning Support
Among unique pupils with a learning disability proxy (MLD/SLD/PMLD), categories with fewer than 5 pupils are omitted for disclosure control. Published categories use the full learning disability proxy denominator: EHCP 150 (67.7%); SEN Support 70 (32.3%).
Additional SEN types
This table summarises other recorded SEN types among pupils included in the learning disability proxy group.
| Other SEN types among pupils with a learning disability proxy | ||
| Unique pupils with MLD, SLD or PMLD, 2021/22 to 2025/26 (n = 225) | ||
| Other SEN type | Pupils | % of pupils |
|---|---|---|
| None | 85 | 37.2% |
| Autistic Spectrum Disorder | 45 | 21.1% |
| Speech, Language and Communication Needs | 45 | 20.2% |
| Social, Emotional and Mental Health | 25 | 10.8% |
| Physical Disability | 10 | 5.4% |
| Source: School Census, Autumn 2021 - Summer 2026. Camden residents attending Camden state-funded schools. Categories with fewer than 5 pupils omitted. Remaining counts rounded to the nearest 5. Percentages use the full learning disability proxy denominator; omitted categories are not redistributed. |
||
Social contact was adequate for most PWLD accessing adult social care
Residents who had received a service from ASC in the last 12 months were asked whether they had any unmet social contact needs.
57% of PWLD as their primary support need (PSN) reported having no unmet social contact needs.
87% reported at least adequate social contact with people
There was a positive association between PSN and social contact outcomes (Goodman and Kruskal’s γ = 0.43; 95% CI 0.29–0.57). This indicates that respondents with a PSN of learning disability tended to report a more positive response than respondents with a different PSN.
This comparison group is not the general population, but everyone receiving an ASC service with a non-LD PSN. It should also be noted that people may have a learning disability, but fall into one of these other PSN categories. The PSNs of people who responded to this question were:
55% Physical Support
21% Learning Disability Support
19% Mental Health Support
3% Memory and Cognition, and
2% Other.
As the item response rate for this question was 20% of everyone who took the survey, there could also be significant response bias in this measure. For example, people maybe be more likely to skip a question if thinking about it brings unpleasant feelings, or if there is stigma attached to feeling lonely.